Related Experiment Video
Updated: Feb 25, 2026
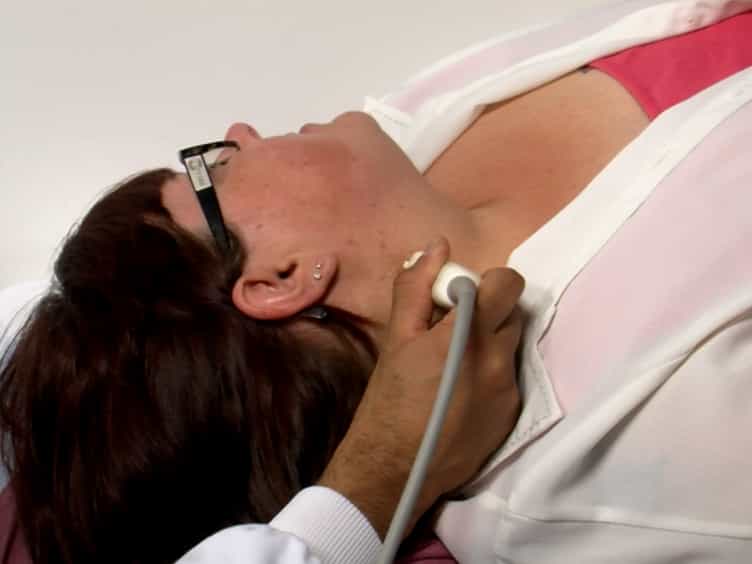
A Methodological Approach to Non-invasive Assessments of Vascular Function and Morphology
Published on: February 7, 2015
Carotid intima-media thickness and carotid plaque represent different adaptive responses to traditional
Liz Andréa Villela Baroncini1, Lucimary de Castro Sylvestre1, Roberto Pecoits Filho1
1Pontifícia Universidade Católica do Paraná, Medical School, Health Sciences Postgraduate Program, Rua Imaculada Conceição 1155 - Bloco CCBS, CEP: 80215-901 Curitiba, Brazil.

Insights
Hypertension significantly increases carotid intima-media thickness (CIMT), with age and male sex also contributing. Age and dyslipidemia elevate carotid plaque risk, highlighting distinct impacts of cardiovascular factors.
Area of Science:
- Cardiovascular Medicine
- Vascular Biology
- Diagnostic Imaging
Background:
- Cardiovascular risk factors significantly influence atherosclerosis.
- Carotid intima-media thickness (CIMT) and plaque presence are key indicators of vascular health.
- Understanding the independent and combined effects of risk factors is crucial for risk stratification.
Purpose of the Study:
- To evaluate the impact of traditional cardiovascular risk factors (hypertension, diabetes, dyslipidemia, smoking) and coronary artery disease (CAD) on CIMT.
- To determine the influence of these factors on the occurrence of carotid plaque.
- To correlate CIMT and plaque presence with specific risk factors.
Main Methods:
- Carotid artery ultrasound was performed on 553 outpatients (mean age 67.06 years).
- Measurements included carotid intima-media thickness (CIMT) and screening for carotid plaque.
- Statistical analysis assessed the association between cardiovascular risk factors and CIMT/plaque presence.
Main Results:
- Higher CIMT was observed in males and patients with hypertension (P < .001).
- Mean CIMT increased with age (0.0059 mm/year).
- Hypertension combined with diabetes, dyslipidemia, or CAD significantly increased CIMT. Age, dyslipidemia, and CAD were associated with increased plaque occurrence.
Conclusions:
- Hypertension is the primary driver of increased CIMT, followed by age and male sex.
- Age and dyslipidemia are significant predictors of carotid plaque formation.
- Different risk factors can independently contribute to increased CIMT and plaque, impacting arterial wall health and clinical prognosis.
Aim:
To assess the effects of each traditional cardiovascular risk factor (hypertension, diabetes mellitus, dyslipidemia, and smoking), including the presence of coronary artery disease (CAD), on carotid intima-media thickness (CIMT) and to assess the degree of carotid plaque occurrence.
Methods:
A total of 553 outpatients (216 men and 337 women; mean age 67.06 ± 12.44 years) who underwent a carotid artery ultrasound were screened for carotid plaque and CIMT measurements.
Results:
The CIMT medians were higher in males (P < .001) and in patients with hypertension (P < .001). A linear increase occurred in mean CIMT of 0.0059 mm for each year of increase in age. The presence of plaque indicated a tendency to correlate with CIMT (P = .067). The presence of hypertension associated with diabetes (P = .0061; estimated difference 0.0494 mm) or dyslipidemia (P = .0016; estimated difference 0.0472 mm) or CAD (P = .0043; estimated difference 0.0527 mm) increased the mean CIMT measurements. The probability of plaque occurrence in carotid arteries is influenced by the age (P < .001) and is higher in patients with dyslipidemia (P = .008) and CAD (P < .001).
Conclusions:
Hypertension is the strongest cardiovascular risk factor that increases CIMT, followed by age and male sex. Age and dyslipidemia increase the probability of carotid plaque. Increased CIMT and plaque could be present in the same patient caused by different risk factors and with independent effects on the artery wall and different clinical prognoses.
More Related Videos
 06:04
Author Spotlight: Assessing the Cardiovascular Profile of Patients with Metabolic Syndrome
Published on: September 27, 2024
 09:36
A Magnetic Resonance Imaging-based Computational Protocol for Analysis of Plaque Morphology and Hemodynamics in Patients with Carotid Artery Stenosis
Published on: August 12, 2025
Related Concept Videos
 01:30
Atherosclerosis I: Introduction
 01:30
Coronary Artery Disease I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:26
Coronary Artery Disease II: Pathophysiology
 01:26
Atherosclerosis III: Management
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT