Related Experiment Video
Updated: Feb 24, 2026

Three-Dimensional Reconstruction of Orbital Fractures
Published on: May 16, 2025
Pediatric orbital blowout fractures
Stella Y Chung1, Paul D Langer
1Institute of Ophthalmology and Visual Science, Rutgers New Jersey Medical School, Newark, New Jersey, USA.

Purpose Of Review:
The current study reviews the recent literature on pediatric orbital blowout fractures and provides guidelines on their management.
Recent Findings:
The most common problem among patients requiring surgical revision of a previously repaired orbital floor fracture is an improperly placed orbital floor implant, usually erroneously placed under the posterior bony ledge. Although the transconjunctival incision can be combined with a lateral canthotomy and cantholysis, excellent surgical exposure can be obtained without the need for these latter relaxing maneuvers. In surgically repaired pediatric orbital blowout fractures with preoperative diplopia (both trapdoor and nontrapdoor), approximately 85% of patients recover completely over time. Delayed orbital tissue atrophy may play a role in the development of late enophthalmos.
Summary:
Most cases of pediatric orbital fracture can initially be followed conservatively to determine if disabling diplopia, when present, resolves without surgery. A notable exception is the trapdoor fracture, in which herniated tissue becomes entrapped by a recoiled bone fragment, causing marked or complete reduction in motility and/or an oculocardiac reflex; we recommend that these fractures be repaired within 24 h from the time of diagnosis. Enophthalmos resulting from an orbital floor fracture does not need to be prevented with early surgery. Enophthalmos can be allowed to develop over time to determine if it is noticeable, and then repair undertaken, if necessary, at that time. When surgery is indicated, a simple transconjunctival incision is preferred over a cutaneous incision, and care should be taken to insure that the implant is placed on the bony ledge at the posterior edge of the defect. Many children with blowout fractures will not require surgery, and those that do usually have excellent outcomes provided the recommendations are closely followed.
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:27
Cranial Bones: Lateral View
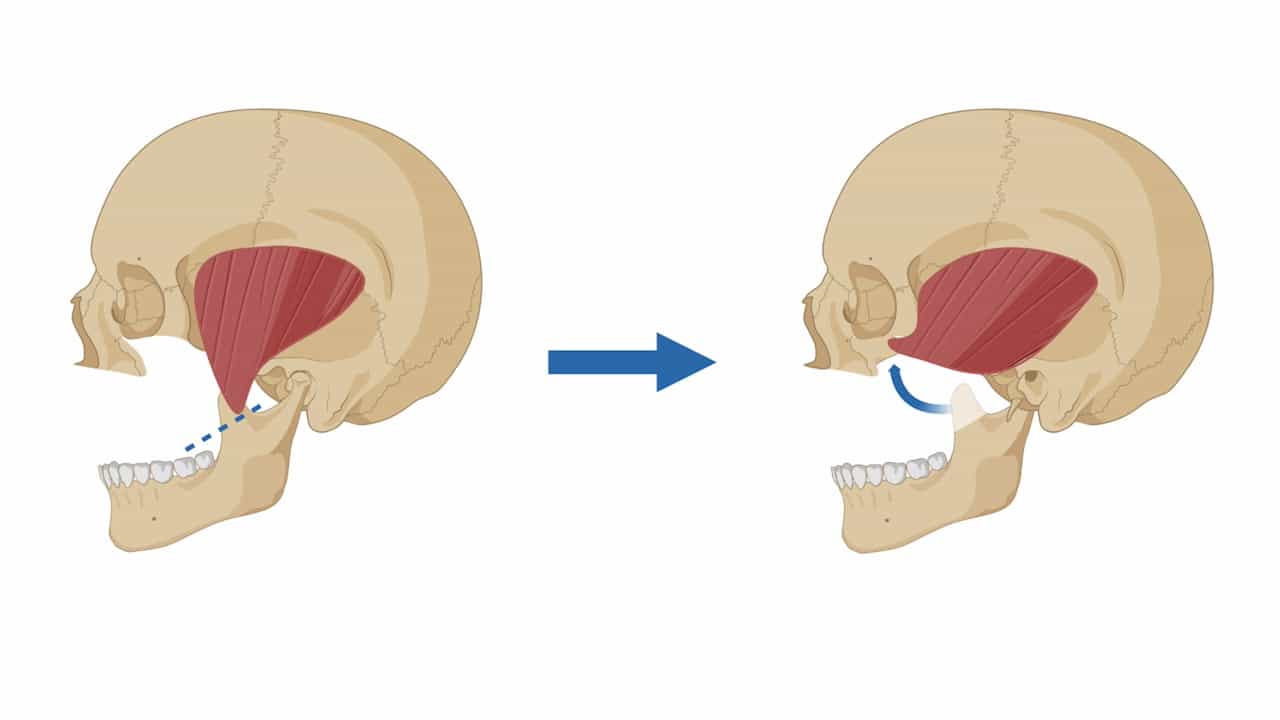
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...