Related Experiment Video
Updated: Feb 24, 2026

Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Optimal Dose, Timing and Ratio of Blood Products in Massive Transfusion: Results from a Systematic Review
Zoe K McQuilten1, Gemma Crighton2, Susan Brunskill3
1Transfusion Research Unit, Department of Epidemiology and Preventive Medicine, Monash University, Melbourne, Australia; Australian and New Zealand Intensive Care Research Centre (ANZIC-RC), Department of Epidemiology and Preventive Medicine, Monash University, Melbourne, Australia.

Optimal dose, timing and ratio to red blood cells (RBC) of blood component therapy (fresh frozen plasma [FFP], platelets, cryoprecipitate or fibrinogen concentrate) to reduce morbidity and mortality in critically bleeding patients requiring massive transfusion is unknown. We performed a systematic review for randomized controlled trials (RCT) in MEDLINE, The Cochrane Library, Embase, CINAHL, PubMed the Transfusion Evidence Library and using multiple clinical trials registries to 21 February 2017. Sixteen RCTs were identified: six completed (five in adult trauma patients, one pediatric burn patients) and ten ongoing trials. Of the completed trials: three were feasibility trials, comparing a FFP, platelets and RBC ratio of 1:1:1 to laboratory-guided transfusion practice [n=69], early cryoprecipitate compared to standard practice [n=41], and early fibrinogen concentrate compared to placebo [n=45]; one trial compared the effect of FFP, platelets and RBC ratio of 1:1:1 with 1:1:2 on 24-hour and 30-day mortality [n=680]; one compared whole blood to blood component therapy on 24-hour blood use [n=107]; one compared a FFP to RBC ratio of 1:1 with 1:4 [n=16]. Data from two trials were pooled in a meta-analysis for 28-day mortality because the transfusion ratios achieved were similar. Results from these two trials suggest higher transfusion ratios were associated with transfusion of more FFP and platelets without evidence of significant difference with respect to mortality or morbidity. On the limited evidence available, there is insufficient basis to recommend a 1:1:1 over a 1:1:2 ratio or standard care for adult patients with critical bleeding requiring massive transfusion.
Optimal dose, timing and ratio to red blood cells (RBC) of blood component therapy (fresh frozen plasma [FFP], platelets, cryoprecipitate or fibrinogen concentrate) to reduce morbidity and mortality in critically bleeding patients requiring massive transfusion is unknown. We performed a systematic review for randomized controlled trials (RCT) in MEDLINE, The Cochrane Library, Embase, CINAHL, PubMed the Transfusion Evidence Library and using multiple clinical trials registries to 21 February 2017. Sixteen RCTs were identified: six completed (five in adult trauma patients, one pediatric burn patients) and ten ongoing trials. Of the completed trials: three were feasibility trials, comparing a FFP, platelets and RBC ratio of 1:1:1 to laboratory-guided transfusion practice [n=69], early cryoprecipitate compared to standard practice [n=41], and early fibrinogen concentrate compared to placebo [n=45]; one trial compared the effect of FFP, platelets and RBC ratio of 1:1:1 with 1:1:2 on 24-hour and 30-day mortality [n=680]; one compared whole blood to blood component therapy on 24-hour blood use [n=107]; one compared a FFP to RBC ratio of 1:1 with 1:4 [n=16]. Data from two trials were pooled in a meta-analysis for 28-day mortality because the transfusion ratios achieved were similar. Results from these two trials suggest higher transfusion ratios were associated with transfusion of more FFP and platelets without evidence of significant difference with respect to mortality or morbidity. On the limited evidence available, there is insufficient basis to recommend a 1:1:1 over a 1:1:2 ratio or standard care for adult patients with critical bleeding requiring massive transfusion.


Related Concept Videos
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:15
Blood Transfusion
Blood Transfusion Overview
A blood transfusion is a medical procedure used to replace blood lost due to injury, surgery, or to treat conditions such as anemia or cancer. During a transfusion, donor blood is...
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady...
 01:15
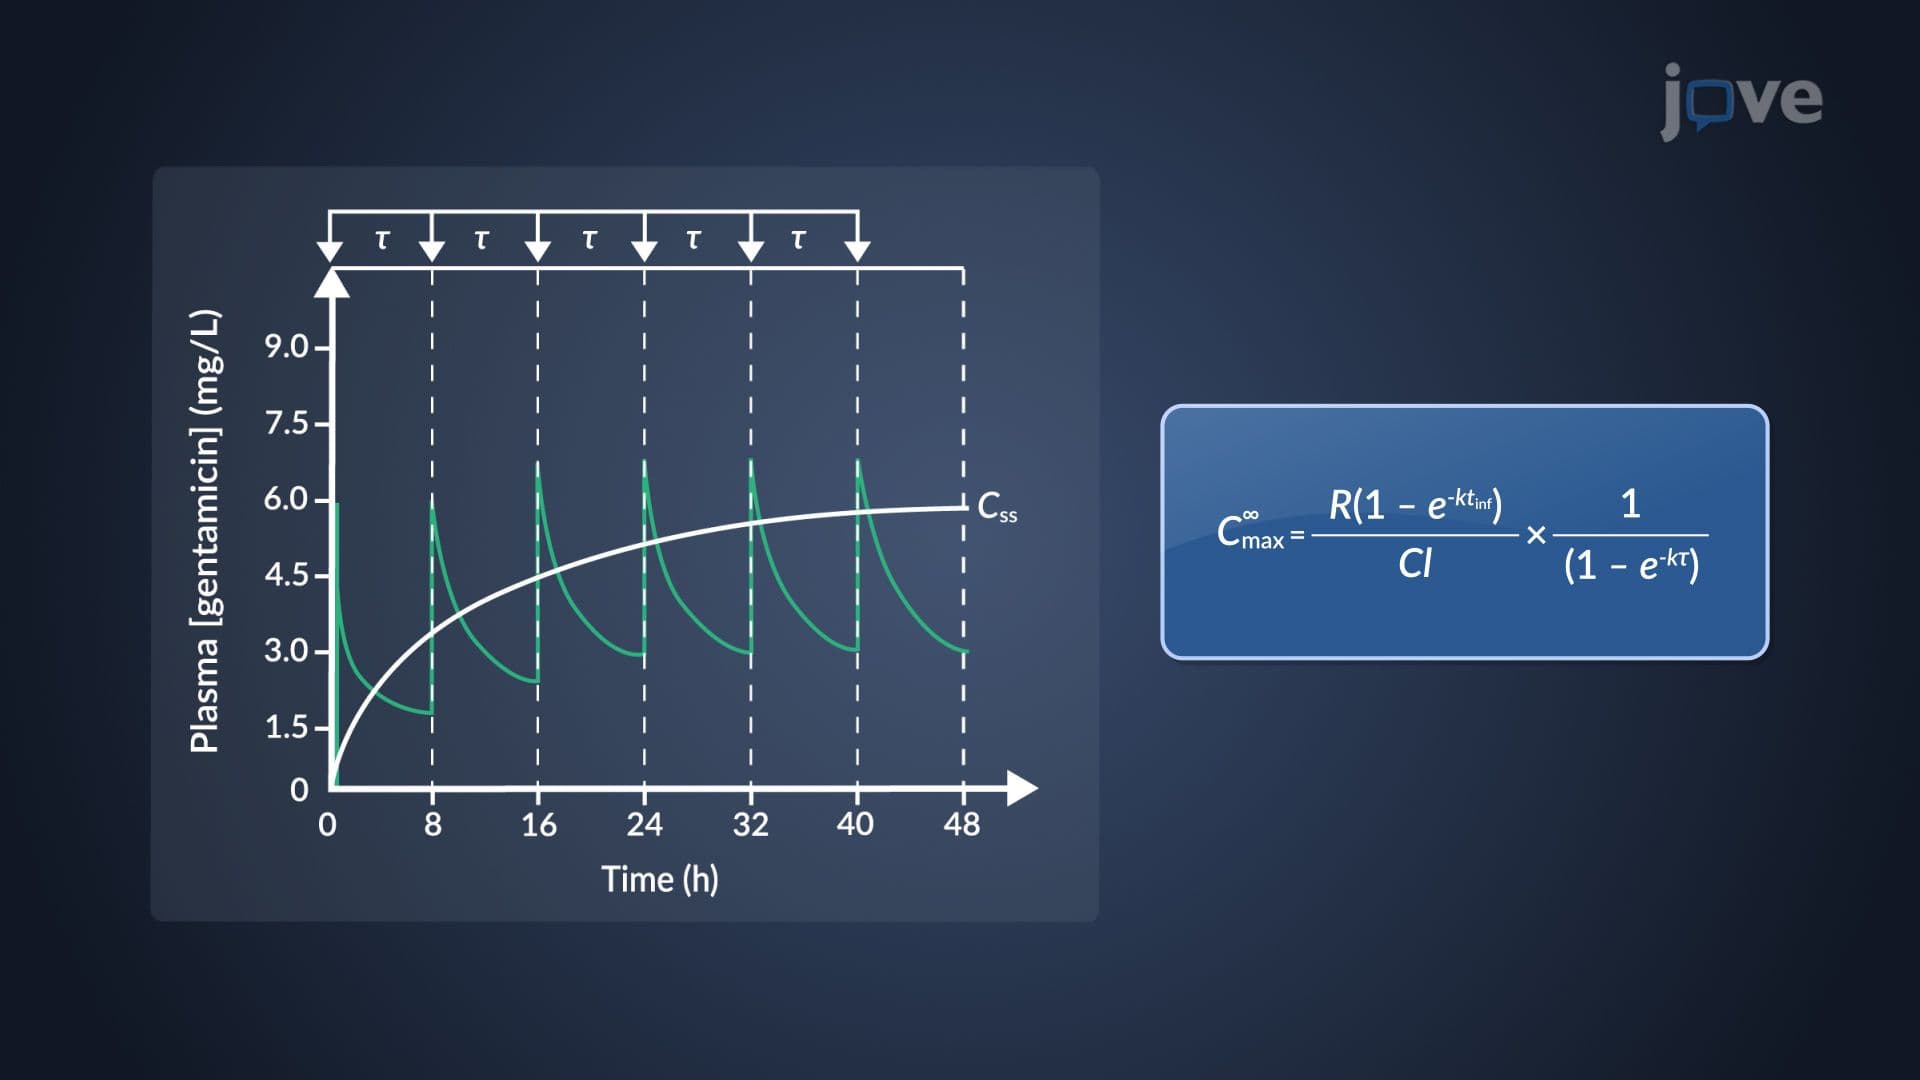
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Dosage Regimens: Designs and Approaches