Related Experiment Video
Updated: Feb 24, 2026


Separation of Immune Cell Subpopulations in Peripheral Blood Samples from Children with Infectious Mononucleosis
Published on: September 7, 2022
Familial Mediterranean fever in childhood: a single-center experience
Kenan Barut1, Sezgin Sahin1, Amra Adrovic1
1Department of Pediatric Rheumatology, Cerrahpasa Medical School, Istanbul University, İstanbul, Turkey.

Insights
Familial Mediterranean Fever (FMF) in children is often linked to the M694V mutation, which can cause severe symptoms and arthritis. Strict colchicine adherence is crucial for managing FMF and reducing amyloidosis risk.
Area of Science:
- Rheumatology
- Genetics
- Pediatrics
Background:
- Familial Mediterranean Fever (FMF) is a genetic autoinflammatory disorder.
- Understanding FMF's clinical features, genetic variations, and treatment outcomes in children is essential for effective management.
- Amyloidosis remains a significant concern in FMF patients, particularly in pediatric populations.
Purpose of the Study:
- To analyze demographic and clinical characteristics of pediatric FMF patients.
- To investigate MEFV gene mutations and their correlation with clinical manifestations and treatment response.
- To determine the current frequency of amyloidosis in children with FMF.
Main Methods:
- Retrospective evaluation of 708 pediatric FMF patients on colchicine treatment for at least six months.
- Data collection from patient records and verification through patient/parent interviews.
- Analysis of MEFV mutation variations, clinical features, and treatment outcomes, including amyloidosis and colchicine resistance.
Main Results:
- Abdominal pain, fever, and arthritis were the most common FMF manifestations.
- The M694V mutation (homozygous or heterozygous) was more frequent in patients with arthritis and chronic arthritis.
- Amyloidosis was confirmed in two patients; colchicine resistance was observed in 6.6% of cases, with M694V being the most common mutation.
- Amyloidosis frequency was lower than in previous studies, and anti-IL-1 therapy showed promise in colchicine-resistant cases.
Conclusions:
- Homozygous M694V mutation is associated with severe FMF phenotypes and worse outcomes in Turkish children.
- M694V genotype correlates with increased arthritis incidence and severity.
- Strict adherence to colchicine treatment is vital for managing FMF recurrence and preventing amyloidosis; anti-IL-1 agents offer an alternative for resistant cases.
Abstract:
The aim of this study is to present demographic and clinical features, MEFV mutation variations, and treatment response of a large number of pediatric familial Mediterranean fever (FMF) patients from a single tertiary centre. Moreover, we aimed to investigate the current outcome of FMF, namely frequency of amyloidosis in children with FMF. We evaluated 708 FMF patients who were followed up in our clinic and who were under colchicine treatment for at least 6 months. The data were recorded from patient records and also verified by negotiations with patients and parents. The male/female proportion of the cohort was 1.05/1 (n = 362/346). Abdominal pain (89.5%, n = 634) was the most common manifestation of FMF episodes, followed by fever (88.8%, n = 629) and arthritis (40.7%, n = 288). However, arthritis in 23 (8%) of the 288 cases was not self-limited; and they subsequently diagnosed with juvenile idiopathic arthritis in addition to FMF. Homozygote or heterozygote M694V mutation was more frequent in patients with arthritis (63.2%) and chronic arthritis (69.6%) than the whole cohort (53.8%). Erythrocyte sedimentation rate and CRP level were in high levels even during attack-free period in 13.9% (n = 97/697) and 11% (n = 78/670) of the patients, respectively. Proteinuria was found in ten patients (1.4%). Amyloidosis was confirmed by renal biopsy in only two of these cases who were homozygous for M694V and compound heterozygous for M694V/M680I. 47 (6.6%) subjects were considered as colchicine resistant. Homozygote M694V mutation was the most frequent mutation in those resistant cases (63.8%, n = 30), followed by compound heterozygote mutation of M694V/M680I (6.3%, n = 3). Homozygous M694V mutation are still the most frequent mutation and associated with the most severe clinical picture and the worst outcome in Turkish children. M694V genotype seems to be more frequently associated with arthritis as well as with chronic arthritis than other genotypes. Recurrence of FMF episodes as well as amyloidosis could only be managed via strict compliance to colchicine treatment. Frequency of amyloidosis significantly decreased compared to the previous studies. A favorable outcome could be obtained with the anti IL-1 in colchicine-resistant FMF patients.
More Related Videos
 08:04
Development of an IFN-γ ELISpot Assay to Assess Varicella-Zoster Virus-specific Cell-mediated Immunity Following Umbilical Cord Blood Transplantation
Published on: July 9, 2014
 08:07
Single Myofiber Isolation and Culture from a Murine Model of Emery-Dreifuss Muscular Dystrophy in Early Post-Natal Development
Published on: July 1, 2020
Related Concept Videos
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:26
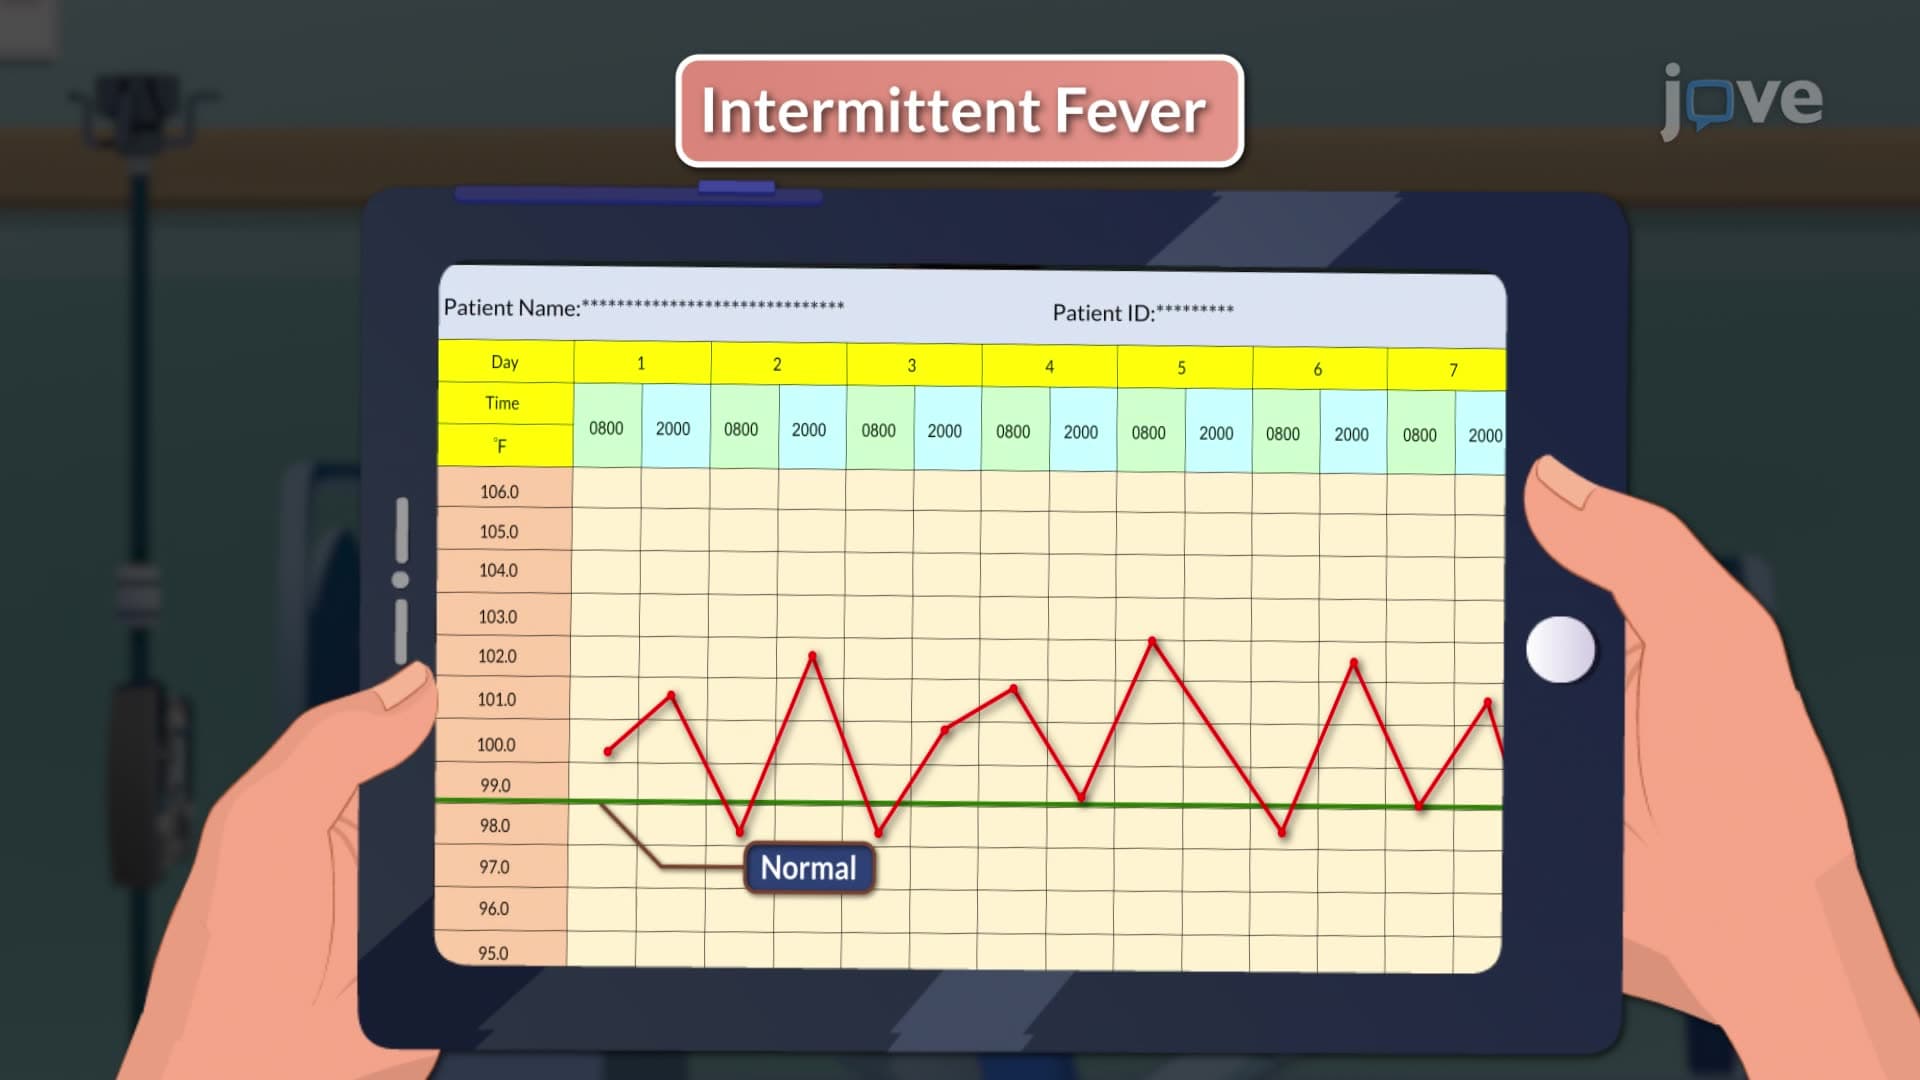
Patterns of Fever
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:14
Myocarditis III: Medical Management
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:21
Myocarditis I: Introduction