Related Experiment Video
Updated: Feb 24, 2026

Proton Therapy Delivery and Its Clinical Application in Select Solid Tumor Malignancies
Published on: February 6, 2019
Impact of respiratory motion on variable relative biological effectiveness in 4D-dose distributions of proton therapy
Silke Ulrich1,2, Hans-Peter Wieser1,2, Wenhua Cao3
1a Department of Medical Physics in Radiation Therapy , German Cancer Research Center (DKFZ) , Heidelberg , Germany.

Background:
Organ motion during radiation therapy with scanned protons leads to deviations between the planned and the delivered physical dose. Using a constant relative biological effectiveness (RBE) of 1.1 linearly maps these deviations into RBE-weighted dose. However, a constant value cannot account for potential nonlinear variations in RBE suggested by variable RBE models. Here, we study the impact of motion on recalculations of RBE-weighted dose distributions using a phenomenological variable RBE model.
Material And Methods:
4D-dose calculation including variable RBE was implemented in the open source treatment planning toolkit matRad. Four scenarios were compared for one field and two field proton treatments for a liver cancer patient assuming (α∕β)x = 2 Gy and (α∕β)x = 10 Gy: (A) the optimized static dose distribution with constant RBE, (B) a static recalculation with variable RBE, (C) a 4D-dose recalculation with constant RBE and (D) a 4D-dose recalculation with variable RBE. For (B) and (D), the variable RBE was calculated by the model proposed by McNamara. For (C), the physical dose was accumulated with direct dose mapping; for (D), dose-weighted radio-sensitivity parameters of the linear quadratic model were accumulated to model synergistic irradiation effects on RBE.
Results:
Dose recalculation with variable RBE led to an elevated biological dose at the end of the proton field, while 4D-dose recalculation exhibited random deviations everywhere in the radiation field depending on the interplay of beam delivery and organ motion. For a single beam treatment assuming (α∕β)x = 2 Gy, D95% was 1.98 Gy (RBE) (A), 2.15 Gy (RBE) (B), 1.81 Gy (RBE) (C) and 1.98 Gy (RBE) (D). The homogeneity index was 1.04 (A), 1.08 (B), 1.23 (C) and 1.25 (D).
Conclusion:
For the studied liver case, intrafractional motion did not reduce the modulation of the RBE-weighted dose postulated by variable RBE models for proton treatments.

Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:30
Application of Integration: Problem Solving
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:15
Respiratory Volumes
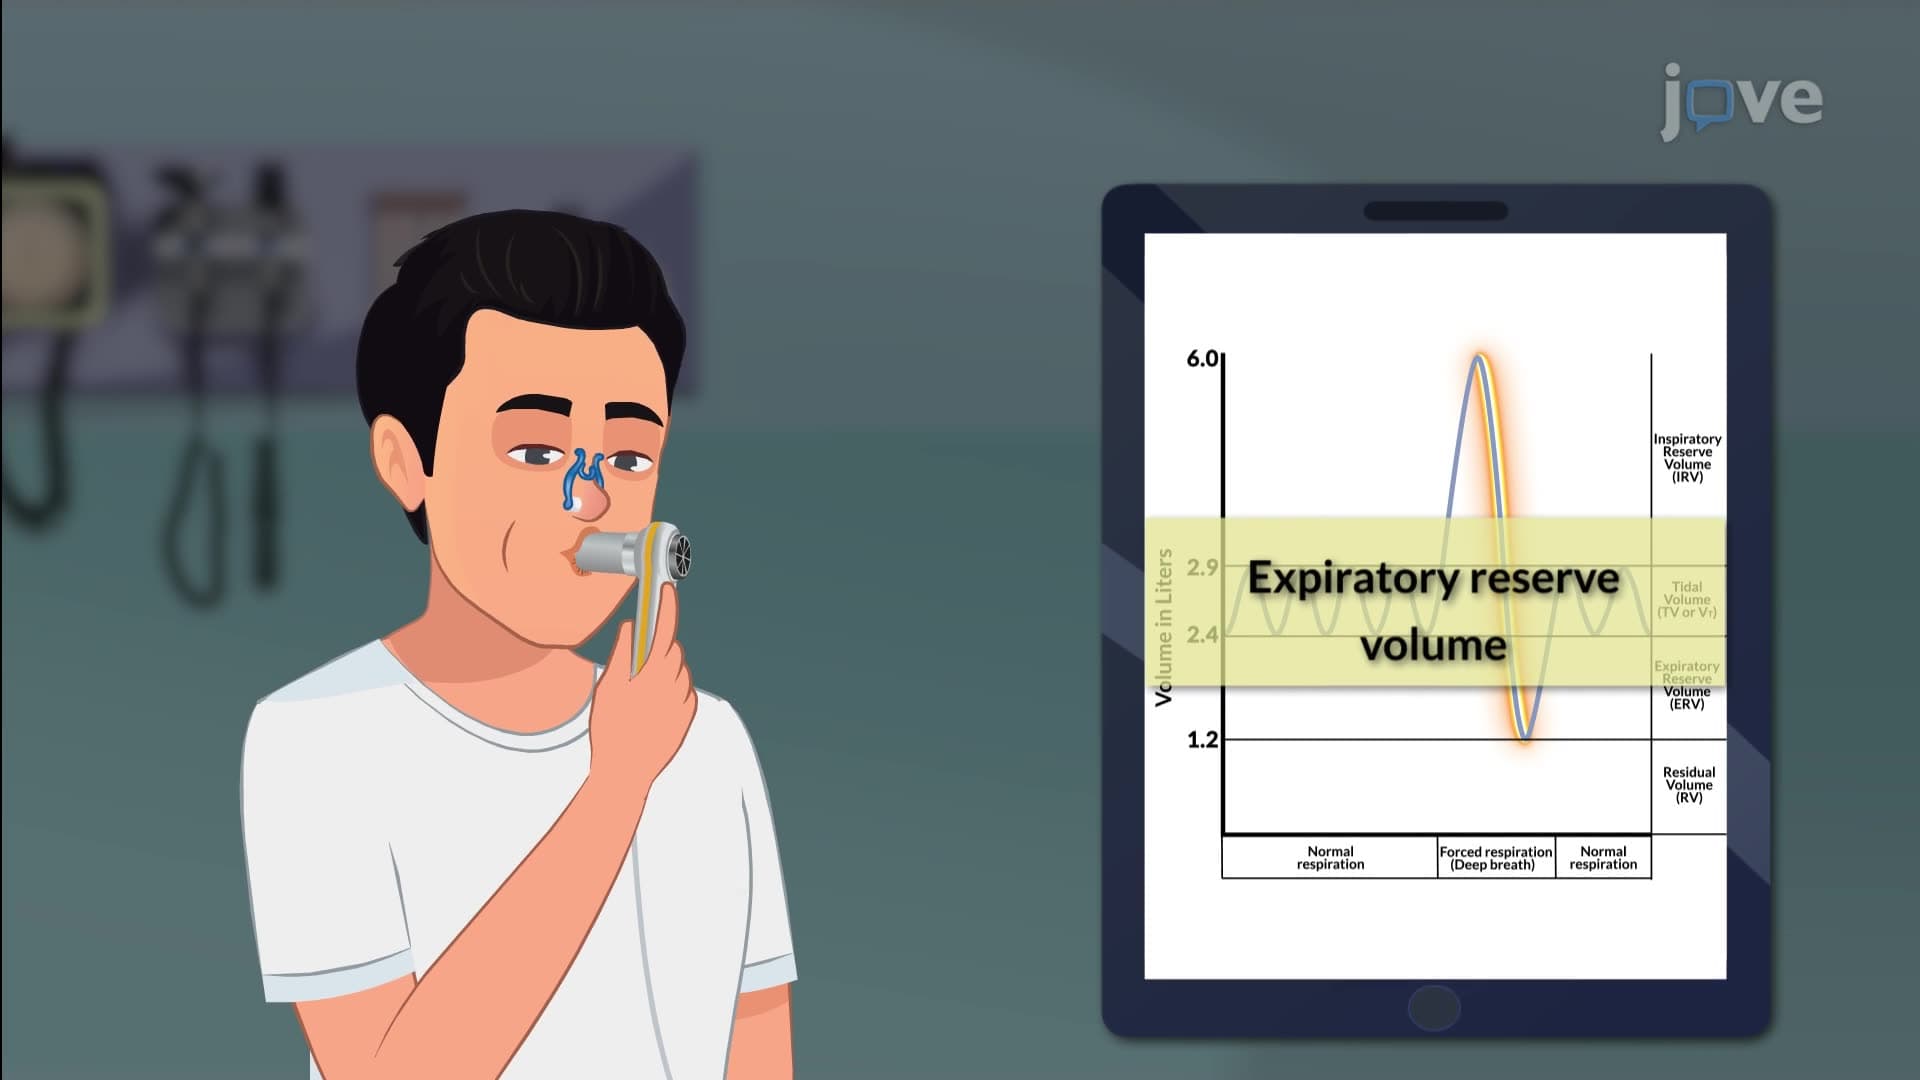
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Factors Affecting Respiration
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...