Related Experiment Video
Updated: Feb 24, 2026


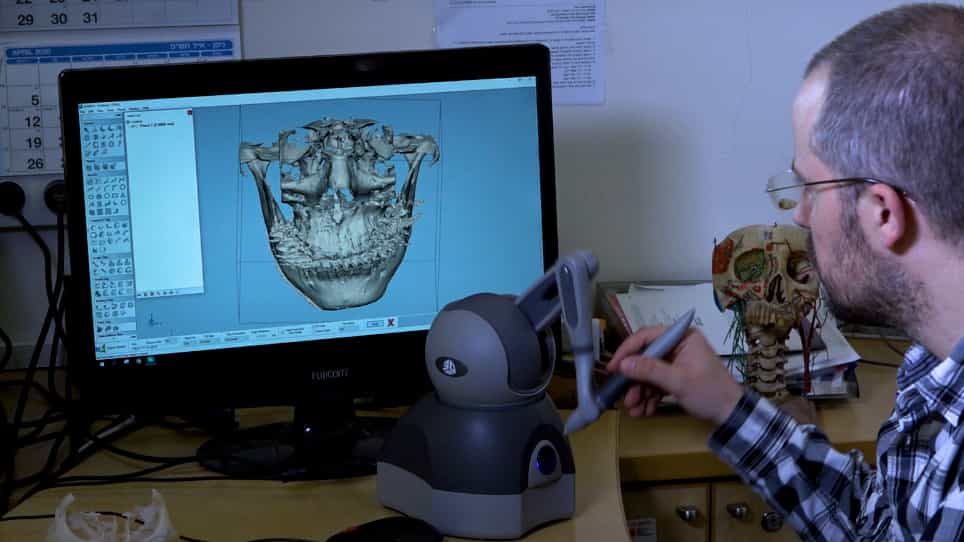
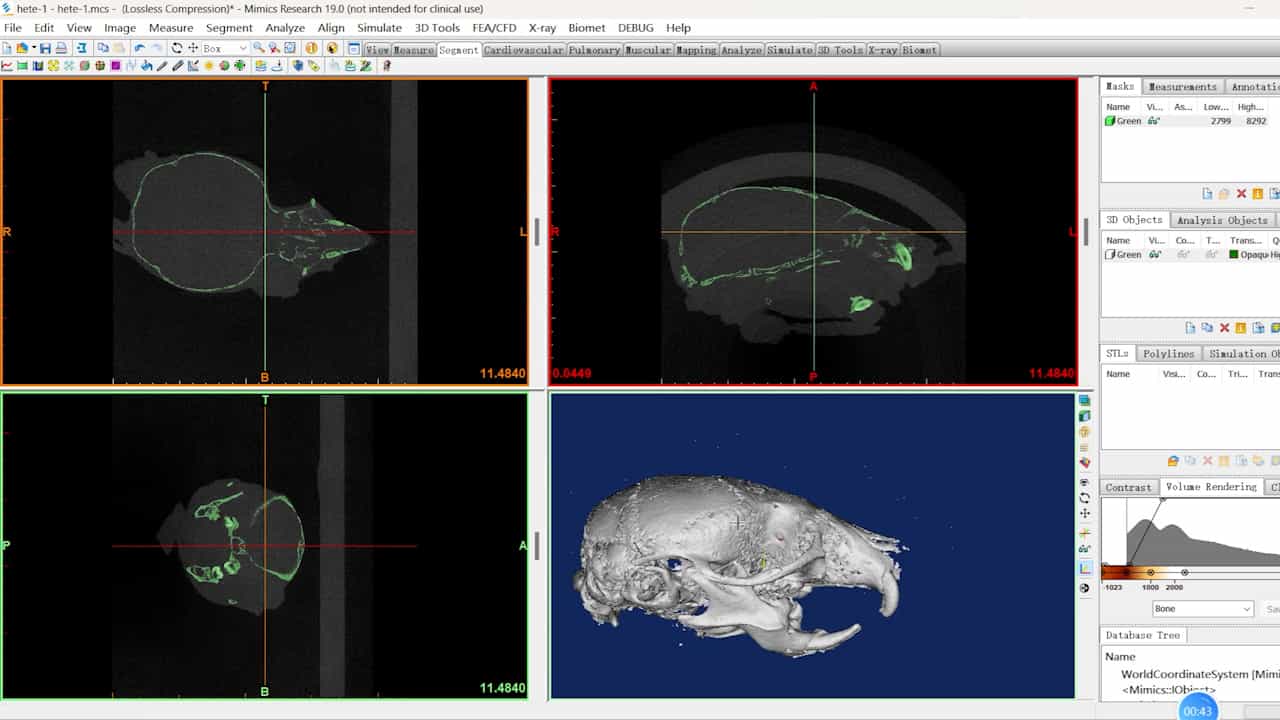
Midface Hypoplasia and Cranial Base Morphology in Syndromic Craniosynostosis: A Comparative Analysis Study Using a Predictive Regression Model
Published on: November 4, 2025
Positional Skull Deformities

Insights
Positional skull deformities in infants are common and influenced by various risk factors. Early intervention through parent education, positioning, and physical therapy is key for effective treatment.
Area of Science:
- Pediatric Neurology
- Developmental Pediatrics
Background:
- Skull deformities, such as occipital flattening, are common in infants, particularly within the first six months of life.
- These conditions raise questions regarding differential diagnosis and appropriate treatment strategies.
Purpose of the Study:
- To review current understanding of risk factors for positional skull deformities.
- To outline current diagnostic assessments and treatment options for these conditions.
Main Methods:
- Selective literature review based on current studies and guidelines.
- Inclusion of recommendations from the German Society for Pediatric Neurology and American guidelines on positional plagiocephaly.
Main Results:
- Pre-, peri-, and postnatal factors contribute to positional skull deformities.
- Diagnosis relies on clinical features, with ultrasonography as an adjunct for unclear cases.
- Key interventions include parent education on infant positioning, physical therapy for limited motion, and orthoses for severe cases.
Conclusions:
- Comprehensive parental education on preventive and therapeutic measures is crucial.
- Treatment should be initiated early and tailored to the severity of the deformity.
- Reassurance regarding supine sleeping positions is important despite parental concerns.
Background:
Especially in the first 6 months of life, skull deformities manifesting as a uni- or bilateral flattening of the occiput often give rise to questions of differential diagnosis and potential treatment. In this review, the authors summarize the current understanding of risk factors for this condition, and the current state of the relevant diagnostic assessment and options for treatment.
Methods:
The recommendations given in this selective review of the literature are based on current studies and on existing guidelines on the prevention of sudden infant death, the recommendations of the German Society for Pediatric Neurology (Deutsche Gesellschaft für Neuropädiatrie), and the American guidelines on the treatment of positional plagiocephaly in infancy.
Results:
Pre-, peri-, and postnatal risk factors can contribute to the development of positional skull deformities. These deformities can be diagnosed and classified on the basis of their clinical features, supplemented in unclear cases by ultrasonography of the cranial sutures. The putative relationship between positional skull deformities and developmental delay is currently debated. The main preventive and therapeutic measure is parent education to foster correct positioning habits (turning of the infant to the less favored side; prone positioning on occasion when awake) and beneficial stimulation of the infant (to promote lying on the less favored side). If the range of motion of the head is limited, physiotherapy is an effective additional measure. In severe or refractory cases, a skull orthosis (splint) may be useful.
Conclusion:
The parents of children with positional skull deformities should be comprehensively informed about the necessary preventive and therapeutic measures. Treatment should be initiated early and provided in graded fashion, according to the degree of severity of the problem. Parental concern about the deformity should not be allowed to lead to a rejection of the reasonable recommendation for a supine sleeping position.
Related Concept Videos
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:08
Overview of the Skull
The cranial vault surrounds and protects the brain and houses the middle and inner ear structures. This cavity is bounded superiorly by the rounded top of the skull, which...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into ...
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...