Related Experiment Video
Updated: Feb 23, 2026


Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Improving the Safety and Functionality of an Artificial Pancreas System for Use in Younger Children: Input from
Rachel Gildersleeve1, Sara L Riggs2, Daniel R Cherñavvsky1,3
11 Center for Diabetes Technology, University of Virginia , Charlottesville, Virginia.

Insights
Pediatric endocrinologists and parents desire artificial pancreas (AP) systems for young children with type 1 diabetes (T1D). They emphasize the need for modified AP systems with enhanced safety and customization features for this age group.
Area of Science:
- Pediatric endocrinology
- Biomedical engineering
- Diabetes technology
Background:
- Artificial pancreas (AP) systems are primarily designed for teens and adults.
- Younger children with type 1 diabetes (T1D) could benefit from AP systems with enhanced safety and support.
- Existing AP technology requires modifications for safe and effective use in children aged 5-8 years.
Purpose of the Study:
- To explore the needs and preferences of pediatric endocrinologists and parents regarding AP systems for young children with T1D.
- To identify necessary modifications for adapting adult AP systems for use in children aged 5-8 years.
- To gather insights on safety features, user interface, and functionality for a pediatric AP system.
Main Methods:
- Four focus groups were conducted with five pediatric endocrinologists and 15 parents of children aged 5-8 years with T1D.
- Discussions focused on current diabetes technology use, acceptance of AP systems, and required modifications for younger children.
- Qualitative data on desired features and safety considerations were collected.
Main Results:
- Participants suggested child-specific functionalities, including customizable access levels with passcodes for different caregivers and the child.
- Key features requested include simplified meal interfaces, automated exercise modes, spoken/dictated messaging, emergency contacts, and remote monitoring.
- Suggestions also included animated glucose monitoring displays, gamification elements, and comprehensive training programs.
Conclusions:
- Pediatric endocrinologists and parents are highly receptive to AP systems for young children but stress the importance of system modifications.
- A tailored AP system is crucial to address the unique safety, communication, and management needs of children aged 5-8 years with T1D.
- Flexible and customizable AP systems are essential for effective T1D management in this pediatric population.
Background:
Artificial pancreas (AP) systems have initially been designed for and tested in teens and adults, but there is evidence that an AP system with additional support and safety systems could greatly benefit younger children with type 1 diabetes (T1D).
Subjects And Methods:
Five pediatric endocrinologists and 15 parents of children aged 5-8 years with T1D participated in a total of four focus groups. Focus groups investigated current diabetes technology use and acceptance, as well as possible modifications to the current adult AP system, which would allow for safe and successful use in younger children. Modifications discussed include child-specific functionality for input tasks, safety features, and monitoring capabilities.
Results:
Participant suggestions included the following: passcodes for differential access to AP features by parents, ancillary caregivers, and the child; preset early, intermediate, and advanced child access categories; maximal customization for general and alarm settings; simplified meal screens utilizing the AP' corrective blood glucose (BG) ability; automated exercise mode; spoken and dictated messaging capabilities; emergency contacts; treatment instructions for the child and caregiver; remote monitoring website and application; animated continuous glucose monitor BG trace; gamification, such as rewarding diabetes-friendly behaviors; and comprehensive training of all individuals involved in the child's diabetes care.
Conclusion:
Parents and physicians were eager for AP applications to be available for younger children, but stressed that a modified system could better serve this group's needs for safety and improved diabetes-related communication. The diverse and emerging needs of 5-8-year olds require flexible and customizable systems for T1D management.


Related Concept Videos
 01:25
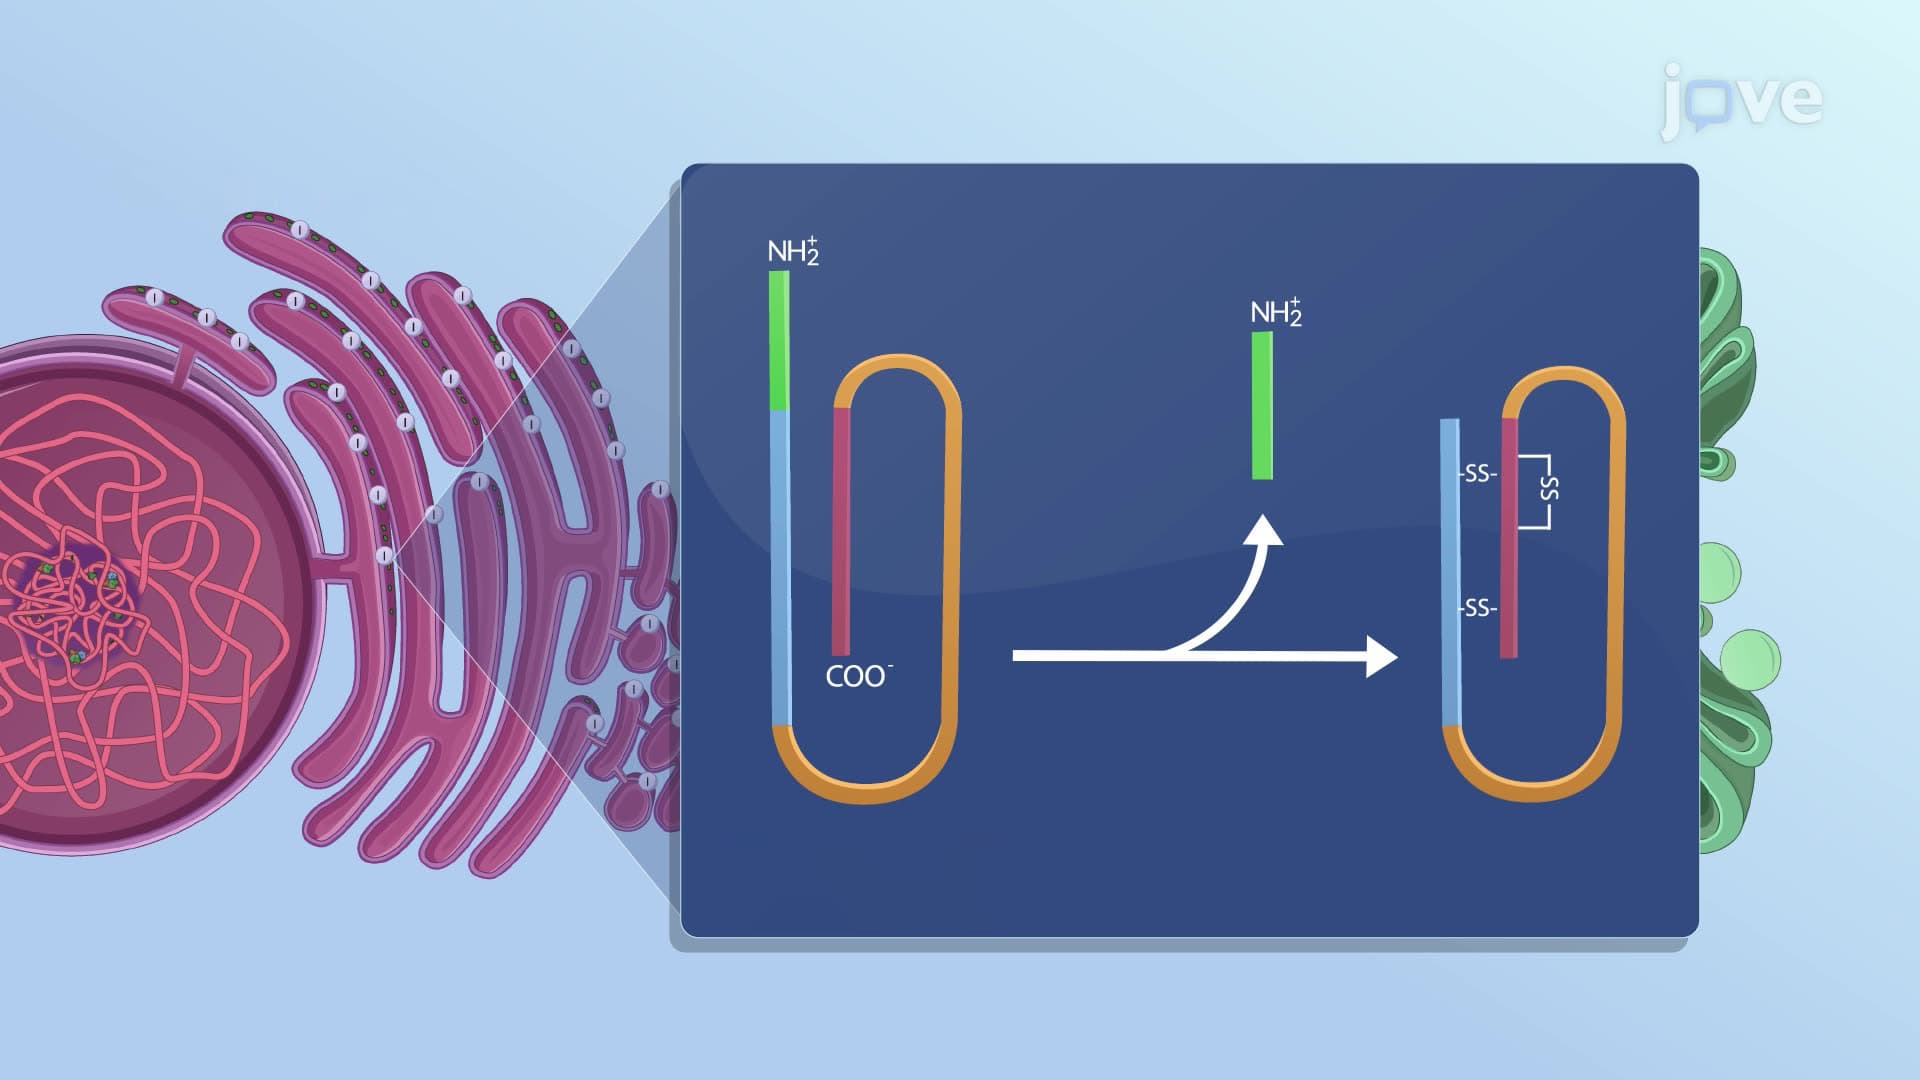
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption