Related Experiment Video
Updated: Feb 23, 2026

Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Nebulized Versus IV Amikacin as Adjunctive Antibiotic for Hospital and Ventilator-Acquired Pneumonia Postcardiac
Nehal A Hassan1, Faten Farid Awdallah2, Maggie M Abbassi3
1Clinical Pharmacy, National Heart Institute, Giza, Egypt.

Objective:
Nebulized antibiotics offer high efficacy due to significant local concentrations and safety with minimal blood levels. This study evaluates the efficacy and nephrotoxicity of nebulized versus IV amikacin in postcardiothoracic surgical patients with nosocomial pneumonia caused by multidrug-resistant Gram- negative bacilli.
Design:
Prospective, randomized, controlled study on surgical patients divided into two groups.
Setting:
Postcardiac surgery ICU.
Interventions:
The first gtroup was administered IV amikacin 20 mg/kg once daily. The second group was prescribed amikacin nebulizer 400 mg twice daily. Both groups were co-administered IV piperacillin/tazobactam empirically.
Patients:
Recruited patients were diagnosed by either hospital-acquired pneumonia or ventilator-associated pneumonia where 56 (42.1%) patients were diagnosed with hospital-acquired pneumonia, 51 (38.34%) patients were diagnosed with early ventilator-associated pneumonia, and 26 (19.54%) patients with late ventilator-associated pneumonia.
Measurements And Main Results:
Clinical cure in both groups assessed on day 7 of treatment was the primary outcome. Efficacy was additionally evaluated through assessing the length of hospital stay, ICU stay, days on amikacin, days on mechanical ventilator, mechanical ventilator-free days, days to reach clinical cure, and mortality rate. Lower nephrotoxicity in the nebulized group was observed through significant preservation of kidney function (p < 0.001). Although both groups were comparable regarding length of hospital stay, nebulizer group showed shorter ICU stay (p = 0.010), lower number of days to reach complete clinical cure (p = 0.001), fewer days on mechanical ventilator (p = 0.035), and fewer days on amikacin treatment (p = 0.022).
Conclusion:
Nebulized amikacin showed better clinical cure rates, less ICU stay, and fewer days to reach complete recovery compared to IV amikacin for surgical patients with nosocomial pneumonia. It is also a less nephrotoxic option associated with less deterioration in kidney function.
Insights
Nebulized amikacin demonstrated superior efficacy and reduced nephrotoxicity compared to intravenous administration in postcardiac surgery patients with nosocomial pneumonia. This approach led to faster recovery and shorter intensive care unit stays.
Area of Science:
- Pulmonary Medicine
- Infectious Diseases
- Critical Care Medicine
Background:
- Nosocomial pneumonia in postcardiac surgery patients presents a significant challenge, often caused by multidrug-resistant Gram-negative bacilli.
- Intravenous (IV) antibiotics achieve systemic concentrations, potentially leading to toxicity, while nebulized antibiotics offer localized high concentrations with minimal systemic absorption.
Purpose of the Study:
- To evaluate the efficacy and nephrotoxicity of nebulized amikacin compared to IV amikacin in postcardiac surgery patients with nosocomial pneumonia.
- To assess clinical cure rates, length of hospital and ICU stay, and renal function preservation.
Main Methods:
- A prospective, randomized, controlled study was conducted in a postcardiac surgery ICU.
- Patients received either IV amikacin (20 mg/kg once daily) or nebulized amikacin (400 mg twice daily), both groups co-administered IV piperacillin/tazobactam.
- Efficacy outcomes included clinical cure, ICU stay, mechanical ventilator days, and mortality; nephrotoxicity was assessed by kidney function preservation.
Main Results:
- Nebulized amikacin showed significantly better preservation of kidney function (p < 0.001) compared to IV amikacin, indicating lower nephrotoxicity.
- The nebulizer group experienced a shorter ICU stay (p = 0.010), fewer days to clinical cure (p = 0.001), and reduced mechanical ventilator days (p = 0.035).
- Clinical cure rates were comparable, but recovery was faster in the nebulized amikacin group.
Conclusions:
- Nebulized amikacin is a more effective and less nephrotoxic treatment option for nosocomial pneumonia in postcardiac surgery patients compared to IV administration.
- This delivery method results in improved clinical outcomes, including shorter ICU stays and faster recovery.
- Nebulized amikacin offers a promising alternative for managing challenging infections in critically ill patients.
More Related Videos
 06:10
Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
 09:17
A Robust Pneumonia Model in Immunocompetent Rodents to Evaluate Antibacterial Efficacy against S. pneumoniae, H. influenzae, K. pneumoniae, P. aeruginosa or A. baumannii
Published on: January 2, 2017
Related Concept Videos
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:23
Acute Respiratory Failure-IV
 01:30
Pneumonia III: Complications and Assessment
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:20
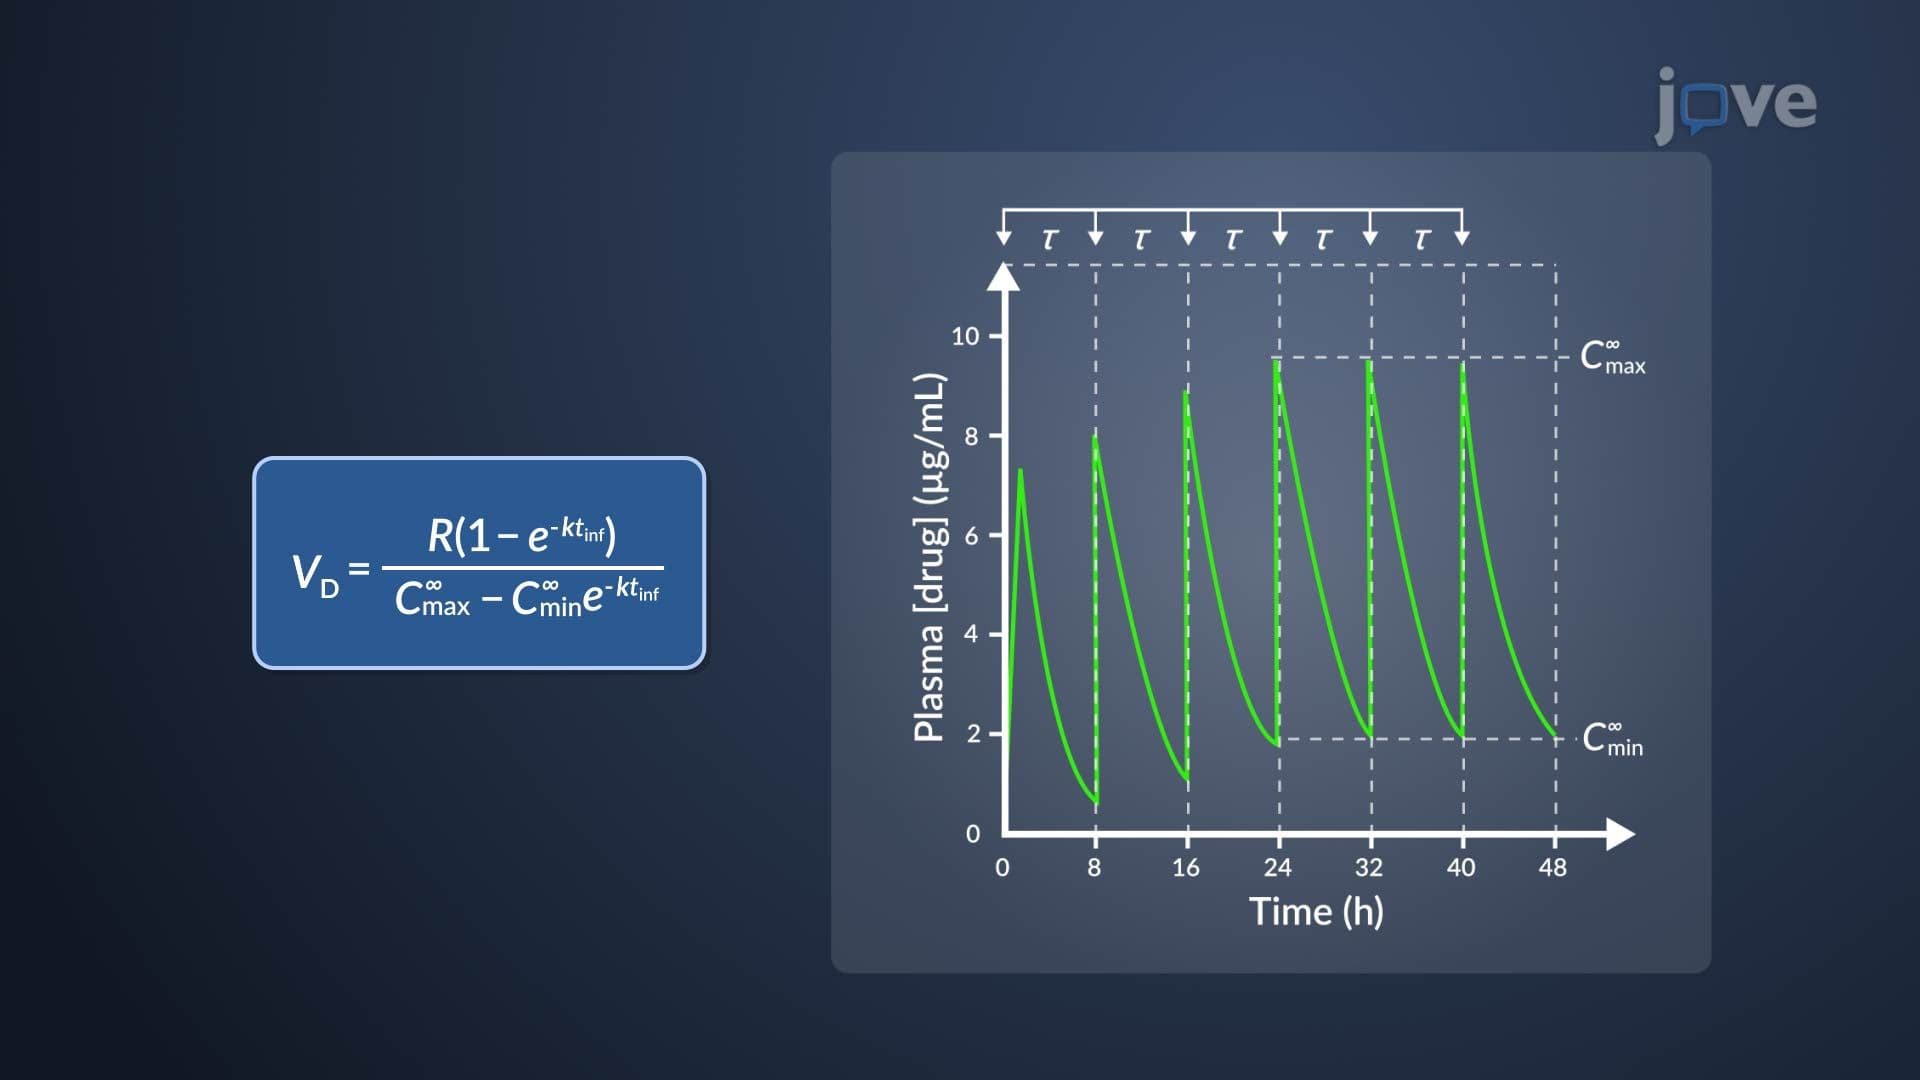
Estimation of k and VD of Aminoglycosides