Related Experiment Video
Updated: Feb 23, 2026

Intracellular Phosphoflow Cytometry of Acute Myeloid Leukemia Patient-Derived Xenotransplants
Published on: June 6, 2025
FLAG-Ida Regimen as Bridge Therapy to Allotransplantation in Refractory/Relapsed Acute Myeloid Leukemia Patients
Mario Delia1, Domenico Pastore1, Paola Carluccio1
1Hematology and Bone Marrow Transplantation Unit, Department of Emergency and Organ Transplantation, University of Bari, Bari, Italy.

Background:
Patients with primary refractory or first relapse acute myeloid leukemia (AML) are considered to have worse clinical outcomes after treatment. For these patients, the achievement of complete remission appears crucial for them to be able to undergo allotransplantation, which might be the only possible treatment.
Patients And Methods:
We used the FLAG-Ida (fludarabine, cytarabine [cytosine arabinoside], granulocyte colony-stimulating factor, idarubicin) regimen in patients with primary refractory/first relapse AML as a bridge to transplantation. We studied its efficacy in terms of overall response and overall survival to assess which variables (age, lactate dehydrogenase, bone marrow blast count, peripheral blood blast count, platelet count, white blood cell count, de novo or secondary AML, molecular-cytogenetic risk, duration of response, and relapsed or refractory disease) might have an effect on outcome.
Results:
We analyzed the data from 108 consecutive adult patients (52 males, 66 females; median age, 49 years; range, 17-72 years) with newly diagnosed AML refractory to standard induction regimens or relapse after first complete remission, who had received the FLAG-Ida protocol as salvage therapy from January 2005 to December 2015. An overall response was achieved in 48 patients (44%). On multivariate analysis, the variables with a positive effect on the response rate were molecular-cytogenetic risk (P = .009), duration of first response in relapsed AML (P = .003), AML status (relapsed or refractory; P = .047), and peripheral blood blast count (P = .016). On multivariate analysis, overall survival was significantly associated with FLAG-Ida response (hazard ratio, 0.343; P = .001) and receipt of allotransplantation (hazard ratio, 0.277; P < .001).
Conclusion:
Our data seem to confirm the value of FLAG-Ida in this setting and might suggest its best usage as bridge therapy for patients awaiting allotransplantation.
More Related Videos
 11:55
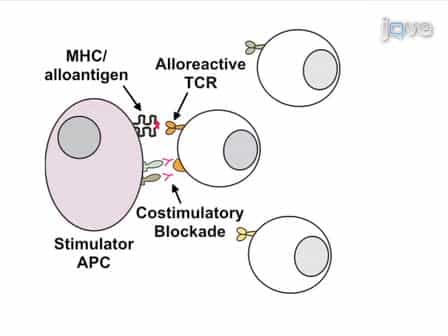
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
 04:36
Comet Assay to Quantify DNA Damage in FLT3 Mutant-expressing 32D Cells after Exposure to Type I and Type II FLT3 Inhibitors
Published on: October 17, 2025
