Related Experiment Video
Updated: Feb 23, 2026


Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Effects of Intensive Systolic Blood Pressure Control on Kidney and Cardiovascular Outcomes in Persons Without Kidney
Srinivasan Beddhu1, Michael V Rocco1, Robert Toto1
1From University of Utah School of Medicine, Salt Lake City, Utah; Wake Forest School of Medicine, Winston-Salem, North Carolina; University of Texas Southwestern Medical Center, Dallas, Texas; Ohio State University, Columbus, Ohio; University of Pennsylvania, Philadelphia, Pennsylvania; University of Minnesota, Minneapolis, Minnesota; National Institute of Diabetes and Digestive and Kidney Diseases, Bethesda, Maryland; University of Illinois at Chicago, Chicago, Illinois; VA Medical Center, Washington, DC; Case Western Reserve University, Cleveland, Ohio; University of California, Los Angeles, Los Angeles, California; VA Medical Center, Albuquerque, New Mexico; VA Medical Center, Memphis, Tennessee; and Tulane University School of Public Health and Tropical Medicine, New Orleans, Louisiana.

Background:
The public health significance of the reported higher incidence of chronic kidney disease (CKD) with intensive systolic blood pressure (SBP) lowering is unclear.
Objective:
To examine the effects of intensive SBP lowering on kidney and cardiovascular outcomes and contrast its apparent beneficial and adverse effects.
Design:
Subgroup analyses of SPRINT (Systolic Blood Pressure Intervention Trial). (ClinicalTrials.gov: NCT01206062).
Setting:
Adults with high blood pressure and elevated cardiovascular risk.
Participants:
6662 participants with a baseline estimated glomerular filtration rate (eGFR) of at least 60 mL/min/1.73 m2.
Intervention:
Random assignment to an intensive or standard SBP goal (120 or 140 mm Hg, respectively).
Measurements:
Differences in mean eGFR during follow-up (estimated with a linear mixed-effects model), prespecified incident CKD (defined as a >30% decrease in eGFR to a value <60 mL/min/1.73 m2), and a composite of all-cause death or cardiovascular event, with surveillance every 3 months.
Results:
The difference in adjusted mean eGFR between the intensive and standard groups was -3.32 mL/min/1.73 m2 (95% CI, -3.90 to -2.74 mL/min/1.73 m2) at 6 months, was -4.50 mL/min/1.73 m2 (CI, -5.16 to -3.85 mL/min/1.73 m2) at 18 months, and remained relatively stable thereafter. An incident CKD event occurred in 3.7% of participants in the intensive group and 1.0% in the standard group at 3-year follow-up, with a hazard ratio of 3.54 (CI, 2.50 to 5.02). The corresponding percentages for the composite of death or cardiovascular event were 4.9% and 7.1% at 3-year follow-up, with a hazard ratio of 0.71 (CI, 0.59 to 0.86).
Limitation:
Long-term data were lacking.
Conclusion:
Intensive SBP lowering increased risk for incident CKD events, but this was outweighed by cardiovascular and all-cause mortality benefits.
Primary Funding Source:
National Institutes of Health.


Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:30
Blood Pressure
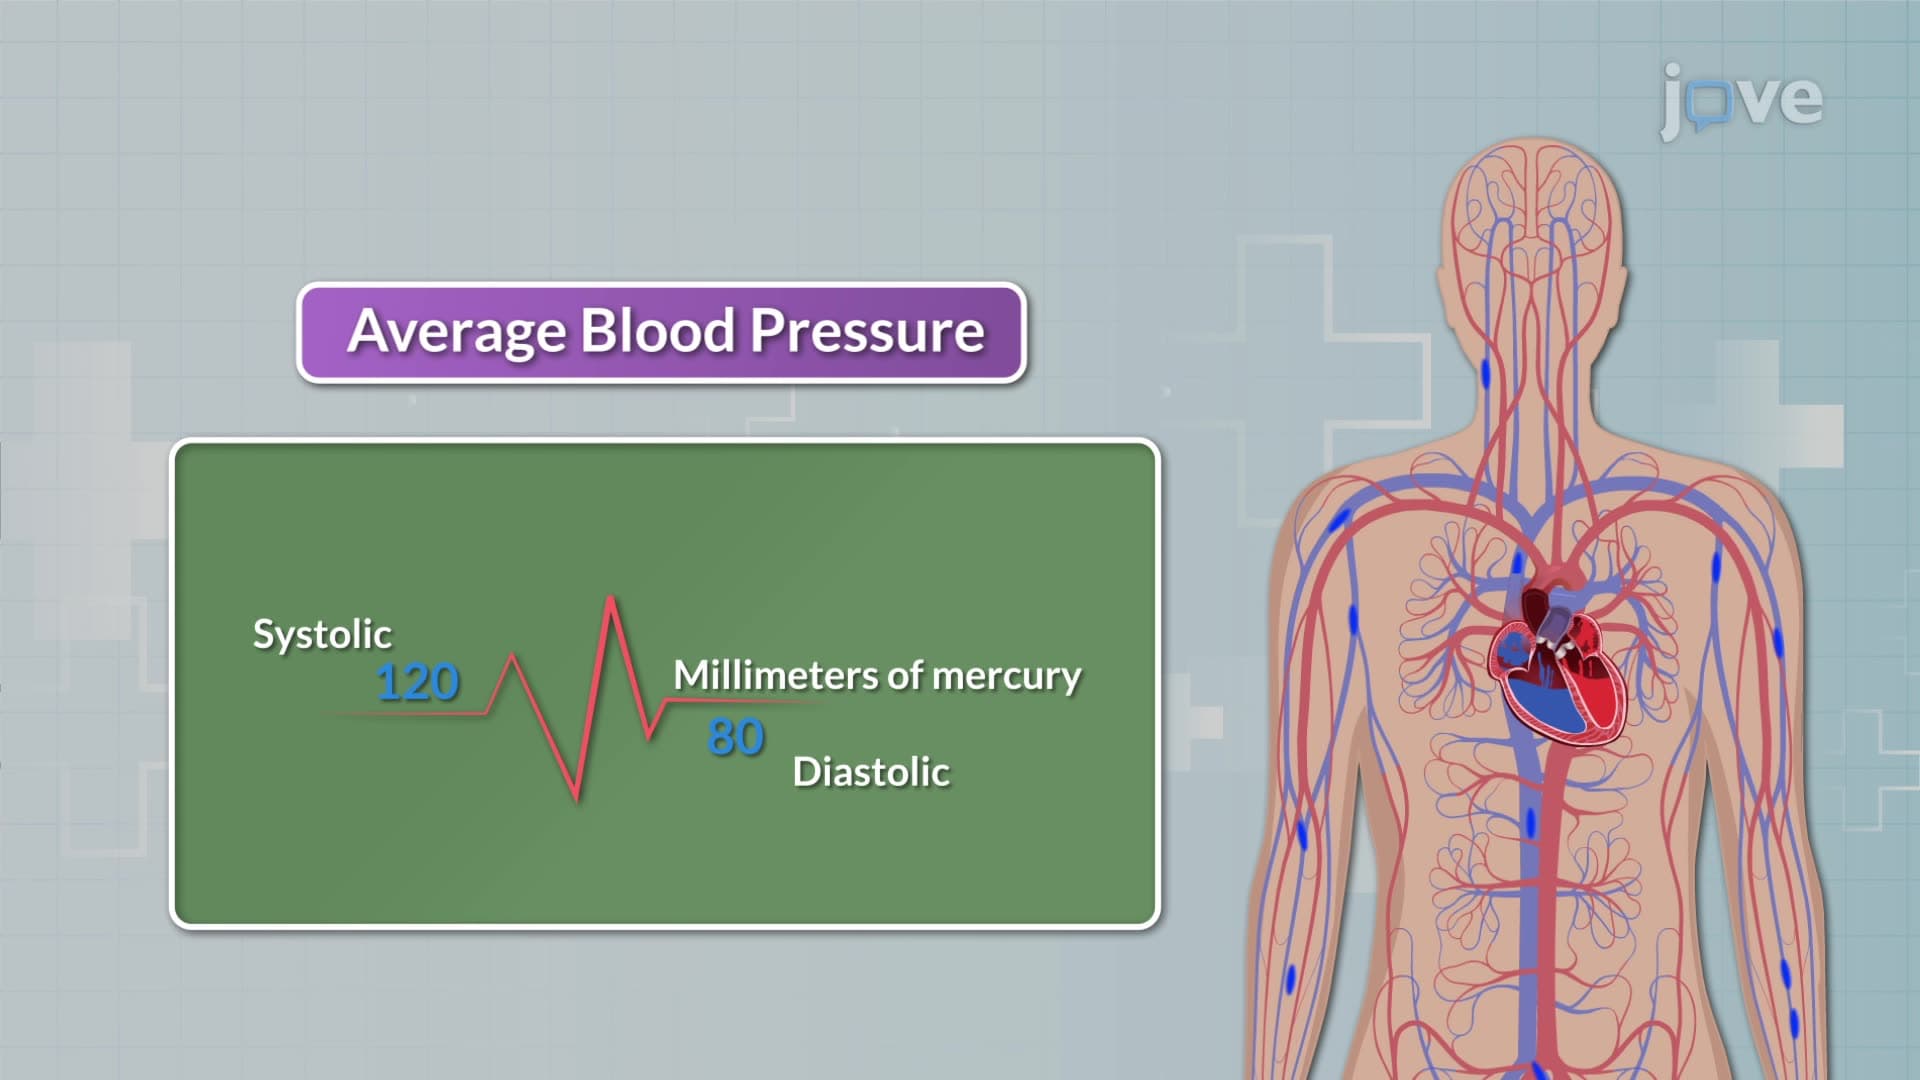
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:24
Blood Pressure
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors