

[Extreme obesity-particular aspect of invasive and noninvasive ventilation]
1Klinik für Innere Medizin und Internistische Intensivmedizin, EVK Oldenburg, Steinweg 13-17, 26122, Oldenburg, Deutschland. matthias.deppe@evangelischeskrankenhaus.de.

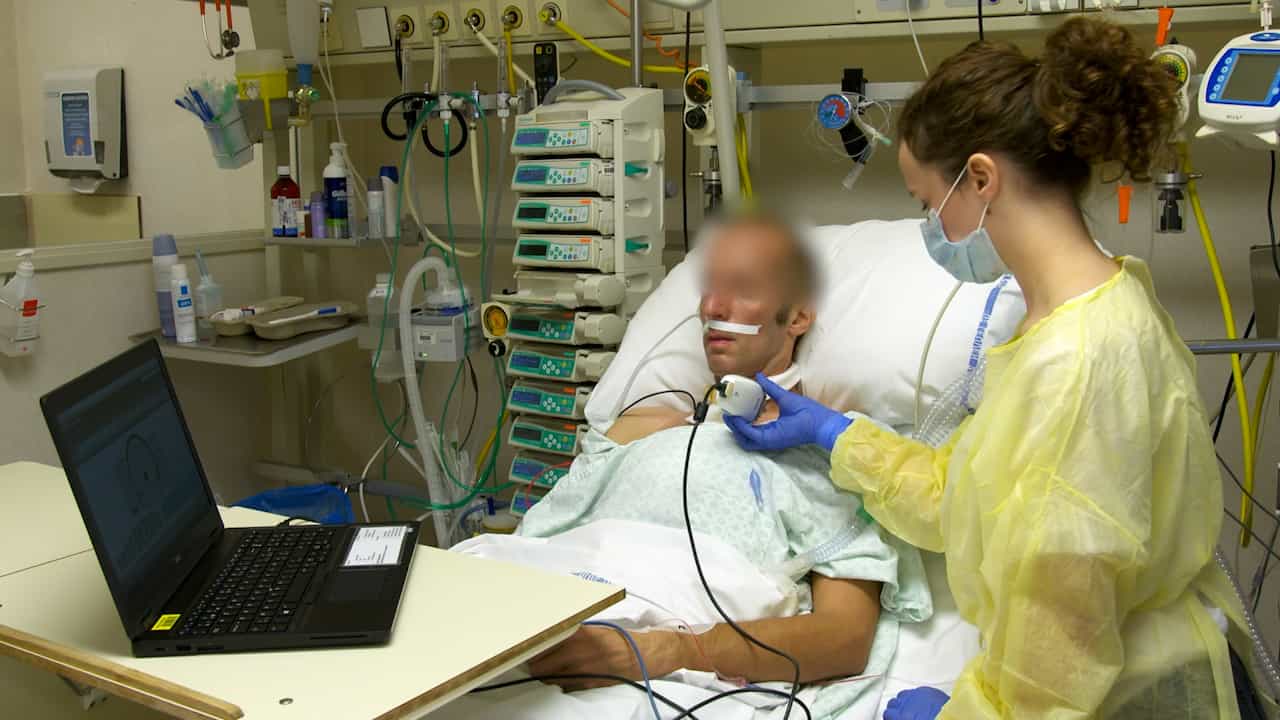
The obesity rate is increasing worldwide and the percentage of obese patients in the intensive care unit (ICU) is rising concomitantly. Ventilatory support strategies in obese patients must take into account the altered pathophysiological conditions. Unfortunately, prospective randomized multicenter trials on this subject are lacking. Therefore, current strategies are based on the individual experiences of ICU physicians and single-center studies. Noninvasive ventilation (NIV) in critically ill patients with acute respiratory failure and obesity hypoventilation syndrome (OHS) is an efficient treatment option and should be provided as early as possible is an effort to avoid intubation. Patient positioning is also crucial: half-sitting positions (>45°) improve lung compliance and functional residual capacity in patients with respiratory failure. Transpulmonary pressure measurements or the Acute Respiratory Distress Syndrome (ARDS) Network tables may help to adjust the optimal positive end-expiratory pressure (PEEP). The tidal volume should be adapted to the ideal and not the actual bodyweight (Vt = 6 ml/kg of ideal bodyweight) to avoid lung damage and (additional) right ventricular stress. Under particular conditions, inspiratory pressures >30 cmH2O may be tolerated for a limited duration. Early tracheostomy combined with termination/reduction of sedation and relaxation is controversy discussed in the literature as a therapeutic option during invasive ventilation of morbidly obese patients. However, data on early tracheotomy in obese respiratory failure patients are rare and this should be regarded as an individual treatment attempt only. In cases of refractory lung failure, venovenous extracorporeal membrane oxygenation (vv-ECMO) is an option despite anatomic changes in morbid obesity.
The obesity rate is increasing worldwide and the percentage of obese patients in the intensive care unit (ICU) is rising concomitantly. Ventilatory support strategies in obese patients must take into account the altered pathophysiological conditions. Unfortunately, prospective randomized multicenter trials on this subject are lacking. Therefore, current strategies are based on the individual experiences of ICU physicians and single-center studies. Noninvasive ventilation (NIV) in critically ill patients with acute respiratory failure and obesity hypoventilation syndrome (OHS) is an efficient treatment option and should be provided as early as possible is an effort to avoid intubation. Patient positioning is also crucial: half-sitting positions (>45°) improve lung compliance and functional residual capacity in patients with respiratory failure. Transpulmonary pressure measurements or the Acute Respiratory Distress Syndrome (ARDS) Network tables may help to adjust the optimal positive end-expiratory pressure (PEEP). The tidal volume should be adapted to the ideal and not the actual bodyweight (Vt = 6 ml/kg of ideal bodyweight) to avoid lung damage and (additional) right ventricular stress. Under particular conditions, inspiratory pressures >30 cmH2O may be tolerated for a limited duration. Early tracheostomy combined with termination/reduction of sedation and relaxation is controversy discussed in the literature as a therapeutic option during invasive ventilation of morbidly obese patients. However, data on early tracheotomy in obese respiratory failure patients are rare and this should be regarded as an individual treatment attempt only. In cases of refractory lung failure, venovenous extracorporeal membrane oxygenation (vv-ECMO) is an option despite anatomic changes in morbid obesity.
More Related Videos

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:30
Acute Respiratory Failure-III
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: