Related Experiment Video
Updated: Feb 23, 2026


Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Type 3 renal tubular acidosis associated with growth hormone deficiency

Insights
Children with renal tubular acidosis (RTA) and growth hormone deficiency may not respond to alkali therapy alone. Growth hormone therapy is crucial for their growth and RTA correction.
Area of Science:
- Pediatric Nephrology
- Endocrinology
- Growth Disorders
Background:
- Differentiating Type 3 Renal Tubular Acidosis (RTA) with growth hormone deficiency from classic Type 1 RTA is clinically important.
- Investigating growth patterns in children with RTA is essential for early diagnosis and intervention.
Observation:
- Two boys with Type 3 RTA and growth hormone deficiency were compared to 28 children with Type 1 RTA.
- Growth response to alkali therapy was assessed in children under 6 years old over a 13-year period.
Findings:
- Children with Type 1 RTA showed significant growth improvement on alkali therapy, reaching the 5th percentile.
- Boys with Type 3 RTA and growth hormone deficiency exhibited poor growth response to alkali alone.
- Growth hormone therapy normalized growth in boys with Type 3 RTA and led to long-term RTA correction.
Implications:
- Inadequate growth response to alkali therapy in children with RTA warrants growth hormone level assessment.
- Early identification and treatment of growth hormone deficiency in RTA patients are critical for optimal outcomes.
- This study highlights the importance of a multidisciplinary approach in managing complex pediatric renal and endocrine disorders.
Background:
We identified two boys with type 3 renal tubular acidosis (RTA) and growth hormone deficiency and we sought to differentiate them from children with classic type 1 distal RTA.
Methods:
We reviewed all children <6 years of age with RTA referred over a 13-year period and compared the growth response to alkali therapy in these two boys and in 28 children with only type 1 distal RTA.
Results:
All children with type 1 RTA reached the 5th percentile or higher on CDC growth charts within 2 years of alkali therapy. Their mean height standard deviation score (SDS) improved from -1.4 to -0.6 SDS and their mean mid-parental height (MPH) SDS improved from -0.6 to 0 SDS after 2 years. In contrast, the boys with growth hormone deficiency had a height SDS of -1.4 and -2.4 SDS after 2 years of alkali and the MPH SDS were both -2.6 SDS after 2 years of alkali therapy. Growth hormone therapy accelerated their growth to normal levels and led to long-term correction of RTA.
Conclusions:
A child with type 1 RTA whose height response after 2 years of alkali therapy is inadequate should undergo provocative growth hormone testing.


Related Concept Videos
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:29
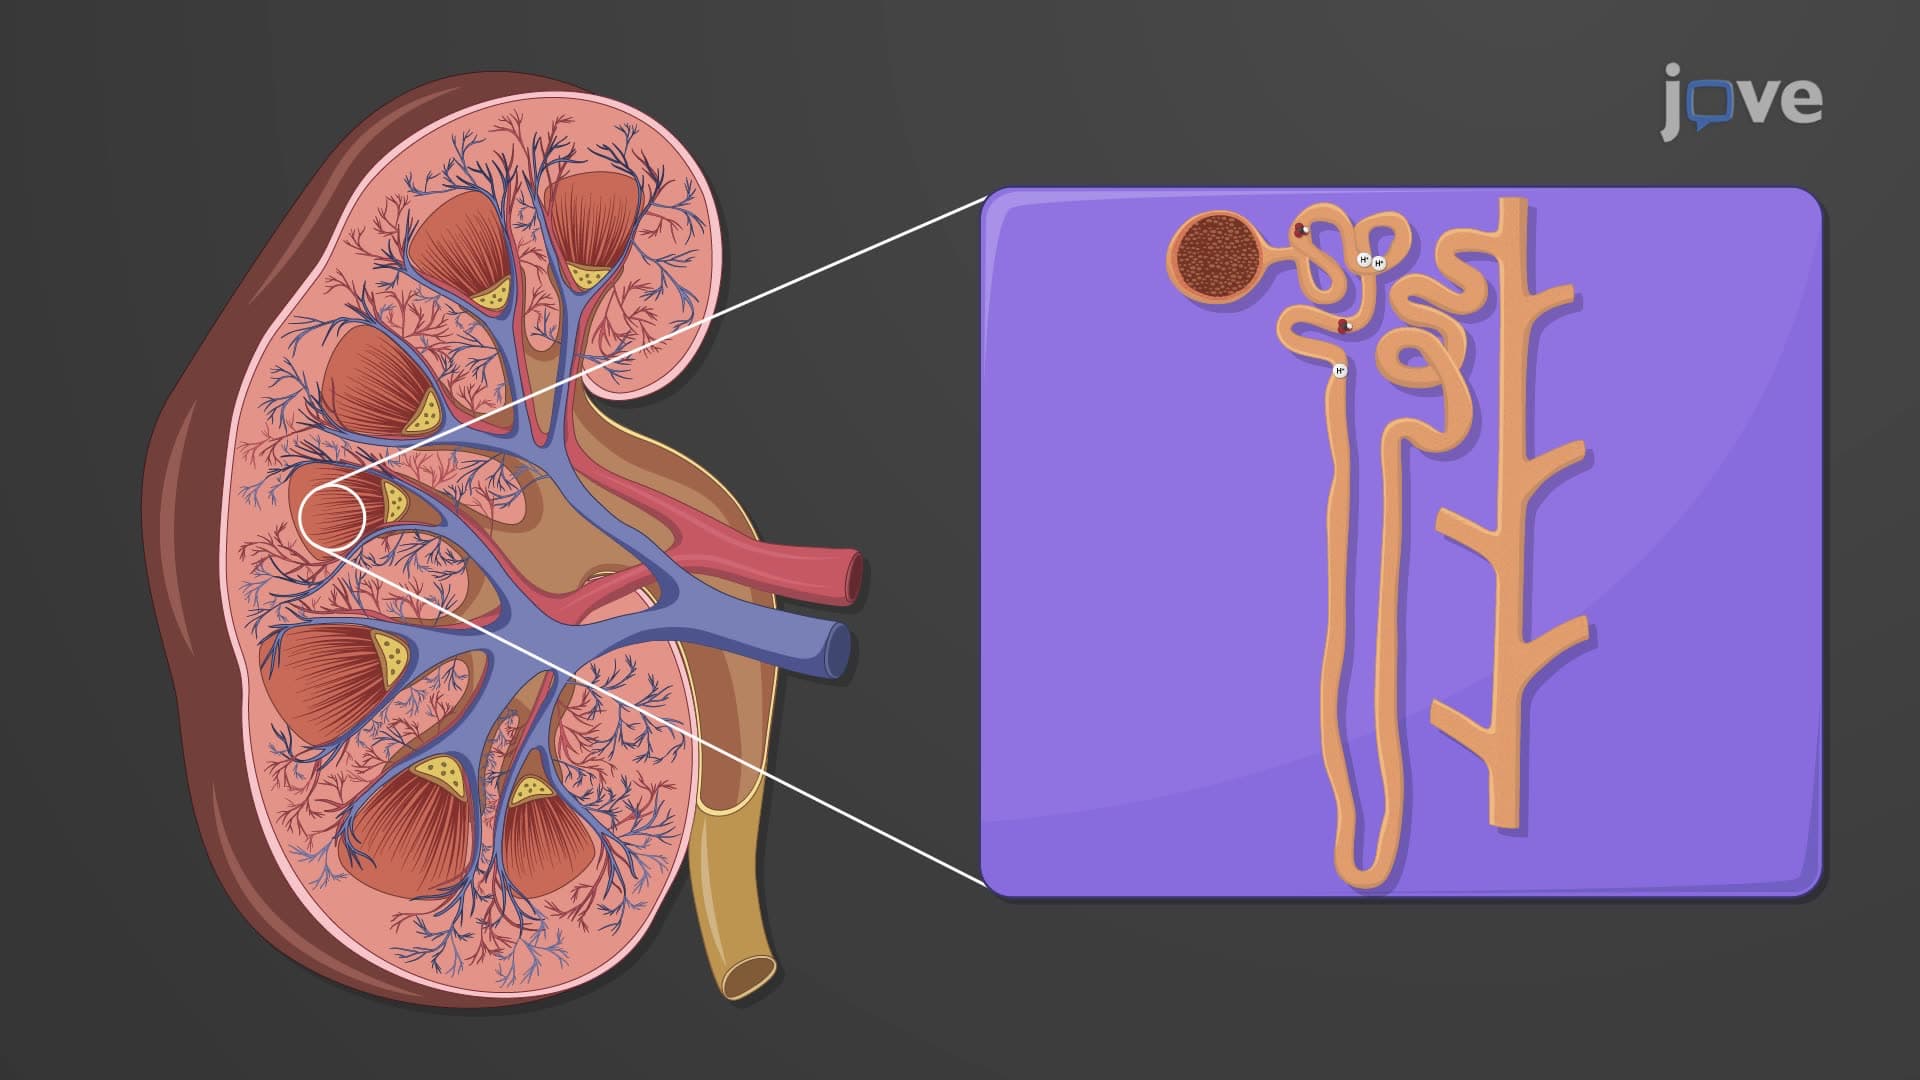
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:20
Inborn Errors of Metabolism
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes: