Related Experiment Video
Updated: Feb 23, 2026

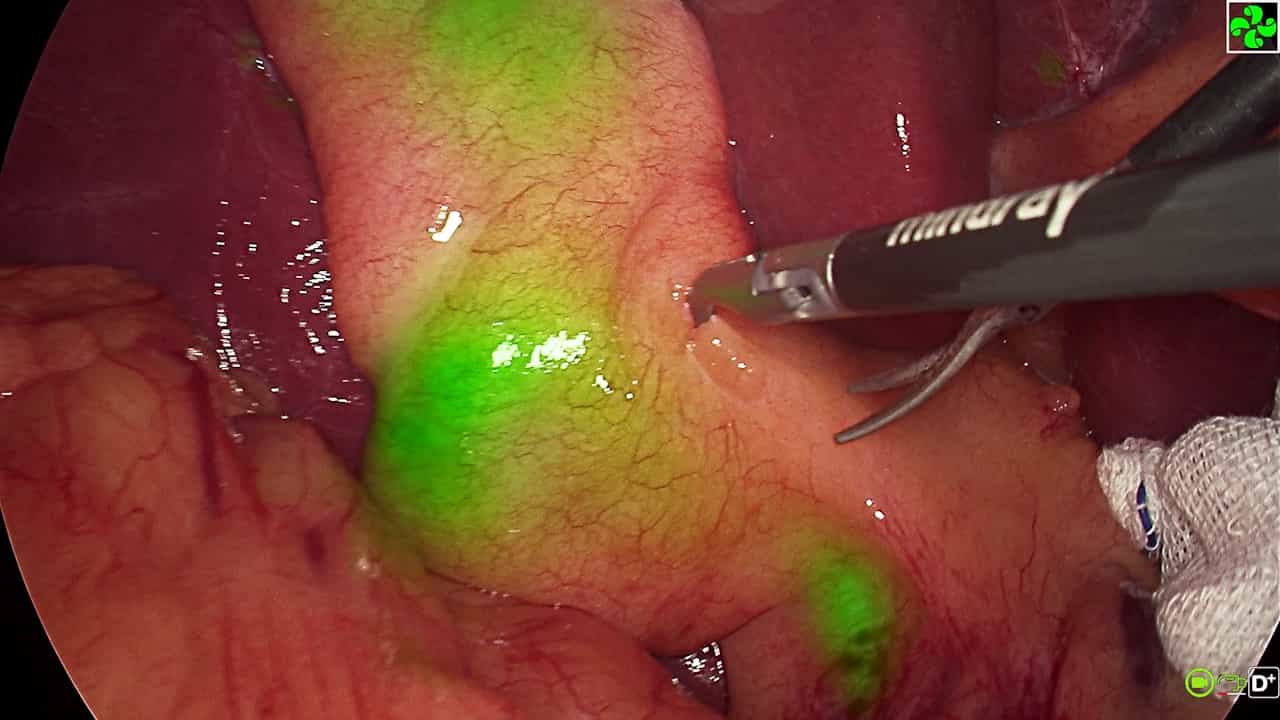
Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
External Drainage of Giant Infantile Choledochal Cyst before Definitive Repair: Is it Worth?
Vijai Datta Upadhyaya1, Basant Kumar1, Sandeep Kumar Raut2
1Assistant Professor, Department of Paediatric Surgery, Sanjay Gandhi Postgraduate Institute of Medical Science, Lucknow, Uttar Pradesh, India.

Insights
Infantile choledochal cysts (IFCC) can cause serious liver damage. External cyst drainage alongside antibiotics aids recovery from cholangitis and prevents further liver fibrosis progression.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Hepatology
Background:
- Infantile choledochal cysts (IFCC) present with jaundice, acholic stools, and abdominal distension.
- Delayed surgical intervention for IFCC can lead to irreversible liver fibrosis and cirrhosis.
Observation:
- Four cases of IFCC with cholangitis (infants aged 1-7 months) were managed over two years.
- All infants presented with cholangitis, elevated white blood cell counts (18-30.6x1000/UL), high total bilirubin (8.2-18 mg/dl), and prolonged prothrombin time (INR 1.33-1.9).
- Hepatic fibrosis was noted in all cases; cirrhosis in one.
Findings:
- One case received prolonged antibiotics; others had external cyst drainage plus IV antibiotics for cholangitis.
- External drainage facilitated early cholangitis recovery and improved liver function optimization.
- No mortality occurred, but one patient experienced postoperative complications and extended hospitalization.
Implications:
- External drainage of choledochal cysts can expedite recovery from cholangitis in infants.
- This approach helps mitigate biliary outflow obstruction, delaying progression to liver fibrosis.
- Early management is crucial to prevent severe liver damage in infants with IFCC.
Abstract:
Infantile Choledochal Cysts (IFCC) usually present with jaundice, acholic stool and abdominal lump or abdominal distension. If the surgical intervention is delayed, they rapidly progress to liver fibrosis which is considered to be irreversible if progressed to cirrhosis. We present the data of four cases (aged one month to seven months) of IFCC presented with cholangitis managed in one surgical unit in last two years. In one case, cholangitis was treated with prolonged antibiotic course before definitive repair whereas in rest, external drainage of cyst was done in addition to intravenous antibiotic to treat cholangitis. All the infants had features of cholangitis at time of presentation. Total leucocyte count ranged from 18x1000/UL to 30.6x1000/UL. Total bilirubin level at presentation ranged from 8.2 mg/dl to 18 mg/dl and Prothrombin time (INR) ranged from 1.33 to 1.9. Hepatic fibrosis was observed in all cases but cirrhosis was observed in only one case. There was no mortality but one patient had postoperative complication with prolonged hospital stay. External drainage helps in early recovery from cholangitis and better optimization of liver function. It also delays further progression to liver fibrosis by relieving the biliary outflow obstruction while waiting for definitive repair.