Related Experiment Video
Updated: Feb 23, 2026


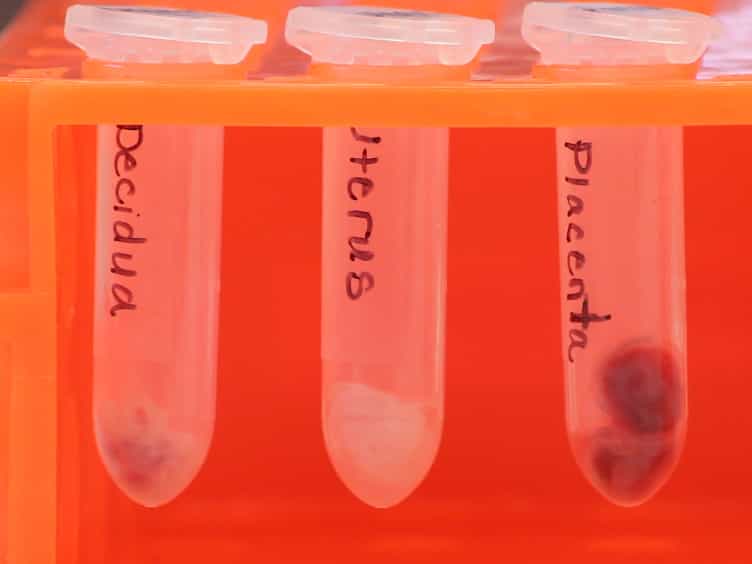
Isolation of Leukocytes from the Human Maternal-fetal Interface
Published on: May 21, 2015
Maternal leukocytosis after antenatal corticosteroid administration: a systematic review and meta-analysis
Melissa E Bauer1, Laura K Price2, Mark P MacEachern3
1a Department of Anesthesiology , University of Michigan , Ann Arbor , MI , USA.

Although it is known that corticosteroid administration causes leukocytosis, the magnitude and length of time this leukocytosis persists is unknown during pregnancy. This study aimed to establish the expected range of maternal leukocytosis in healthy pregnant women at risk for preterm delivery after antenatal corticosteroid administration. PubMed, Embase and ClinicalTrials.gov were searched to identify the studies in healthy women at risk for preterm delivery without signs of clinical infection that reported white blood cell values preceding and after antenatal corticosteroid administration. The inverse variance weighting technique was used to calculate the weighted means and the standard deviation from the mean for each time period. Six studies met inclusion criteria and included 524 patients and 1406 observations. Mean ± standard deviation maternal white blood cell count values prior to antenatal corticosteroid administration and up to 24, 48, 72 and 96 hours after corticosteroid administration were 10.4 ± 2.4, 13.6 ± 3.6, 12.1 ± 3.0, 11.5 ± 2.9 and 11.1 ± 2.5 × 10⁹/L, respectively. Leukocytosis in healthy, non-infected women is expected to peak 24 hours after antenatal corticosteroid administration and the magnitude of increase is small. Impact statement What is already known on this subject: While it is well known that administration of antenatal corticosteroids causes leukocytosis, it is currently unknown the magnitude and length of time the leukocytosis persists. What the results of this study add: This study establishes the expected range and the temporal progression and regression with antenatal corticosteroid administration in healthy pregnant women at risk for preterm delivery without clinical signs of infection. What the implications are of these findings for clinical practice and/or further research: Clinicians may wish to consider further investigation into the clinical cause, whether infectious or non-infectious, for absolute values and changes outside this range.
Although it is known that corticosteroid administration causes leukocytosis, the magnitude and length of time this leukocytosis persists is unknown during pregnancy. This study aimed to establish the expected range of maternal leukocytosis in healthy pregnant women at risk for preterm delivery after antenatal corticosteroid administration. PubMed, Embase and ClinicalTrials.gov were searched to identify the studies in healthy women at risk for preterm delivery without signs of clinical infection that reported white blood cell values preceding and after antenatal corticosteroid administration. The inverse variance weighting technique was used to calculate the weighted means and the standard deviation from the mean for each time period. Six studies met inclusion criteria and included 524 patients and 1406 observations. Mean ± standard deviation maternal white blood cell count values prior to antenatal corticosteroid administration and up to 24, 48, 72 and 96 hours after corticosteroid administration were 10.4 ± 2.4, 13.6 ± 3.6, 12.1 ± 3.0, 11.5 ± 2.9 and 11.1 ± 2.5 × 10⁹/L, respectively. Leukocytosis in healthy, non-infected women is expected to peak 24 hours after antenatal corticosteroid administration and the magnitude of increase is small. Impact statement What is already known on this subject: While it is well known that administration of antenatal corticosteroids causes leukocytosis, it is currently unknown the magnitude and length of time the leukocytosis persists. What the results of this study add: This study establishes the expected range and the temporal progression and regression with antenatal corticosteroid administration in healthy pregnant women at risk for preterm delivery without clinical signs of infection. What the implications are of these findings for clinical practice and/or further research: Clinicians may wish to consider further investigation into the clinical cause, whether infectious or non-infectious, for absolute values and changes outside this range.
More Related Videos

Related Concept Videos
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by...
 01:27
Disorders of Leukocytes
Leukopenia may result from bone marrow disorders, autoimmune diseases, and infectious diseases. For example, conditions such as multiple myeloma and aplastic anemia can impair the bone marrow's ability to produce adequate leukocytes. Similarly, autoimmune diseases like lupus and viral infections such as HIV can prompt the immune...
 01:07
Teratogenicity