Related Experiment Video
Updated: Jul 29, 2026
Extrahepatic Bile Duct and Gall Bladder Dissection in Nine-Day-Old Mouse Neonates
Published on: August 23, 2022
Intestinal obstruction due to kaposiform hemangioendothelioma in a 1-month-old infant: A case report
Joong Kee Youn1, Shin-Hoo Park, Ji-Won Han
1Department of Pediatric Surgery, Seoul National University College of Medicine, Seoul, Korea.

Insights
Kaposiform hemangioendothelioma (KHE) in the intestine is rare but can cause obstruction. Complete surgical resection offers a successful treatment for this aggressive vascular tumor in infants.
Area of Science:
- Pediatric Oncology
- Vascular Malformations
- Surgical Gastroenterology
Background:
- Kaposiform hemangioendothelioma (KHE) is an aggressive vascular tumor typically affecting infants and children.
- While cutaneous and visceral forms are more common, intestinal KHE is a rarer presentation.
- Intestinal KHE has a better prognosis if localized and without coagulopathy, but data remains limited.
Observation:
- A 1-month-old female infant presented with abdominal distention and bilious vomiting.
- Diagnostic workup suggested intestinal obstruction.
- Surgical exploration revealed a jejunal mass causing obstruction.
Findings:
- The infant underwent successful small bowel segmental resection and anastomosis.
- Pathological examination confirmed the mass as intestinal type Kaposiform Hemangioendothelioma.
- The patient was discharged symptom-free post-surgery.
Implications:
- Intestinal KHE can manifest as a critical cause of bowel obstruction in infants.
- Complete surgical resection is a viable and effective management strategy.
- Further case reporting and research are crucial for understanding treatment options and prognosis for intestinal KHE.
Rationale:
Kaposiform hemangioendothelioma (KHE) is an aggressive vascular tumor, mainly occurring in infants and young children and previously reported cases were mainly cutaneous or visceral form. Intestinal kaposiform hemangioma was first reported in 2012. Intestinal type KHE showed better prognosis if the lesion was limited in the gastrointestinal tract and coagulopathy was not accompanied. Since the number of reported cases is small, further study for treatment options and prognosis need to be done.
Patient Concerns:
We described the case of a 1-month-old female who had abdominal distention and bilious vomiting.
Diagnoses:
She was suspected as intestinal obstruction after diagnostic work up.
Interventions:
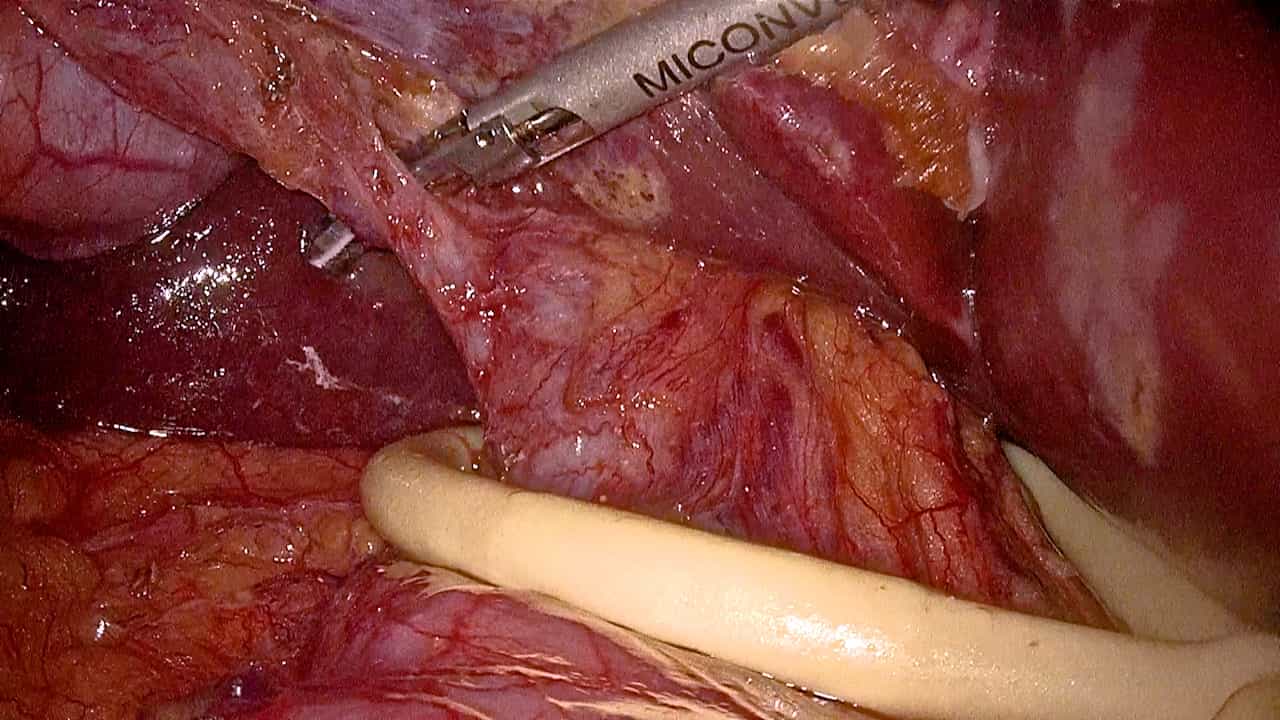
Surgical exploration was performed and jejunal obstruction with a mass was identified. Small bowel segmental resection and anastomosis was performed.
Outcomes:
The patient discharged with symptom free. Through the pathological examination, the mass was identified as intestinal type KHE.
Lessons:
Intestinal KHE can cause bowel obstruction and be managed successfully with complete surgical resection. More cases should be reported and further evaluation for treatment options and prognosis evaluation is necessary.
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:11
Pyloric Obstruction
 01:29
Intestinal Obstruction I: Introduction
 01:07
Intestinal Obstruction II: Pathophysiology