Related Experiment Video
Updated: Feb 22, 2026
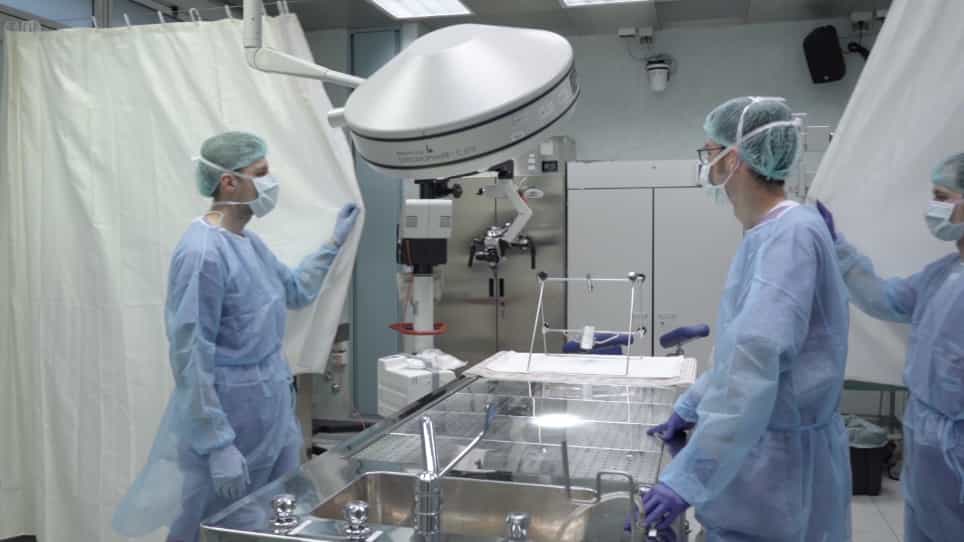
Learning Modern Laryngeal Surgery in a Dissection Laboratory
Published on: March 18, 2020
Management of Type I and Type II laryngeal clefts: controversies and evidence
Sarah N Bowe1, Christopher J Hartnick
1Department of Otolaryngology-Head and Neck Surgery, Massachusetts Eye & Ear Infirmary, Boston, Massachusetts, USA.

Purpose Of Review:
To summarize the pediatric Type I and Type II laryngeal cleft literature, paying special attention to recent trends, including evolution of surgical techniques, standardization of outcome assessments, and utilization of management algorithms.
Recent Findings:
There are a variety of options to choose from whenever considering Type I and Type II cleft repair, including endoscopic repair, transoral robotic surgery, and injection laryngoplasty. Conservative management including feeding therapy and treatment of comorbid medical conditions is recommended prior to repair. Validated outcome measures have arisen for swallow study interpretation and timing, as well as caregiver quality-of-life assessment. In addition, a series of medical algorithms have been proposed, which provide specific recommendations for diagnosis, treatment, and follow-up.
Summary:
For clefts that fail conservative management, endoscopic repair has become the gold standard. In addition, injection laryngoplasty appears to provide both a diagnostic and therapeutic option in the management of these patients. Transoral robotic-assisted endoscopic repair appears well tolerated and feasible, although broader implementation of this technology remains limited. The development and refinement of best practice algorithms can help standardize management and improve decision-making. Furthermore, incorporating validated outcome measures, recorded and followed over time, will improve both patient care and research efforts moving forward.

Related Concept Videos
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids,...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...