A Simplified Method of Accurate Postprocessing of Diffusion Tensor Imaging for Use in Brain Tumor Resection
Related Experiment Video
Updated: Feb 22, 2026
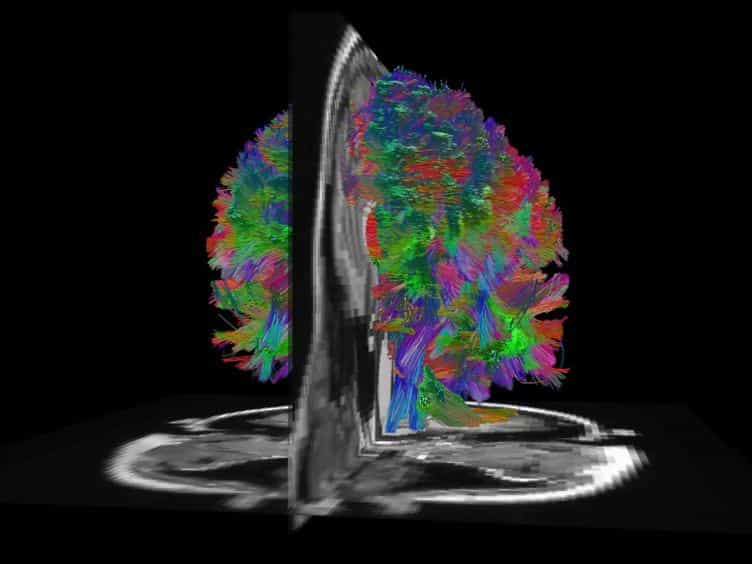
DTI of the Visual Pathway - White Matter Tracts and Cerebral Lesions
Published on: August 26, 2014
Phillip A Bonney1, Andrew K Conner1, Lillian B Boettcher1
1Department of Neurosurgery, University of Oklahoma Health Sciences Center, Oklahoma City, Oklahoma.

Background:
Use of diffusion tensor imaging (DTI) in brain tumor resection has been limited in part by a perceived difficulty in implementing the techniques into neurosurgical practice.
Objective:
To demonstrate a simple DTI postprocessing method performed without a neuroscientist and to share results in preserving patient function while aggressively resecting tumors.
Methods:
DTI data are obtained in all patients with tumors located within presumed eloquent cortices. Relevant white matter tracts are mapped and integrated with neuronavigation by a nonexpert in < 20 minutes. We report operative results in 43 consecutive awake craniotomy patients from January 2014 to December 2014 undergoing resection of intracranial lesions. We compare DTI-expected findings with stimulation mapping results for the corticospinal tract, superior longitudinal fasciculus, and inferior fronto-occipital fasciculus.
Results:
Twenty-eight patients (65%) underwent surgery for high-grade gliomas and 11 patients (26%) for low-grade gliomas. Seventeen patients had posterior temporal lesions; 10 had posterior frontal lesions; 8 had parietal-temporal-occipital junction lesions; and 8 had insular lesions. With DTI-defined tracts used as a guide, a combined 65 positive maps and 60 negative maps were found via stimulation mapping. Overall sensitivity and specificity of DTI were 98% and 95%, respectively. Permanent speech worsening occurred in 1 patient (2%), and permanent weakness occurred in 3 patients (7%). Greater than 90% resection was achieved in 32 cases (74%).
Conclusion:
Accurate DTI is easily obtained, postprocessed, and implemented into neuronavigation within routine neurosurgical workflow. This information aids in resecting tumors while preserving eloquent cortices and subcortical networks.