Related Experiment Video
Updated: Feb 22, 2026
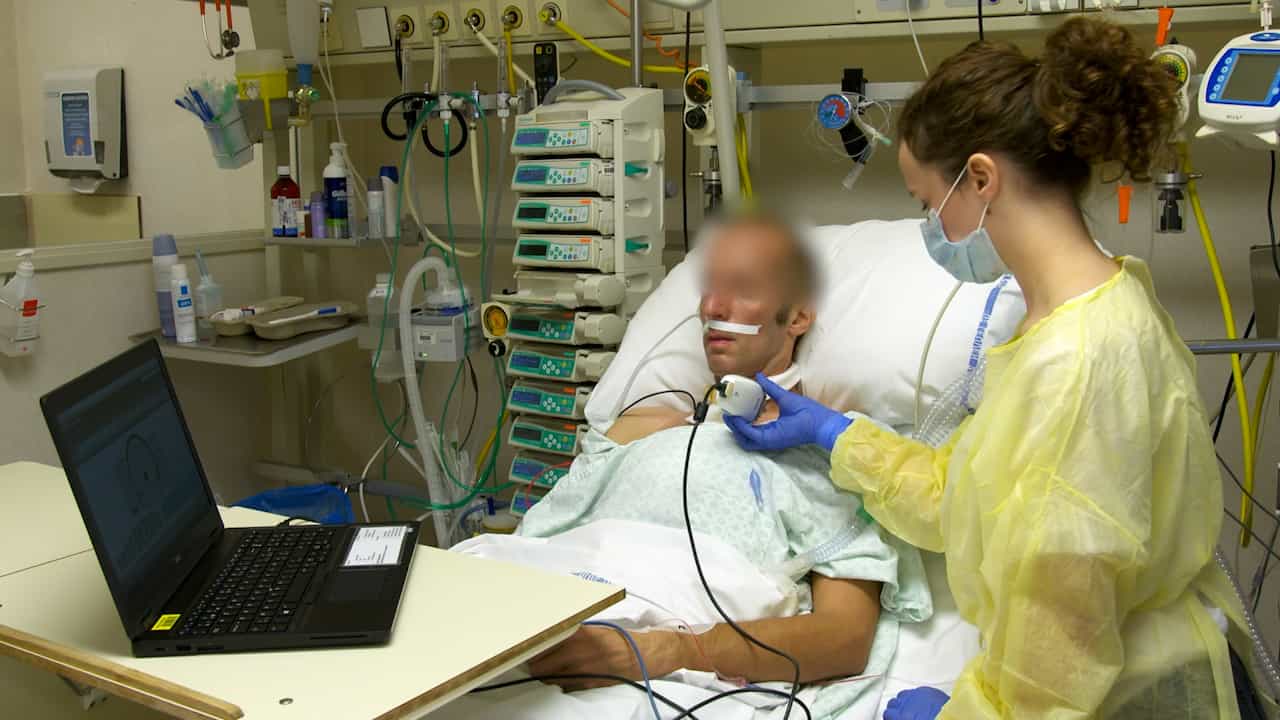
Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Manometry Optimized Positive Expiratory Pressure (MOPEP) in Excessive Dynamic Airway Collapse (EDAC)
Muhammad A Zafar1, Aaron M Mulhall1, William Eschenbacher1
1Division of Pulmonary, Critical Care and Sleep Medicine, Department of Internal Medicine, University of Cincinnati Medical Center, United States; Pulmonary Section, Department of Medicine, Cincinnati Veteran Affairs Medical Center, United States.

Background:
Positive expiratory pressure(PEP) breathing modalities are commonly prescribed in obstructive lung diseases, however practical methods of airway pressures(AP) quantification for therapeutic efficacy are lacking. Excessive dynamic airway collapse(EDAC) is characterized by expiratory central airway collapse leading to dyspnea and poor quality of life(QoL), with limited therapeutic options.
Purpose:
To measure AP and exertional dyspnea in EDAC patients during normal breathing and with use of pursed-lip breathing(PLB), nasal PEP device(nPEP), and oral-PEP valve(oPEP) during rest and exercise using an Esophageal Manometer.
Methods:
EDAC patients exercised on a bicycle ergometer sequentially using normal breathing, PLB, nPEP, and oPEP for five-minute intervals. AP's were measured by continuous topographic upper airway manometry. Pre- and post-exercise BORG dyspnea scores were recorded and QoL measured with the St. George's respiratory questionnaire(SGRQ-C). The most effective and patient-preferred PEP modality was prescribed for daily activities and SGRQ-C repeated after one week.
Results:
Three women with symptomatic EDAC participated. Expiratory laryngopharyngeal AP's during exercise with normal breathing, PLB, nPEP and oPEP in patient-1 were 1.7, 14, 4.5, and 7.3 mmHg, in patient-2; 2.3, 8, 8.3, and 12 mmHg, and in patient-3; 1, 15, unobtainable, and 9 mmHg, respectively. Maximal reduction in BORG scores occurred with PLB in patient 1 and with oPEP in patients 2 and 3. After 1 week mean SGRQ-C scores declined by 17-points.
Conclusions:
Upper airway manometry directly measures laryngopharyngeal pressures during rest and exercise and can be used to select and optimize PEP breathing techniques to improve respiratory symptoms in EDAC patients.

Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...