Related Experiment Video
Updated: Feb 22, 2026

External Cephalic Version: Is it an Effective and Safe Procedure?
Published on: June 6, 2020
Risk of maternal, fetal and neonatal complications associated with the use of the transcervical balloon catheter in
Jip S M Gommers1, Milou Diederen1, Chris Wilkinson2
1Faculty of Health, Medicine and Life Sciences, Maastricht University, Universiteitssingel 60, 6229 ER, Maastricht, The Netherlands.

Induction of labour is one of the most frequently applied obstetrical interventions globally. Many studies have compared the use of balloon catheters with pharmacological agents. Although the safety of the balloon catheter is often mentioned, little has been written about the total spectrum of maternal and fetal morbidity associated with induction of labour using a balloon catheter. We evaluated the safety of labour induction with a transcervical balloon catheter by conducting a literature review with pooled risk assessments of the maternal, fetal and neonatal morbidity. We searched Medline, EMBASE and CINAHL as well as the Cochrane database using the Keywords 'induction of labour', 'cervical ripening', 'transcervical balloon', 'balloon catheter' and 'Foley balloon'. We did not use language or date restrictions. Randomized and quasi-randomized controlled trials as well as observational studies that contained original data on occurrence of maternal, fetal or neonatal morbidity during induction of labour with the balloon catheter were included. Studies were excluded if the balloon catheter was used concurrently with oxytocin and concurrently or consecutively with misoprostol, dinoprostone or extra-amniotic saline infusion. Study selection and quality assessment was performed by two authors independently using a standardized critical appraisal instrument. Outcomes were reported as weighted mean rates. We detected 84 articles reporting on 13,791 women. The overall risk of developing intrapartum maternal infection was 11.3% (912 of 8079 women), 3.3% (151 of 4538 women) for postpartum maternal infection and 4.6% (203 of 4460 women) for neonatal infection. Uterine hypercontractility occurred in 2.7% (148 of 5439) of the women. Uterine rupture after previous caesarean section occurred in 1.9% of women (26 of 1373), while other major maternal complications had an occurrence rate of <1%. The risk for developing minor maternal complications was <2%. The risk of developing a non-reassuring fetal heart rate was 10.8% (793 of 7336 women), 10.1% (507 of 5008 women) for fetal distress and 14.0% (460 of 3295 women) for meconium stained liquor. Neonatal death occurred in 0.29% (6 of 2058) of the deliveries and NICU admission in 7.2% (650 of 9065 deliveries). This review shows that labour induction with a balloon catheter is a safe intervention, with intrapartum maternal infection being the only reasonable risk above 10%.
Induction of labour is one of the most frequently applied obstetrical interventions globally. Many studies have compared the use of balloon catheters with pharmacological agents. Although the safety of the balloon catheter is often mentioned, little has been written about the total spectrum of maternal and fetal morbidity associated with induction of labour using a balloon catheter. We evaluated the safety of labour induction with a transcervical balloon catheter by conducting a literature review with pooled risk assessments of the maternal, fetal and neonatal morbidity. We searched Medline, EMBASE and CINAHL as well as the Cochrane database using the Keywords 'induction of labour', 'cervical ripening', 'transcervical balloon', 'balloon catheter' and 'Foley balloon'. We did not use language or date restrictions. Randomized and quasi-randomized controlled trials as well as observational studies that contained original data on occurrence of maternal, fetal or neonatal morbidity during induction of labour with the balloon catheter were included. Studies were excluded if the balloon catheter was used concurrently with oxytocin and concurrently or consecutively with misoprostol, dinoprostone or extra-amniotic saline infusion. Study selection and quality assessment was performed by two authors independently using a standardized critical appraisal instrument. Outcomes were reported as weighted mean rates. We detected 84 articles reporting on 13,791 women. The overall risk of developing intrapartum maternal infection was 11.3% (912 of 8079 women), 3.3% (151 of 4538 women) for postpartum maternal infection and 4.6% (203 of 4460 women) for neonatal infection. Uterine hypercontractility occurred in 2.7% (148 of 5439) of the women. Uterine rupture after previous caesarean section occurred in 1.9% of women (26 of 1373), while other major maternal complications had an occurrence rate of <1%. The risk for developing minor maternal complications was <2%. The risk of developing a non-reassuring fetal heart rate was 10.8% (793 of 7336 women), 10.1% (507 of 5008 women) for fetal distress and 14.0% (460 of 3295 women) for meconium stained liquor. Neonatal death occurred in 0.29% (6 of 2058) of the deliveries and NICU admission in 7.2% (650 of 9065 deliveries). This review shows that labour induction with a balloon catheter is a safe intervention, with intrapartum maternal infection being the only reasonable risk above 10%.
More Related Videos
 03:14
Author Spotlight: Enhancing Success of Ultrasound-Guided Neuraxial Anesthesia in Cases with Difficult Anatomy
Published on: January 31, 2025
 05:21
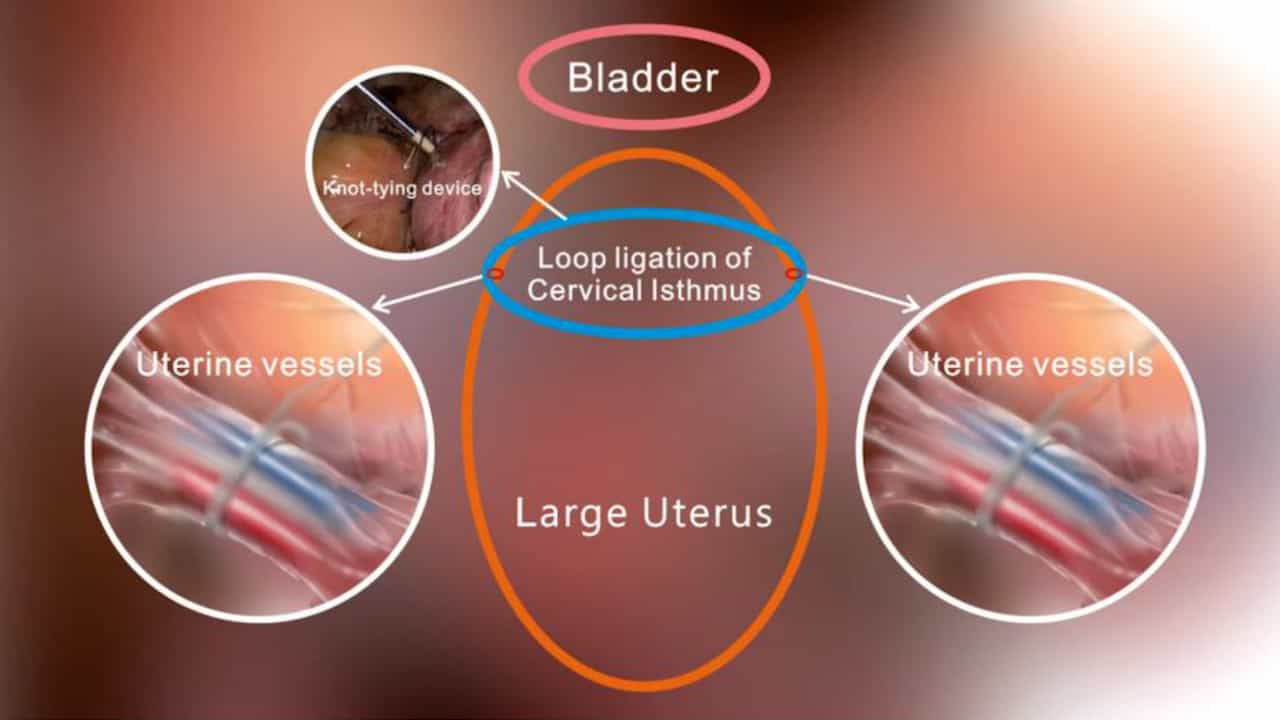
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Related Concept Videos
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:26
Cardiac Catheterization IV: Nursing Management
 01:28
Cardiac Catheterization I: Pre-Procedure Overview