Related Experiment Video
Updated: Feb 22, 2026
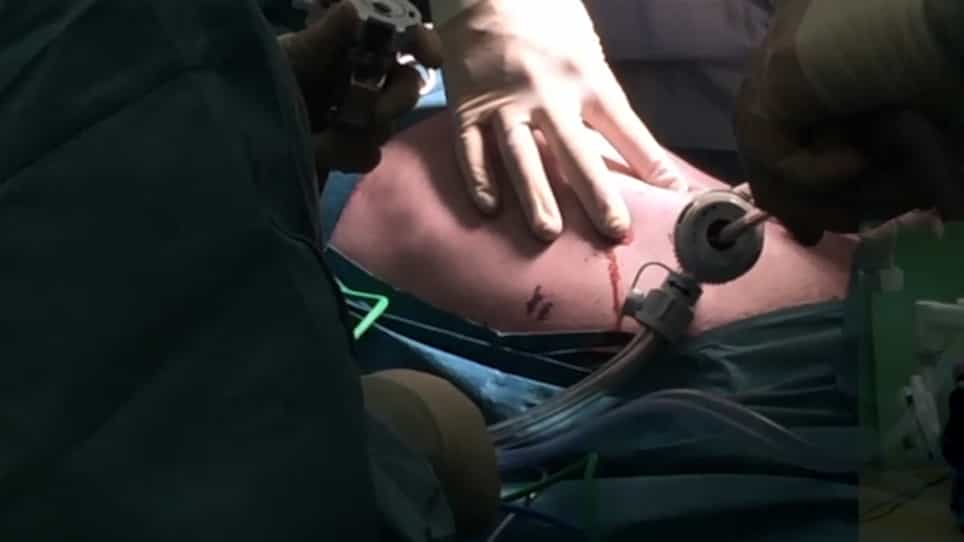

Robotic Lateral Pancreaticojejunostomy for Chronic Pancreatitis
Published on: December 14, 2019
Prophylactic ulinastatin administration for preventing post-endoscopic retrograde cholangiopancreatography
Kun Zhu1, Jian-Ping Wang1, Jin-Gen Su1
1Department of Surgery, Shanghai Jiading Central Hospital, Shanghai 201800, P.R. China.

Abstract:
The objective of the present study was to perform a meta-analysis of all available studies on the effect of prophylactic ulinastatin administration on preventing post-endoscopic retrograde cholangiopancreatography (ERCP) pancreatitis (PEP). The PubMed, Web of Knowledge and Chinese National Knowledge Infrastructure databases were searched to identify all relevant studies published in English or Chinese prior to April 2016. Cochrane Review Manager was used to calculate the pooled risk ratio (RR) and 95% confidence interval (CI) to determine the effect of prophylactic ulinastatin on PEP, post-ERCP hyperamylasemia (PEHA) and post-ERCP abdominal pain. The analysis revealed that prophylactic ulinastatin administration significantly reduced the PEP risk (RR=0.49; 95% CI: 0.33-0.74; P=0.0006; I2=24); however, such significant risk reduction occurred only in patients with low or average risk for PEP and high-dosage ulinastatin (150,000 or 200,000 U) administration, and when the ulinastatin administration began prior to or during ERCP. Pre-ERCP ulinastatin administration alone without additional administration after ERCP was sufficient. Prophylactic ulinastatin also significantly reduced the PEHA risk (RR=0.68; 95% CI: 0.56-0.83; P=0.0001; I2=19) and marginally reduced the incidence of post-ERCP abdominal pain (RR=0.67; 95% CI: 0.45-1.00; P=0.05; I2=67). In conclusion, prophylactic ulinastatin administration significantly reduced the risk of PEP in patients with low or average risk for PEP when administered at a high dosage prior to or during ERCP. High-quality studies, particularly on high-risk patients, are warranted.
Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...