Related Experiment Video
Updated: Feb 21, 2026
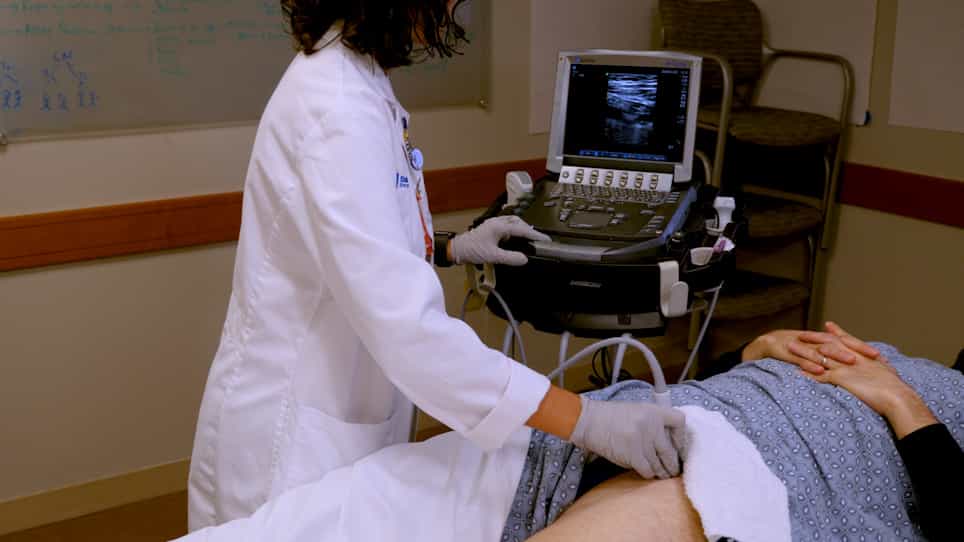
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Pediatric Hospital Acquired Venous Thromboembolism
Char M Witmer1, Clifford M Takemoto2
1Department of Pediatrics, Division of Hematology, Children's Hospital of Philadelphia, Philadelphia, PA, United States.

Insights
Pediatric hospital-acquired venous thromboembolism (HA-VTE) is rising, with central venous catheters as a key risk. Research is needed on effective risk assessment and prevention strategies to reduce morbidity and mortality in children.
Area of Science:
- Pediatric Thrombosis
- Hospital-Acquired Conditions
- Vascular Medicine
Background:
- Pediatric hospital-acquired venous thromboembolism (HA-VTE) incidence is increasing significantly.
- HA-VTE is linked to substantial morbidity and mortality in children.
- Central venous catheters are the primary identified risk factor, alongside acquired and inherited factors.
Purpose of the Study:
- To address the need for effective risk assessment tools for pediatric HA-VTE.
- To evaluate current and potential preventative strategies for HA-VTE in hospitalized children.
- To highlight the ongoing challenges and future directions in managing pediatric thrombosis.
Main Methods:
- Review of existing literature on pediatric HA-VTE risk factors and prevention.
- Discussion of limitations in current risk-assessment models, emphasizing the need for prospective validation.
- Exploration of mechanical and pharmacologic thromboprophylactic options and their associated harms.
Main Results:
- Current risk-assessment models for pediatric HA-VTE are limited by small sample sizes and require validation.
- Standard anticoagulants (heparin, warfarin) require monitoring and pose bleeding risks.
- Direct oral anticoagulants show promise for revolutionizing pediatric thrombosis management.
Conclusions:
- Further research is critical to assess the clinical outcomes, effectiveness, and harms of VTE prevention strategies in children.
- High clinical suspicion is essential for prompt diagnosis and treatment of HA-VTE to mitigate adverse effects.
- Optimizing HA-VTE prevention requires a multi-faceted approach, including improved risk assessment and novel therapeutic agents.
Abstract:
Pediatric hospital acquired venous thromboembolism (HA-VTE) is an increasing problem with an estimated increase from 5.3 events per 10,000 pediatric hospital admissions in the early 1990s to a current estimate of 30-58 events per 10,000 pediatric hospital admissions. Pediatric HA-VTE is associated with significant morbidity and mortality. The etiology is multifactorial but central venous catheters remain the predominant risk factor. Additional HA-VTE risk factors include both acquired (recent surgery, immobility, inflammation, and critical illness) and inherited risk factors. Questions remain regarding the most effective method to assess for HA-VTE risk in hospitalized pediatric patients and what preventative strategies should be implemented. While several risk-assessment models have been published in pediatric patients, these studies have limited power due to small sample size and require prospective validation. Potential thromboprophylactic measures include mechanical and pharmacologic methods both of which have associated harms, the most significant of which is bleeding from anticoagulation. Standard anticoagulation options in pediatric patients currently include unfractionated heparin, low molecular weight heparin, or warfarin all of which pose a monitoring burden. Ongoing pediatric studies with direct oral anticoagulants could potentially revolutionize the prevention and treatment of pediatric thrombosis with the possibility of a convenient route of administration and no requirement for monitoring. Further studies assessing clinical outcomes of venous thromboembolism (VTE) prevention strategies are critical to evaluate the effectiveness and harm of prophylactic interventions in children. Despite HA-VTE prevention efforts, thrombotic events can still occur, and it is important that clinicians have a high clinical suspicion to ensure prompt diagnosis and treatment to prevent further associated harms.


Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:27
Pulmonary Embolism III: Nursing Management