Related Experiment Video
Updated: Feb 21, 2026
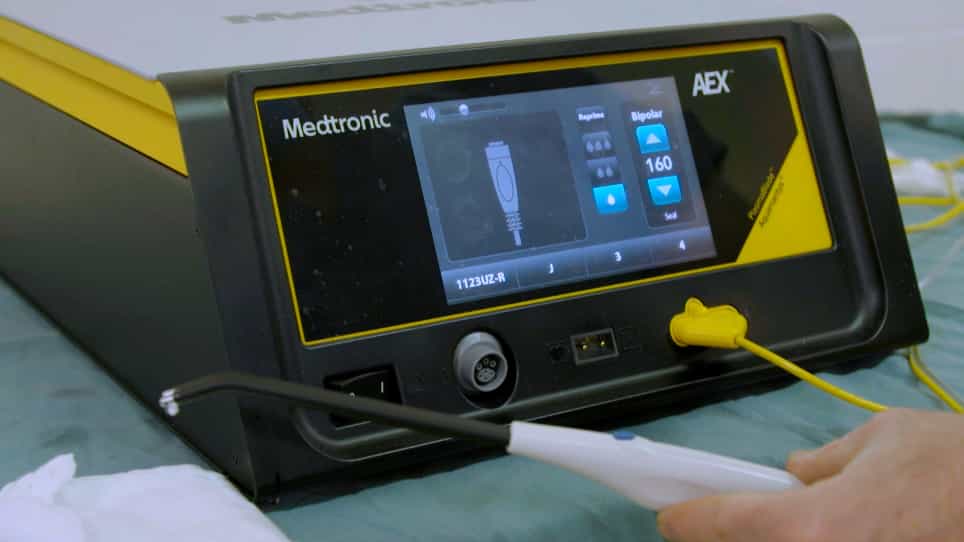

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Bleeding peptic ulcer: An evolving role for surgical intervention
Frank J Branicki1, Albert Cw Ting1, Philip Gertsch1
1Department of Surgery, University of Hong Kong Medical Centre, Queen Mary Hospital, Hong Kong.

Abstract:
Early surgical intervention was previously advocated in patients > 60 years with bleeding peptic ulcer presenting with haemodynamic instability or ongoing transfusion requirements. It is, however, well recognized that emergency surgical intervention with its inherent risks must be reserved for highly selected patients in whom endoscopy initially fails to control exsanquinating haemorrhage or in whom life-threatening bleeding recurs. Therapeutic endoscopy for bleeding ulcer has led to a remarkable decline in rebleeding rates, the need for emergency surgery and mortality. Octogenarians are at risk, particularly when ulcer size exceeds 2 cm. Poor surgical candidates make up two-thirds of patients with major ulcer bleeding and operation is to be avoided if at all possible. Medical therapy with proton pump inhibitor and subsequent eradication of Helicobacter pylori following endoscopic treatment has been shown to be beneficial to outcomes. Should surgery be deemed necessary, it is likely that laparoscopic techniques to control bleeding, with or without the addition of an acid-reducing procedure, will find a role in haemodynamically stable patients undergoing operation on an early elective basis.

Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors