Related Experiment Video
Updated: Feb 21, 2026
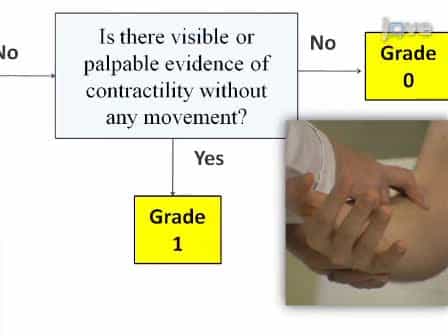
Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Benchmarking rehabilitation practice in the intensive care unit
Anna Knott1, Matt Stevenson1, Stephanie Km Harlow1
1Physiotherapy Department, Ashford and St Peter's Hospitals NHS Foundation Trust, Chertsey, Surrey, UK.

Introduction:
Early rehabilitation in critically ill patients has been demonstrated to be safe and is associated with many positive outcomes. Despite this, there are inconsistencies in the early active rehabilitation that patients receive on intensive care units. The aims of this study were to quantify the amount of active rehabilitation provided for patients in a District General Hospital intensive care unit and to identify specific barriers encountered.
Methods:
Data were collected over a six-week period during March and April 2013. All patients admitted to the intensive care unit at St Peter's Hospital for more than 48 h were included. For every treatment session, the treating physiotherapist recorded what type of treatment took place. Treatments were classified as either non-active or active rehabilitation. Non-active rehabilitation included chest physiotherapy, passive range of movement exercises and hoisting to a chair. Active rehabilitation was defined as any treatment including active/active-assisted exercises, sitting on the edge of the bed, sitting to standing, standing transfers, marching on the spot or ambulation. Classification of rehabilitation was based upon internationally agreed intensive care unit activity codes and definitions. All barriers to active rehabilitation were also recorded.
Results:
The study included 35 patients with a total of 194 physiotherapy treatment sessions. Active rehabilitation was included in 51% of all treatment sessions. The median time to commencing active rehabilitation from intensive care unit admission was 3 days (range 3-42 [IQR 3-7]). The most frequent barriers to active rehabilitation were sedation and endotracheal tubes, which together accounted for 50% of the total barriers.
Conclusion:
The study provides useful benchmarking of current rehabilitation activity in a District General Hospital intensive care unit and highlights the most common barriers encountered to active rehabilitation. Longer duration studies incorporating larger sample sizes are warranted. Future studies should utilise the internationally agreed intensive care unit activity codes to improve comparability.

Related Concept Videos
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:19
Restorative Care
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:22
Acute Kidney Injury VI: Nursing Management
 01:30
Continuous Renal Replacement Therapy
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...