Related Experiment Video
Updated: Feb 21, 2026


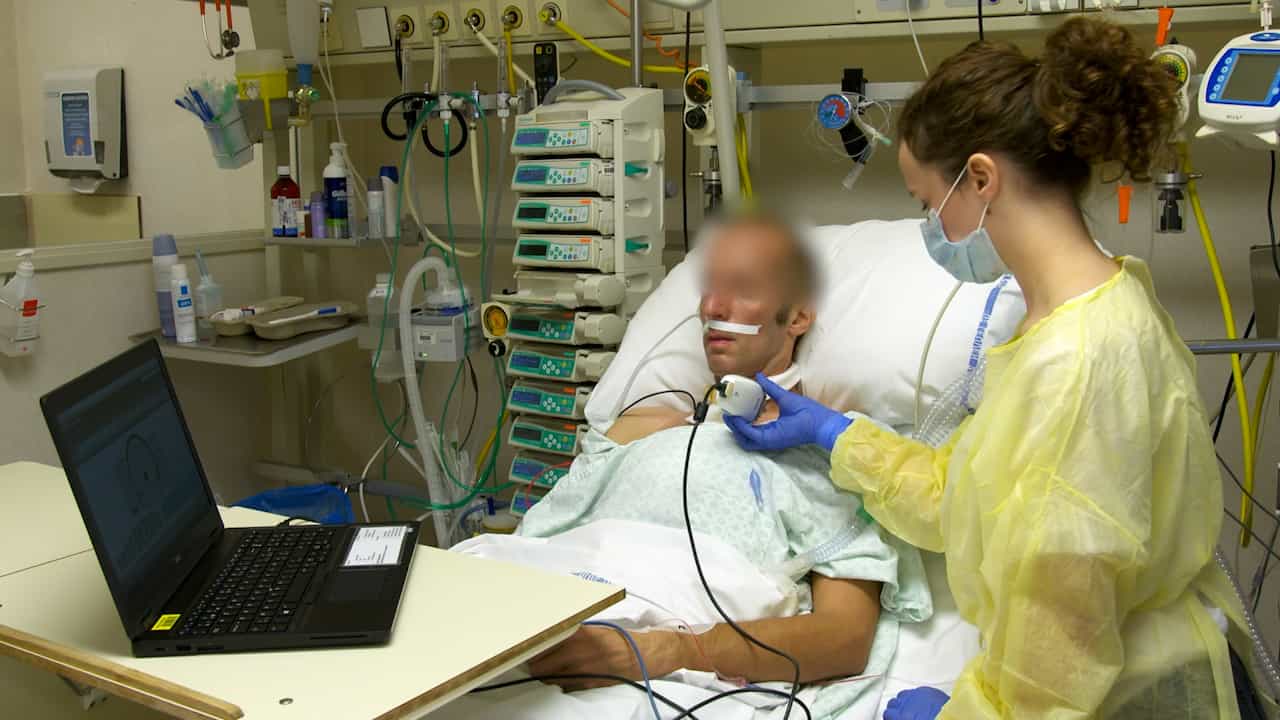
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Effect of inspiratory synchronization during pressure-controlled ventilation on lung distension and inspiratory
Nuttapol Rittayamai1,2,3, François Beloncle1,2,4, Ewan C Goligher1,5,6,7
1Interdepartmental Division of Critical Care Medicine, University of Toronto, Toronto, ON, Canada.

Background:
In pressure-controlled (PC) ventilation, tidal volume (V T) and transpulmonary pressure (P L ) result from the addition of ventilator pressure and the patient's inspiratory effort. PC modes can be classified into fully, partially, and non-synchronized modes, and the degree of synchronization may result in different V T and P L despite identical ventilator settings. This study assessed the effects of three PC modes on V T, P L , inspiratory effort (esophageal pressure-time product, PTPes), and airway occlusion pressure, P 0.1. We also assessed whether P 0.1 can be used for evaluating patient effort.
Methods:
Prospective, randomized, crossover physiologic study performed in 14 spontaneously breathing mechanically ventilated patients recovering from acute respiratory failure (1 subsequently withdrew). PC modes were fully (PC-CMV), partially (PC-SIMV), and non-synchronized (PC-IMV using airway pressure release ventilation) and were applied randomly; driving pressure, inspiratory time, and set respiratory rate being similar for all modes. Airway, esophageal pressure, P 0.1, airflow, gas exchange, and hemodynamics were recorded.
Results:
V T was significantly lower during PC-IMV as compared with PC-SIMV and PC-CMV (387 ± 105 vs 458 ± 134 vs 482 ± 108 mL, respectively; p < 0.05). Maximal P L was also significantly lower (13.3 ± 4.9 vs 15.3 ± 5.7 vs 15.5 ± 5.2 cmH2O, respectively; p < 0.05), but PTPes was significantly higher in PC-IMV (215.6 ± 154.3 vs 150.0 ± 102.4 vs 130.9 ± 101.8 cmH2O × s × min-1, respectively; p < 0.05), with no differences in gas exchange and hemodynamic variables. PTPes increased by more than 15% in 10 patients and by more than 50% in 5 patients. An increased P 0.1 could identify high levels of PTPes.
Conclusions:
Non-synchronized PC mode lowers V T and P L in comparison with more synchronized modes in spontaneously breathing patients but can increase patient effort and may need specific adjustments. Clinical Trial Registration Clinicaltrial.gov # NCT02071277.
More Related Videos
 08:25
Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
 04:12
Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Related Concept Videos
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:17
Pulmonary Cycle: Exhalation