Related Experiment Video
Updated: Feb 21, 2026
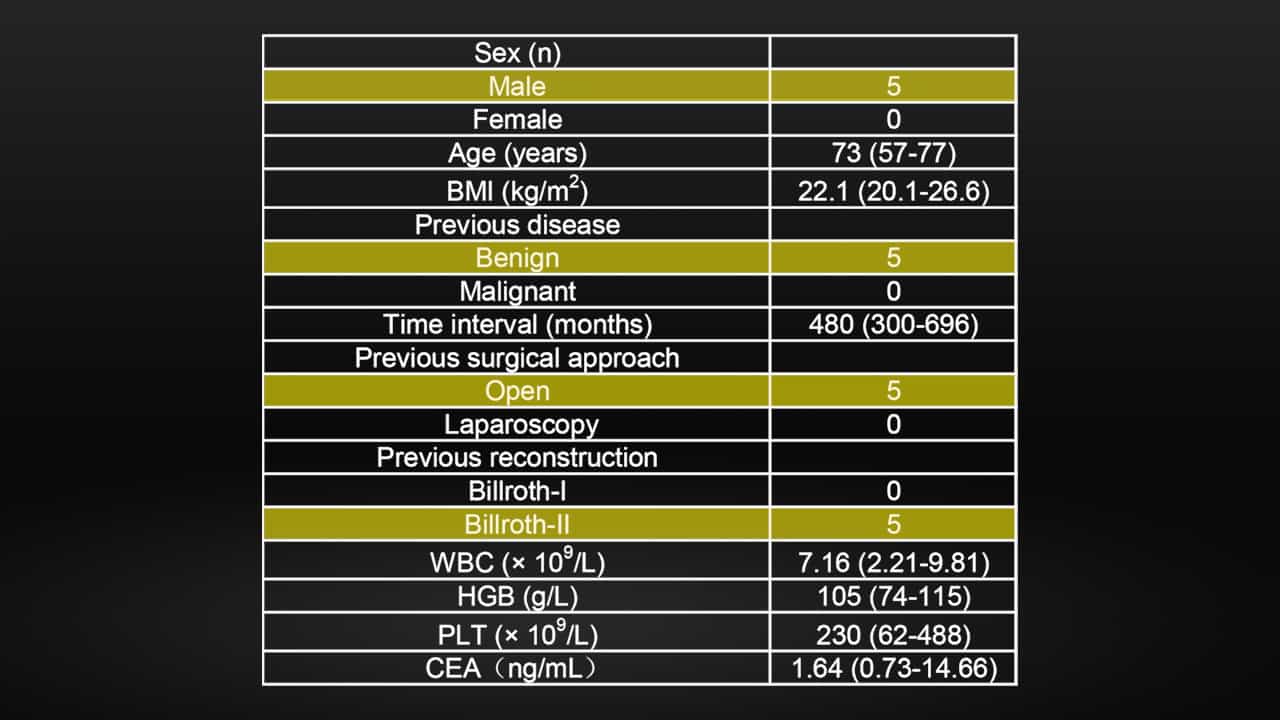
Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
Endoscopic resection versus radical gastrectomy for early gastric cancer in Asia: A meta-analysis
Fei-Long Ning1, Chun-Dong Zhang2, Peng Wang2
1Department of Gastrointestinal Surgery, The Fourth Affiliated Hospital of China Medical University, Shenyang, Liaoning, China; Department of General Surgery, Xuzhou Hospital of Traditional Chinese Medicine, Xuzhou, Jiangsu, China; Department of General Surgery, Affiliated Xuzhou Hospital of Nanjing University of Chinese Medicine, Xuzhou, Jiangsu, China.

Background:
To compare the efficacy and safety of endoscopic resection (ER) and radical gastrectomy (RG) for early gastric cancer (EGC) in Asia.
Materials And Methods:
We systematically searched relevant articles published before September 1, 2017. We evaluated the quality of the included non-randomized studies using the Newcastle-Ottawa Scale (NOS). Meta-analysis was carried out using RevMan 5.3 software. The odds ratio (OR) with 95% confidence intervals (CI) were used for the dichotomous data.
Results:
Fifteen retrospective studies were included in this analysis (3737 patients in the ER group and 4246 patients in RG group). No significant differences in the three-year survival rate (OR, 0.87; 95%CI, 0.50-1.53) and five-year survival rate (OR, 0.81; 95%CI, 0.58-1.13) between the ER and RG groups were observed. Although patients undergoing ER had a higher risk of recurrence (OR, 6.07; 95%CI 4.17-8.84) and the occurrence of metachronous cancer (OR, 8.35; 95%CI, 5.48-12.75), recurrent or metachronous gastric cancers following ER were successfully detected and removed using the endoscopic technique. Higher recurrence in the ER group may be associated with its lower en bloc resection rate (OR, 0.05; 95%CI, 0.02-0.14) and complete resection rate (OR, 0.03; 95%CI, 0.01-0.08). Importantly, although the three-year survival and five-year survival were similar in the two groups, the complication rate in the ER group was significantly lower than that in the RG group.
Conclusion:
ER is a good choice for patients with small EGC lesions (≤2 cm) without lymph node metastasis, especially in elderly patients with various medical comorbidities and in patients who cannot tolerate abdominal surgery or who meet the criteria but decline surgery. In contrast, RG is recommended when the diameter of the tumor is large (>2 cm) and preoperative examination suggests the possible presence of lymph node metastasis.
More Related Videos
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
 10:31
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016