Related Experiment Video
Updated: Feb 21, 2026
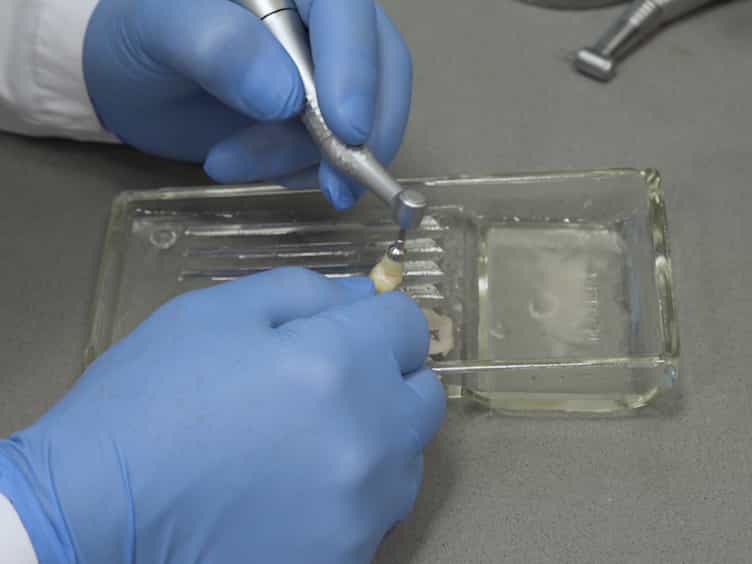

Mimicking and Measuring Occlusal Erosive Tooth Wear with the "Rub&Roll" and Non-contact Profilometry
Published on: February 2, 2018
The relationship between dentine hypersensitivity, dietary acid intake and erosive tooth wear
Saoirse O'Toole1, David Bartlett2
1Department of Tissue Engineering and Biophotonics, King's College London Dental Institute, Floor 17 Tower Wing, Guy's Hospital, London, SE1 9RT, UK.

Objectives:
To assess the interplay between dietary acid intake, toothbrushing and erosive tooth wear as aetiological factors in self-reported DH MATERIALS AND METHODS: This is a secondary analysis on previously collected data from 600 participants with (n=300) and without (n=300) severe erosive tooth wear. Participants recruited from restorative clinics of King's College London Dental Institute (REC Ref 14/EM/1171) were questioned on their self-reported DH, frequency and timing of dietary acid intake, habits associated with consumption of dietary acids and tooth brushing habits. Erosive tooth wear was assessed using Basic Erosive Wear Examination (BEWE). Differences in diet and brushing habits between those with self-reported DH and those without were analysed using descriptives and logistic regression in SPSS vers. 24.
Results:
Of those reporting with DH (n=272), a greater number spent ≥10min eating fruit per sitting, (n=46) and had a drinking habit such as sipping, swishing or holding drinks in the mouth (n=72) compared to those without DH (n=26 OR 2.72, 95%CI [1.32-5.61], p=0.007 and n=38 OR2.33, 95%CI [1.40-3.88], p=0.001, respectively). More DH participants used a soft toothbrush (n=36) compared to those without DH (n=18 OR 2.35, 95%CI [1.20-4.59], p=0.013). No association was observed with frequency of daily toothbrushing or dietary acid intake.
Conclusion:
Contact time between the tooth and the acid may be a more important risk factor for DH compared to frequency of dietary acid intake or frequency of toothbrushing. Other possible aetiological factors should be considered. CLINICALTRIALS.
Gov Number:
NCT02449434 CLINICAL SIGNIFICANCE: Increased contact time with dietary acids and sipping swishing or holding drinks in the mouth prior to swallowing should be addressed as an aetiological factor in DH. Toothpaste abrasivity and toothbrush filament stiffness may play a greater role in DH compared to frequency of toothbrushing.
Related Concept Videos
 01:21
Tooth Anatomy
The Crown, Neck, and Root
The visible part of the tooth is referred to as the crown. It's covered by enamel, the hardest substance in the human body. The crown is uniquely shaped for each type of tooth, allowing for different functions such as cutting, tearing, or...
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:31
Acid Suppressive Drugs for Peptic Ulcer Disease: Antacids
However, this neutralization reaction between...