Glecaprevir and Pibrentasvir in Patients with HCV and Severe Renal Impairment
Related Experiment Video
Updated: Feb 21, 2026

Reverse Genetics to Engineer Positive-Sense RNA Virus Variants
Published on: June 9, 2022
Edward Gane1, Eric Lawitz1, David Pugatch1
1From the Liver Unit, Auckland City Hospital, Auckland, New Zealand (E.G.); the Texas Liver Institute, University of Texas Health, San Antonio (E.L.); AbbVie, North Chicago, IL (D.P., C.C., Y.L., M.K., F.J.M.); the Academic Department of Gastroenterology, Medical School of National and Kapodistrian University of Athens, Laiko General Hospital, Athens (G.P.); the James J. Peters Veterans Affairs Medical Center, Bronx, and Icahn School of Medicine at Mount Sinai, New York - both in New York (N.B.); Imperial College Healthcare, London (A.B.); Groupe Hospitalier Cochin-Saint Vincent de Paul, Paris (S.P.), and Centre Hospitalier Universitaire de Grenoble, Grenoble (V.L.) - both in France; the Internal Medicine and Hepatology Unit, University of Salerno, Salerno (M.P.), Humanitas Clinical and Research Center, Rozzano (M.C.), and Fondazione Istituto di Ricovero e Cura a Carattere Scientifico Ca' Granda Ospedale Maggiore Policlinico, Università di Milano, Milan (M.C.) - all in Italy; Cliniques Universitaires de Bruxelles Hôpital Erasme, Université Libre de Bruxelles, Brussels (C.M.); University of British Columbia, Vancouver, Canada (E.M.Y.); and the Department of Medicine, University of Florida, Gainesville (D.R.N.).

Insights
Hepatitis C virus (HCV) infection is common in patients with chronic kidney disease (CKD). A 12-week treatment with glecaprevir and pibrentasvir achieved a 98% sustained virologic response in patients with advanced CKD.
Area of Science:
- Hepatology
- Nephrology
- Virology
Background:
- Chronic hepatitis C virus (HCV) infection is more prevalent in patients with chronic kidney disease (CKD).
- HCV infection increases the risk of end-stage renal disease (ESRD) progression in CKD patients.
- Limited treatment options exist for patients with both HCV infection and advanced CKD.
Purpose of the Study:
- To evaluate the efficacy and safety of glecaprevir/pibrentasvir in adults with HCV infection and severe renal impairment or end-stage renal disease.
- To determine the sustained virologic response rate 12 weeks after treatment completion.
Main Methods:
- A multicenter, open-label, phase 3 trial.
- 104 adult patients with HCV genotypes 1-6 and stage 4 or 5 CKD (including dialysis-dependent patients) were enrolled.
- Treatment consisted of glecaprevir and pibrentasvir for 12 weeks.
Main Results:
- A sustained virologic response rate of 98% was achieved (102/104 patients).
- No instances of virologic failure or relapse were observed.
- Common adverse events included pruritus, fatigue, and nausea; 24% experienced serious adverse events.
Conclusions:
- Glecaprevir and pibrentasvir combination therapy for 12 weeks is highly effective for treating HCV infection in patients with advanced CKD.
- The treatment regimen demonstrated a high sustained virologic response rate and was generally well-tolerated.
Background:
Chronic hepatitis C virus (HCV) infection is more prevalent among patients who have chronic kidney disease than among those who do not have the disease. Patients with chronic kidney disease who also have HCV infection are at higher risk for progression to end-stage renal disease than those who have chronic kidney disease without HCV infection. Patients with both HCV infection and advanced chronic kidney disease have limited treatment options.
Methods:
We conducted a multicenter, open-label, phase 3 trial to evaluate the efficacy and safety of treatment with the combination of the NS3/4A protease inhibitor glecaprevir and the NS5A inhibitor pibrentasvir for 12 weeks in adults who had HCV genotype 1, 2, 3, 4, 5, or 6 infection and also had compensated liver disease (with or without cirrhosis) with severe renal impairment, dependence on dialysis, or both. Patients had stage 4 or 5 chronic kidney disease and either had received no previous treatment for HCV infection or had received previous treatment with interferon or pegylated interferon, ribavirin, sofosbuvir, or a combination of these medications. The primary end point was a sustained virologic response 12 weeks after the end of treatment.
Results:
Among the 104 patients enrolled in the trial, 52% had genotype 1 infection, 16% had genotype 2 infection, 11% had genotype 3 infection, 19% had genotype 4 infection, and 2% had genotype 5 or 6 infection. The sustained virologic response rate was 98% (102 of 104 patients; 95% confidence interval, 95 to 100). No patients had virologic failure during treatment, and no patients had a virologic relapse after the end of treatment. Adverse events that were reported in at least 10% of the patients were pruritus, fatigue, and nausea. Serious adverse events were reported in 24% of the patients. Four patients discontinued the trial treatment prematurely because of adverse events; three of these patients had a sustained virologic response.
Conclusions:
Treatment with glecaprevir and pibrentasvir for 12 weeks resulted in a high rate of sustained virologic response in patients with stage 4 or 5 chronic kidney disease and HCV infection. (Funded by AbbVie; ClinicalTrials.gov number, NCT02651194 .).
Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:15
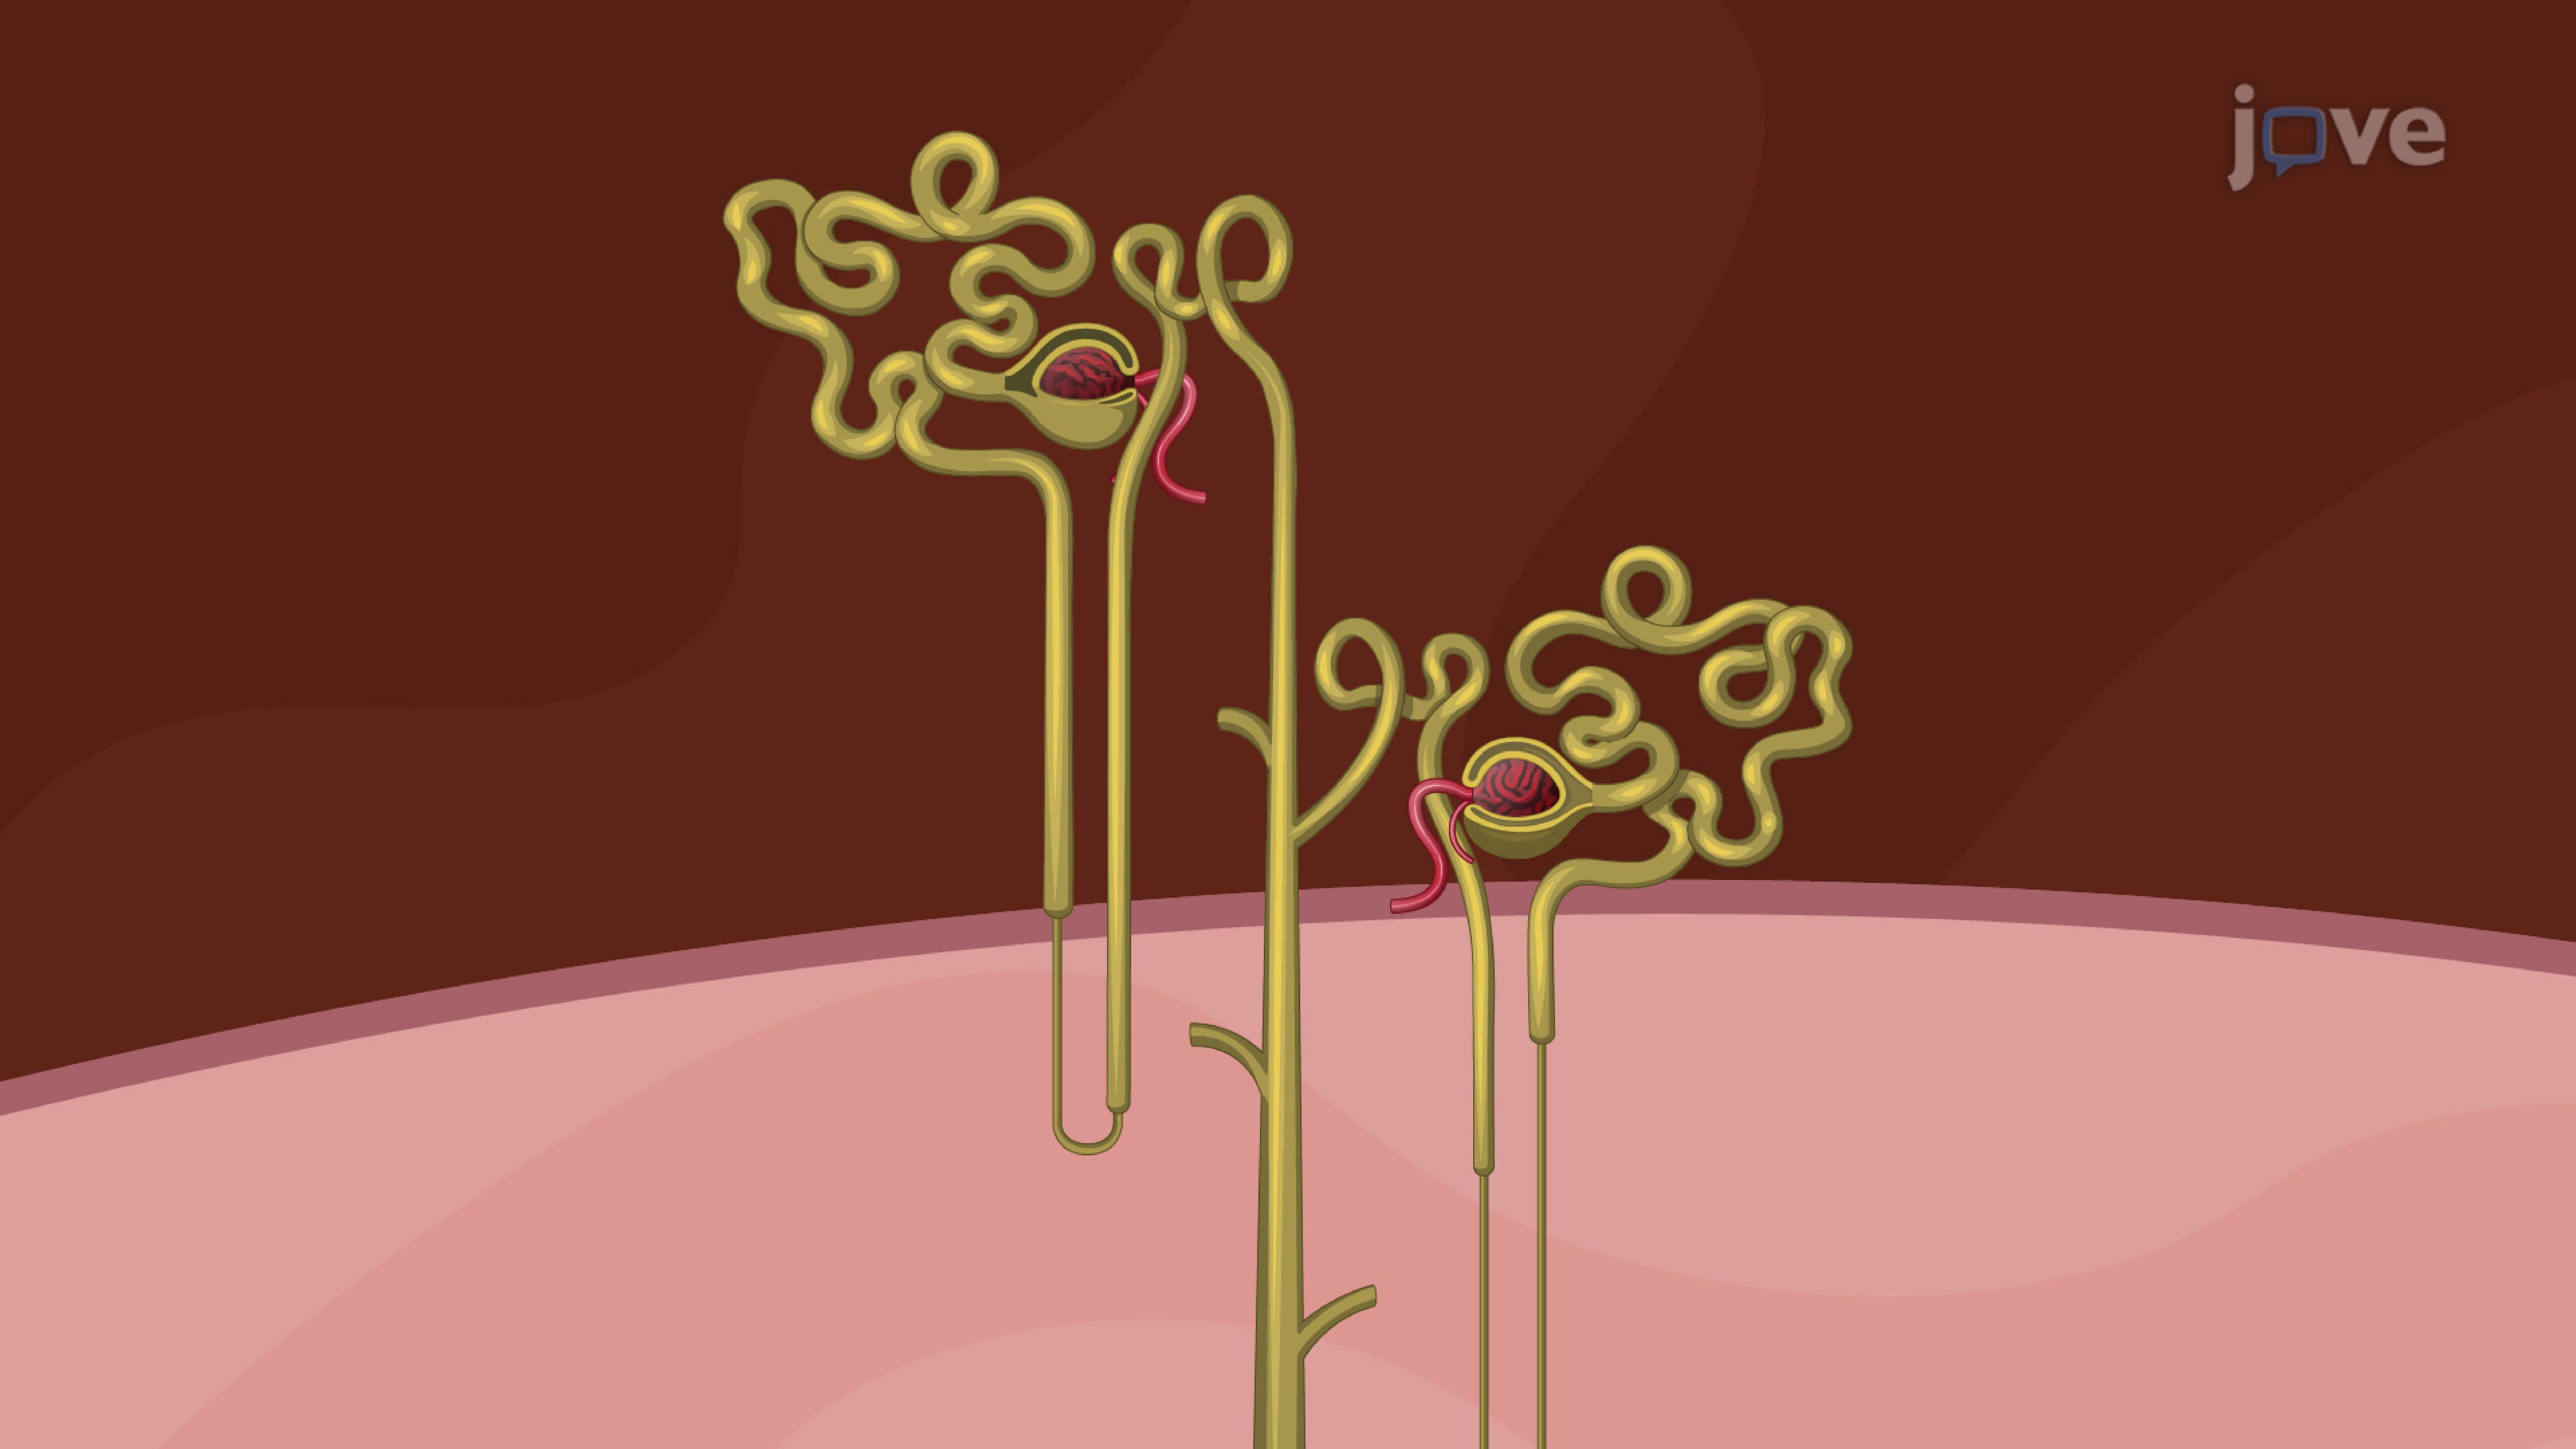
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
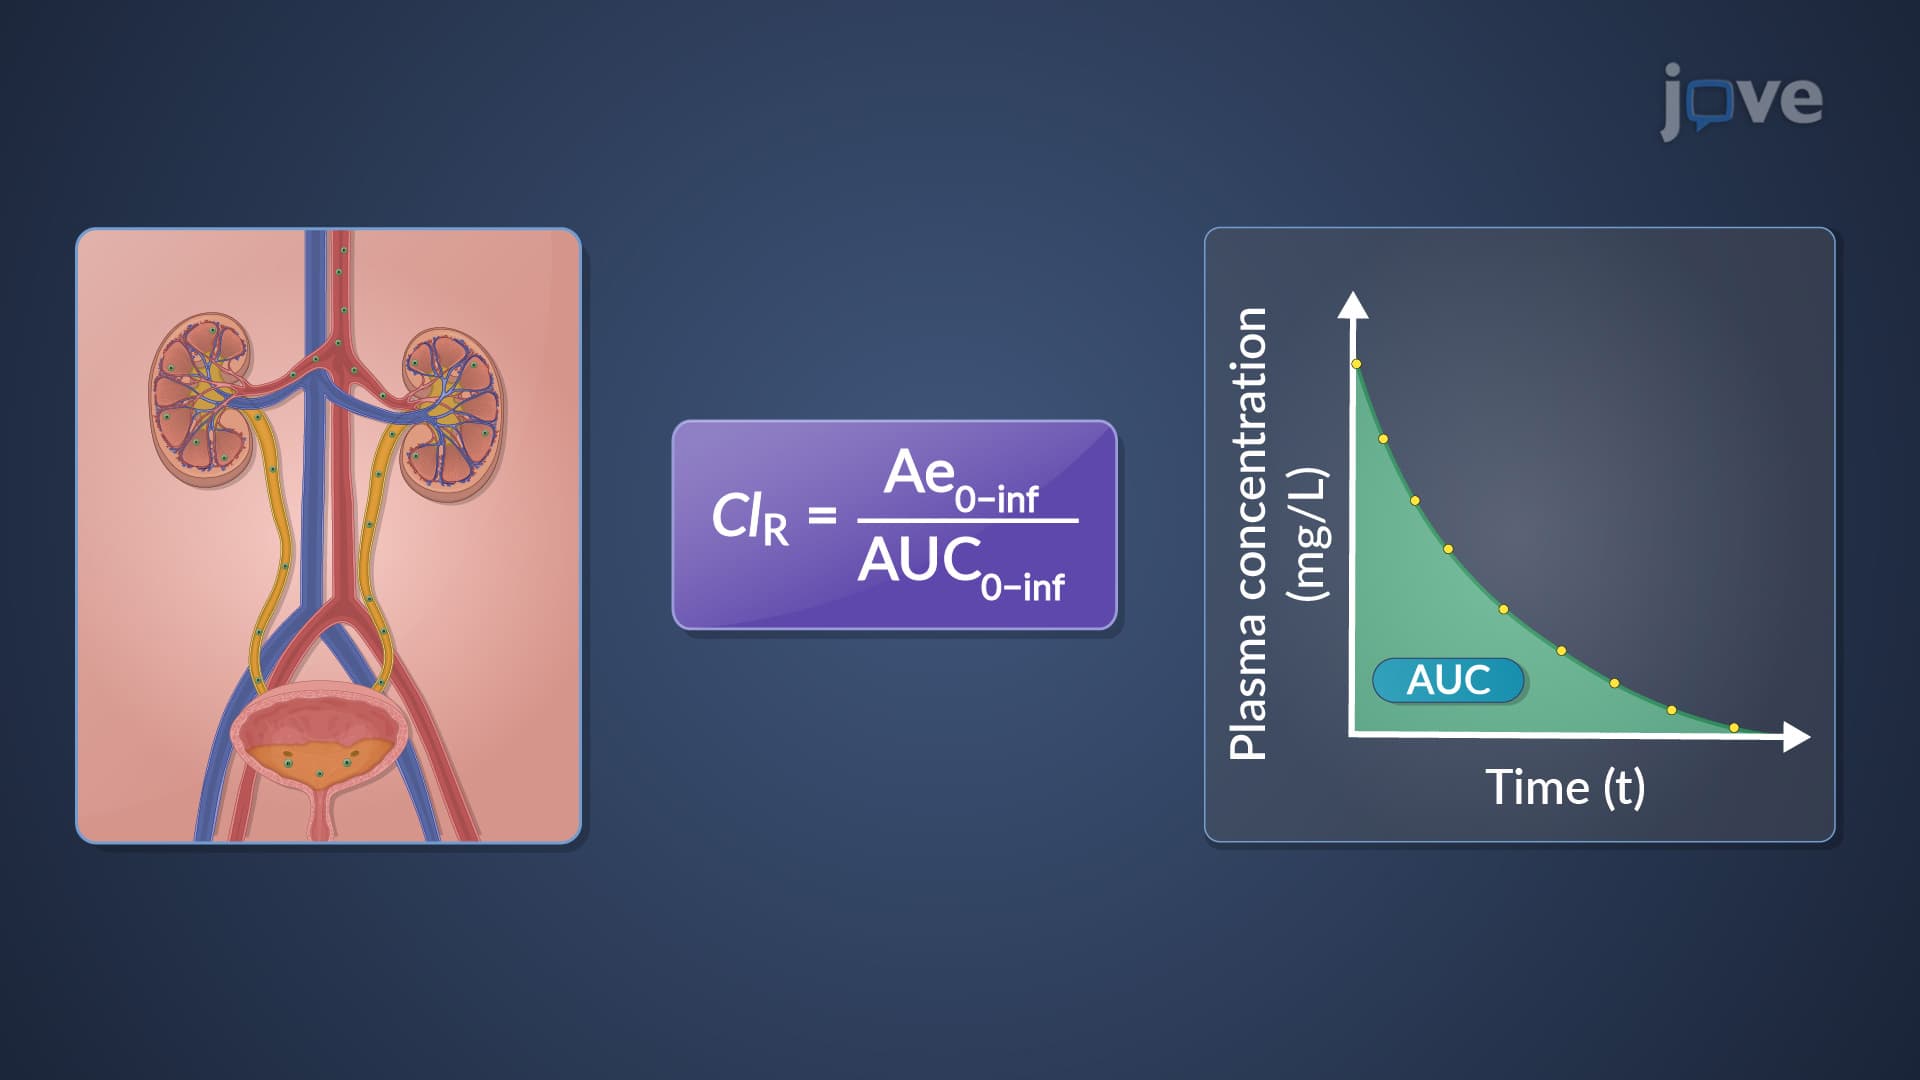
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:30
Continuous Renal Replacement Therapy