Related Experiment Video
Updated: Feb 20, 2026

Cardiopulmonary Bypass in a Mouse Model: A Novel Approach
Published on: September 22, 2017
Optimal blood pressure during cardiopulmonary bypass defined by cerebral autoregulation monitoring
Daijiro Hori1, Yohei Nomura1, Masahiro Ono2
1Division of Cardiac Surgery, Department of Surgery, The Johns Hopkins University School of Medicine, Baltimore, Md.

Insights
This study defines optimal blood pressure ranges for cerebral blood flow autoregulation during cardiopulmonary bypass. Maintaining blood pressure within these limits may reduce stroke risk and improve patient outcomes.
Area of Science:
- Neurology
- Cardiovascular Medicine
- Critical Care Medicine
Background:
- Cerebral blood flow autoregulation is crucial for maintaining brain perfusion during cardiopulmonary bypass.
- Understanding the limits of autoregulation and optimal blood pressure is vital for patient safety.
Purpose of the Study:
- To define the lower and upper limits of cerebral blood flow autoregulation during cardiopulmonary bypass.
- To identify the optimal mean arterial pressure for cerebral autoregulation.
- To determine variables that predict these autoregulation endpoints.
Main Methods:
- Continuous monitoring of cerebral autoregulation using transcranial Doppler in 614 patients.
- Calculation of the mean velocity index (MVI) using a moving Pearson's correlation coefficient between cerebral blood flow velocity and mean arterial pressure.
- Definition of autoregulation limits and optimal mean arterial pressure based on MVI values.
Main Results:
- The population mean lower and upper limits of cerebral blood flow autoregulation were 65 ± 12 mm Hg and 84 ± 11 mm Hg, respectively.
- Optimal mean arterial pressure was 78 ± 11 mm Hg.
- In a significant portion of patients, autoregulation limits deviated from the population optimum; lower limits were above optimal MAP in 17% and upper limits below in 29%.
- Nonwhite race, diuretic use, prior carotid endarterectomy, and duration of cardiopulmonary bypass were associated with optimal mean arterial pressure.
- Cerebral perfusion pressure below the lower autoregulation limit was linked to increased stroke risk.
Conclusions:
- Real-time monitoring of cerebral autoregulation can guide individualized mean arterial pressure management during cardiopulmonary bypass.
- Optimizing mean arterial pressure based on autoregulation monitoring may improve patient outcomes and reduce the incidence of stroke.
Objectives:
We sought to define the lower and upper limits of cerebral blood flow autoregulation and the optimal blood pressure during cardiopulmonary bypass. We further sought to identify variables predictive of these autoregulation end points.
Methods:
Cerebral autoregulation was monitored continuously with transcranial Doppler in 614 patients during cardiopulmonary bypass enrolled in 3 investigations. A moving Pearson's correlation coefficient was calculated between cerebral blood flow velocity and mean arterial pressure to generate the variable mean velocity index. Optimal mean arterial pressure was defined as the mean arterial pressure with the lowest mean velocity index indicating the best autoregulation. The lower and upper limits of cerebral blood flow autoregulation were defined as the mean arterial pressure at which mean velocity index was increasingly pressure passive (ie, mean velocity index ≥0.4) with declining or increasing blood pressure, respectively.
Results:
The mean (± standard deviation) lower and upper limits of cerebral blood flow autoregulation, and optimal mean arterial pressure were 65 ± 12 mm Hg, 84 ± 11 mm Hg, and 78 ± 11 mm Hg, respectively, after adjusting for study enrollment. In 17% of patients, though, the lower limit of cerebral autoregulation was above this optimal mean arterial pressure, whereas in 29% of patients the upper limit of autoregulation was below the population optimal mean arterial pressure. Variables associated with optimal mean arterial pressure based on multivariate regression analysis were nonwhite race (increased 2.7 mm Hg; P = .034), diuretics use (decreased 1.9 mm Hg; P = .049), prior carotid endarterectomy (decreased 5.5 mm Hg; P = .019), and duration of cardiopulmonary bypass (decreased 1.28 per 60 minutes of cardiopulmonary bypass). The product of the duration and magnitude that mean arterial pressure during cardiopulmonary bypass was below the lower limit of cerebral autoregulation was associated with the risk for stroke (P = .02).
Conclusions:
Real-time monitoring of autoregulation may improve individualizing mean arterial pressure during cardiopulmonary bypass and improving patient outcomes.
More Related Videos

Related Concept Videos
 01:24
Blood Pressure
 01:30
Blood Pressure
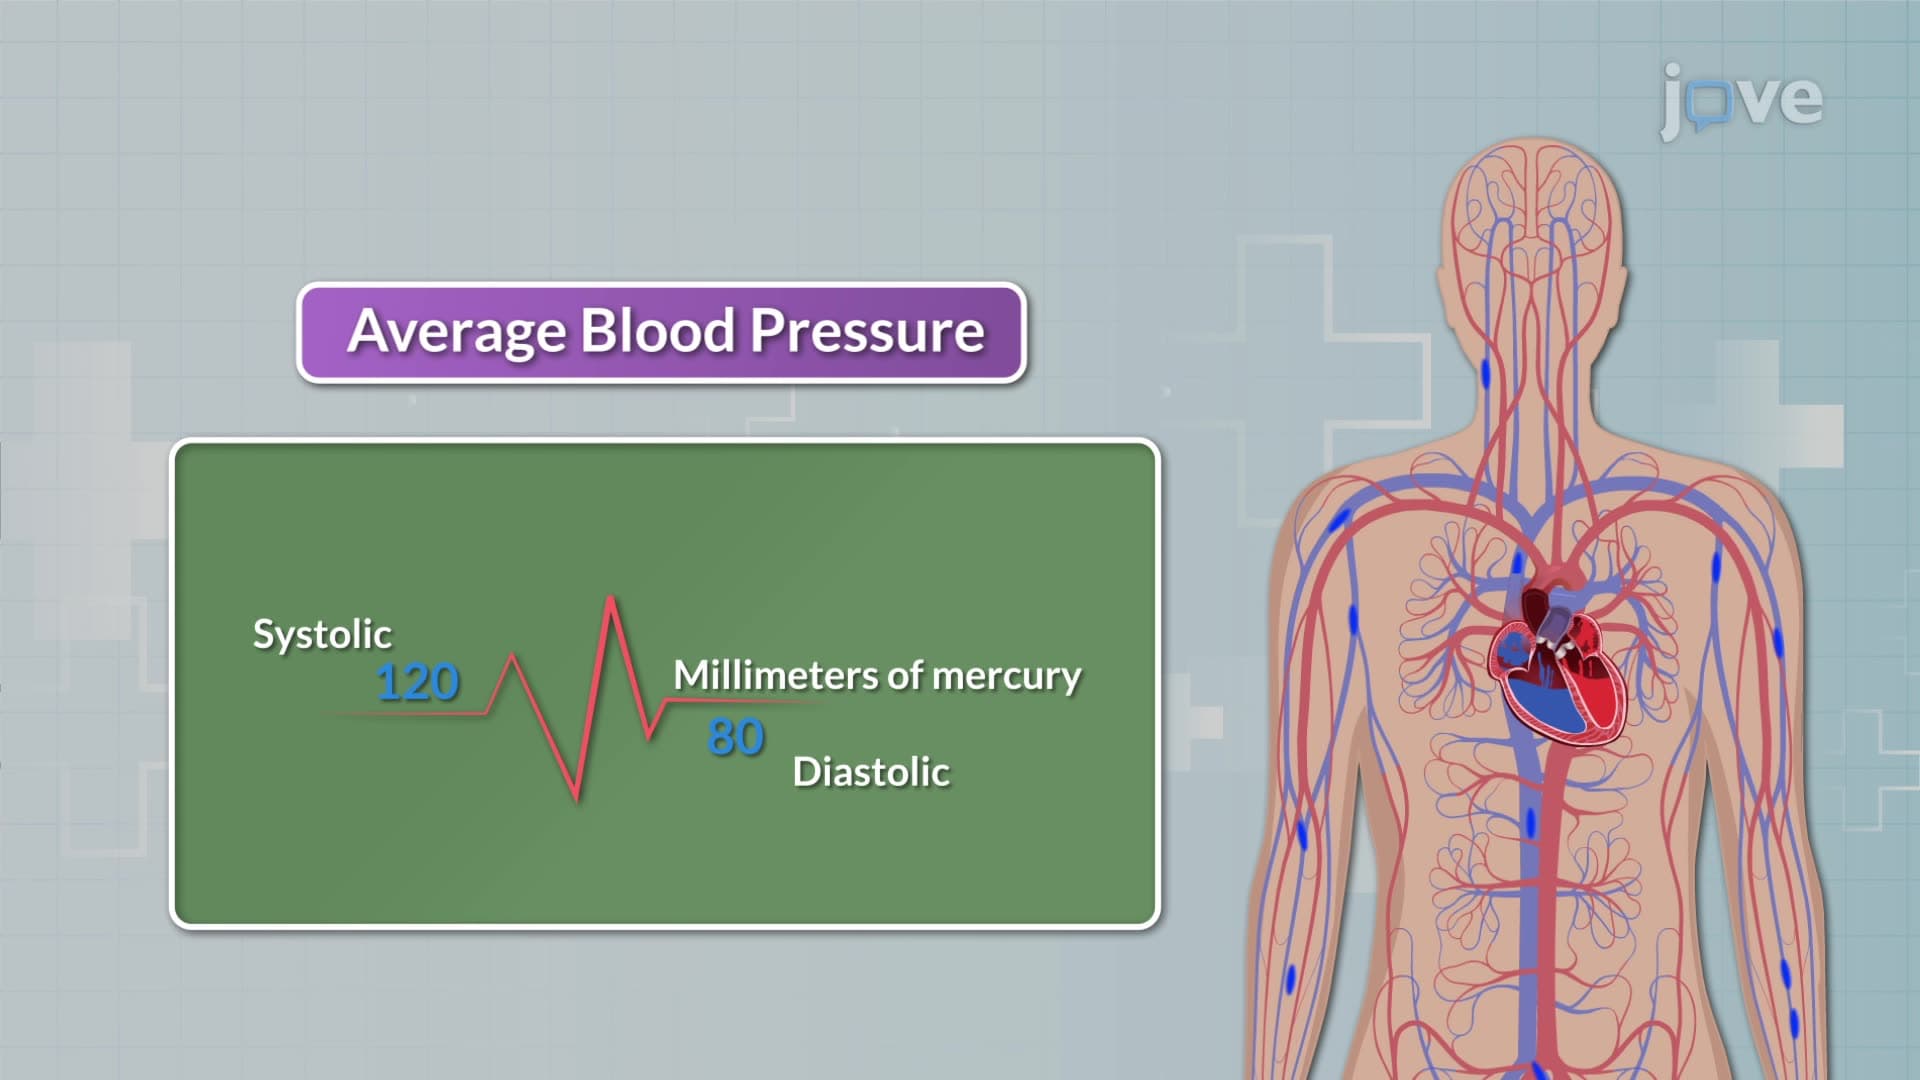
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:17
Autoregulation of Blood Flow
Chemical Signaling in Autoregulation
Chemical signaling operates at the precapillary sphincter level, inciting either contraction or relaxation....
 01:17
Measurement of Blood Pressure