Related Experiment Video
Updated: Feb 20, 2026
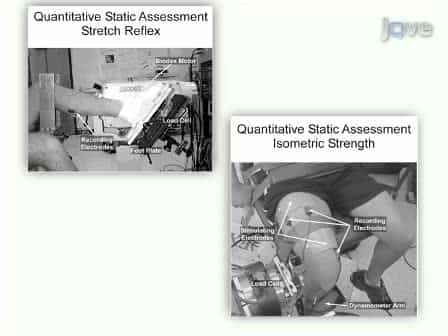

Methods to Quantify Pharmacologically Induced Alterations in Motor Function in Human Incomplete SCI
Published on: April 18, 2011
Non-pharmacological interventions for spasticity in adults: An overview of systematic reviews
Fary Khan1, Bhasker Amatya1, Djamel Bensmail2
1Department of rehabilitation medicine, Royal Melbourne Hospital, 34-54, Poplar Road, Parkville, VIC 3052, Victoria, Australia; Department of medicine, Royal Melbourne Hospital, The University of Melbourne, Parkville, Victoria, Australia; Australian Rehabilitation Research Centre, Royal Melbourne Hospital, Parkville, Victoria, Australia.

Objectives:
Spasticity causes significant long-term disability-burden, requiring comprehensive management. This review evaluates evidence from published systematic reviews of clinical trials for effectiveness of non-pharmacological interventions for improved spasticity outcomes.
Methods:
Data sources: a literature search was conducted using medical and health science electronic (MEDLINE, EMBASE, CINAHL, PubMed, and the Cochrane Library) databases for published systematic reviews up to 15th June 2017.
Data Extraction And Synthesis:
two reviewers applied inclusion criteria to select potential systematic reviews, independently extracted data for methodological quality using Assessment of Multiple Systematic Reviews (AMSTAR). Quality of evidence was critically appraised with Grades of Recommendation, Assessment, Development and Evaluation (GRADE).
Results:
Overall 18 systematic reviews were evaluated for evidence for a range of non-pharmacological interventions currently used in managing spasticity in various neurological conditions. There is "moderate" evidence for electro-neuromuscular stimulation and acupuncture as an adjunct therapy to conventional routine care (pharmacological and rehabilitation) in persons following stroke. "Low" quality evidence for rehabilitation programs targeting spasticity (such as induced movement therapy, stretching, dynamic elbow-splinting, occupational therapy) in stroke and other neurological conditions; extracorporeal shock-wave therapy in brain injury; transcranial direct current stimulation in stroke; transcranial magnetic stimulation and transcutaneous electrical nerve stimulation for other neurological conditions; physical activity programs and repetitive magnetic stimulation in persons with MS, vibration therapy for SCI and stretching for other neurological condition. For other interventions, evidence was inconclusive.
Conclusions:
Despite the available range of non-pharmacological interventions for spasticity, there is lack of high-quality evidence for many modalities. Further research is needed to judge the effect with appropriate study designs, timing and intensity of modalities, and associate costs of these interventions.
More Related Videos


Related Concept Videos
 01:29
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:24
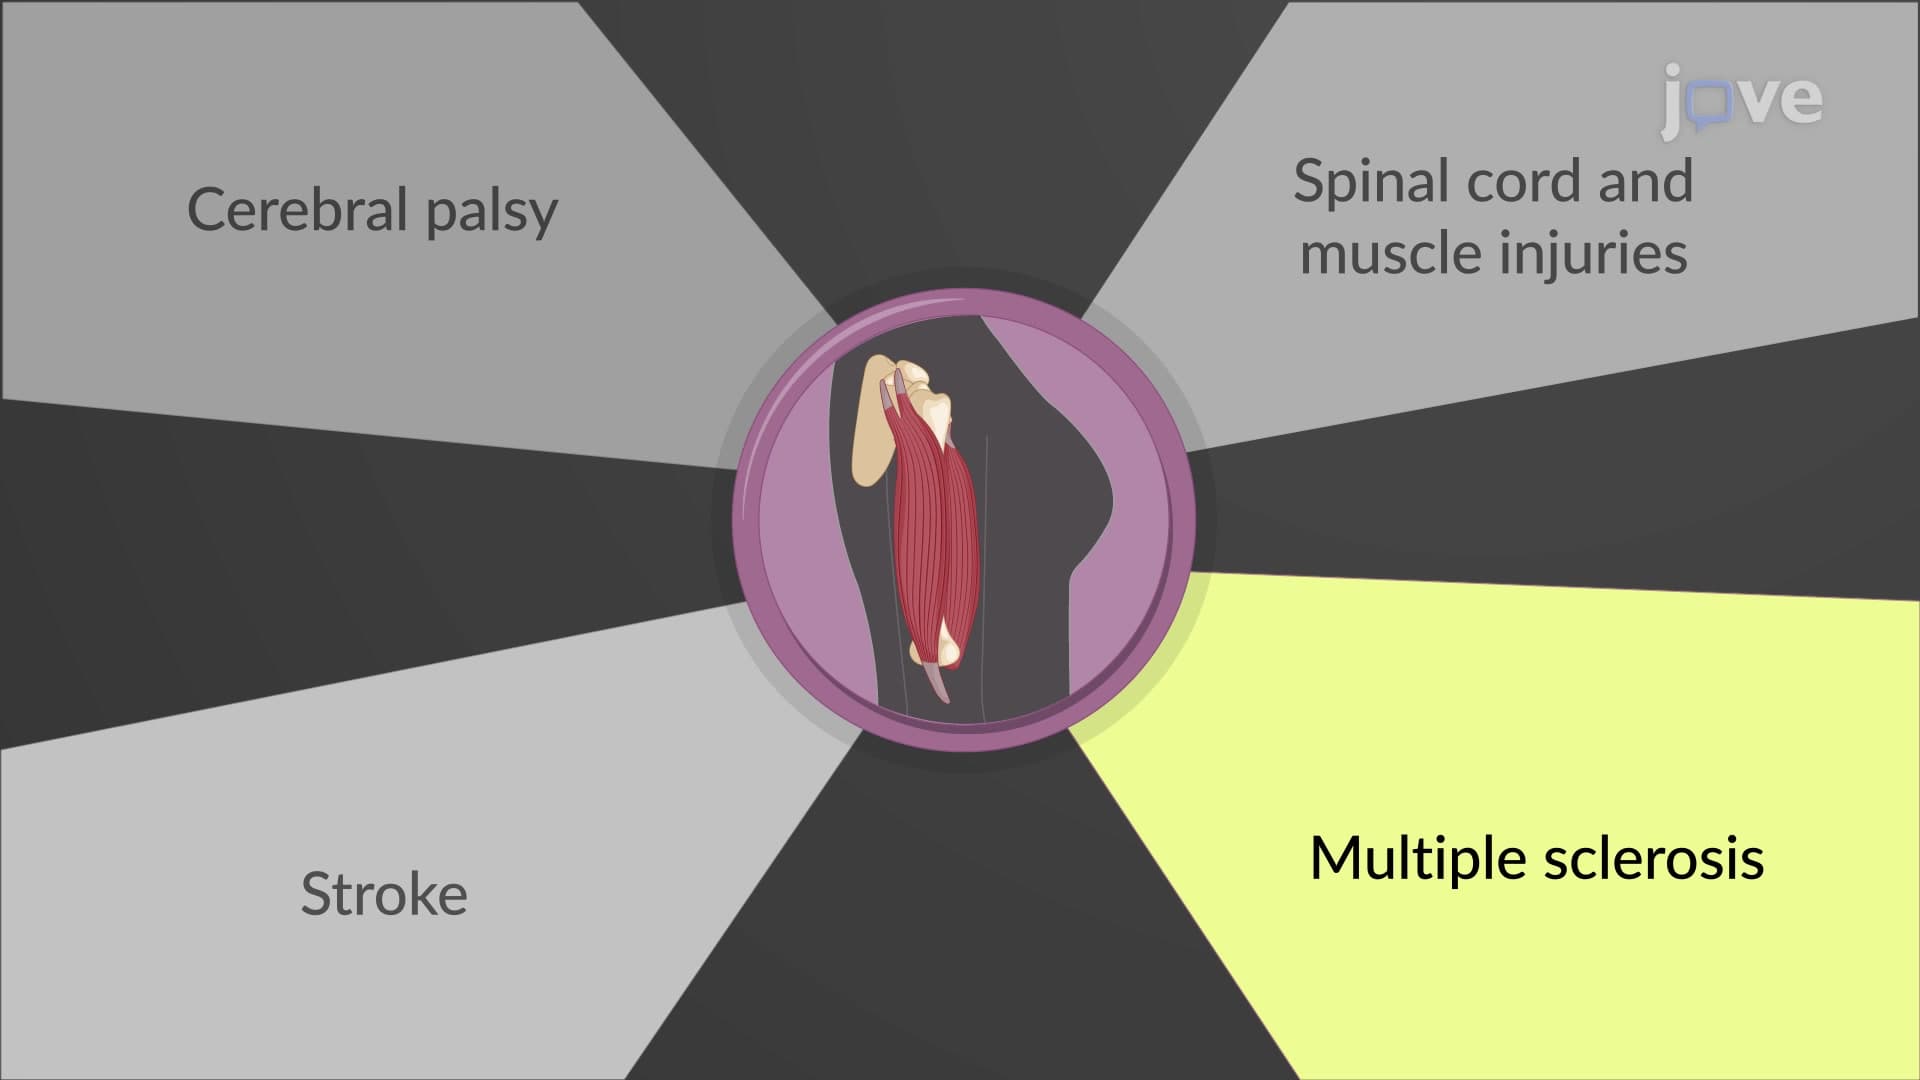
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...