Related Experiment Video
Updated: Feb 20, 2026


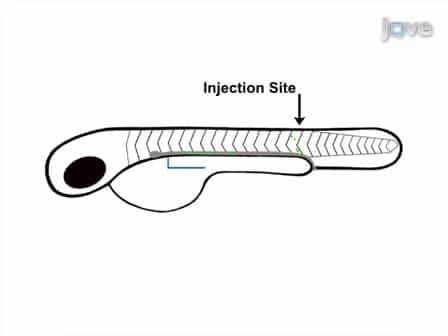
Kidney Regeneration in Adult Zebrafish by Gentamicin Induced Injury
Published on: August 3, 2015
Effects of benfotiamine and coenzyme Q10 on kidney damage induced gentamicin
Mehmet Alperen Ustuner1, Dilara Kaman1, Neriman Colakoglu2
1Department of Medical Biochemistry, Firat University School of Medicine, Elazığ, Turkey.

Objective:
Gentamicin (GM) is an effective antibiotic against severe infection but has limitations related to nephrotoxicity. In this study, we investigated whether benfotiamine (BFT) and coenzyme Q10 (CoQ10), could ameliorate the nephrotoxic effect of GM in rats.
Methods:
Rats were divided into five groups. Group 1 and 2 served as control and sham respectively, Group 3 as GM group, Group 4 as GM+CoQ10 and Group 5 as GM+BFT for 8days. At the end of the study, all rats were euthanized by cervical decapitation and then blood samples and kidneys were collected for further analysis. Serum urea, creatinine, cytokine TNF-a, oxidant and antioxidant parameters, as well as histopathological examination of kidney tissues were assessed.
Results:
Gentamicin administration caused a severe nephrotoxicity which was evidenced by an elevated serum creatinine, urea and KIM-1 level as compared with the controls. Moreover, a significant increase in serum malondialdehyde, reduced glutathione. Histopathological examination of renal tissue in gentamisin administered group, there were extremly pronounced necrotic tubules in the renal cortex and hyalen cast accumulation in the medullar tubuli. BFT given to GM rats reduced these nephrotoxicity parameters. Serum creatinine, urea, and KIM-1 were almost normalized in the GM+BFT group. Benfotiamin treatment was significantly decreased necrotic tubuli and hyalen deposition in gentamisin plus benfotiamin group. CoQ10 given to GM rats did not cause any statistically significant alterations in these nephrotoxicity parameters when compared with GM group but histopathological examination of renal tissue in GM+CoQ10 administered group, CoQ10 treatment was decreased necrotic tubuli rate and hyalen accumulation in tubuli.
Conclusion:
The results from our study indicate that BFT supplement attenuates gentamicin-induced renal injury via the amelioration of oxidative stress and inflammation of renal tubular cells.
Insights
Benfotiamine (BFT) protects against gentamicin-induced kidney damage by reducing oxidative stress and inflammation. Coenzyme Q10 (CoQ10) showed some protective effects but were less significant than BFT.
Area of Science:
- Nephrology
- Pharmacology
- Toxicology
Background:
- Gentamicin (GM) is a vital antibiotic for severe infections.
- GM use is limited by its nephrotoxicity.
- Investigating protective agents against GM-induced kidney damage is crucial.
Purpose of the Study:
- To evaluate the protective effects of benfotiamine (BFT) and coenzyme Q10 (CoQ10) against gentamicin-induced nephrotoxicity in rats.
- To assess the impact of BFT and CoQ10 on oxidative stress and inflammation markers in GM-treated rats.
Main Methods:
- Rats were administered gentamicin (GM) alone or in combination with BFT or CoQ10 for 8 days.
- Serum markers of kidney function (urea, creatinine, KIM-1) were measured.
- Oxidant/antioxidant parameters and histopathological changes in renal tissues were analyzed.
Main Results:
- GM induced significant nephrotoxicity, marked by elevated creatinine, urea, KIM-1, malondialdehyde, and reduced glutathione.
- GM treatment led to severe tubular necrosis and hyaline cast accumulation.
- BFT administration notably normalized kidney function markers and reduced histological damage.
- CoQ10 showed a trend towards reducing tubular damage but did not significantly alter measured biochemical parameters compared to GM alone.
Conclusions:
- Benfotiamine (BFT) effectively attenuates gentamicin-induced nephrotoxicity.
- BFT ameliorates renal injury by mitigating oxidative stress and inflammation.
- CoQ10 offers some protective effects, but BFT demonstrates superior renoprotective capabilities in this model.
More Related Videos

Related Concept Videos
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:22
Acute Kidney Injury I: Introduction
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion