Related Experiment Video
Updated: Feb 20, 2026
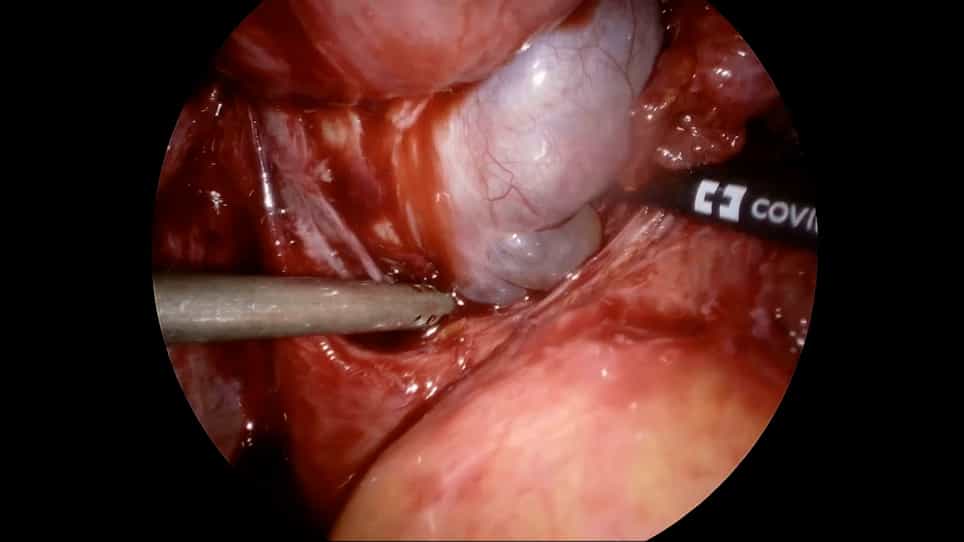
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Only complete tumour resection after neoadjuvant chemotherapy offers benefit over suboptimal debulking in advanced
Carolien K M Vermeulen1, Workineh Tadesse2, Maite Timmermans3
1Department of Gynaecologic Oncology, Mater Misericordiae University Hospital, Dublin, Ireland; Department of Obstetrics and Gynaecology, Maastricht University Medical Centre, Maastricht, The Netherlands, The Netherlands.

Objective:
The aim of this study was to compare surgical results and survival outcome of advanced ovarian cancer patients who were treated with primary versus interval debulking surgery.
Study Design:
In this retrospective study stage III and IV ovarian cancer patients who received debulking surgery from 2006 to 2015 were included. Surgical results were described as complete, optimal or suboptimal debulking and chi-square test was used to assess significant differences. Overall survival was measured using Kaplan-Meier curves, the log-rank test and uni- and multivariable Cox regression analyses.
Results:
Of 146 patients included in the study, 55 patients were treated with primary debulking surgery (PDS) followed by adjuvant chemotherapy and 91 patients received neoadjuvant chemotherapy (NAC) followed by interval debulking surgery (IDS). Complete or optimal debulking (0-10mm of residual disease) was achieved in 76.4% (n=42) of the PDS group and in 79.1% (n=72) of the IDS group. Overall median survival was 38 months for PDS and 31 months for IDS, which was not significantly different (p=0.181). In the IDS group, a significant difference was found in OS between complete and optimal resection (p=0.013). Besides that, no difference in survival outcome was found in the IDS group between patients with optimal or suboptimal debulking (median survival were 20 and 19 months respectively).
Conclusion:
Complete debulking surgery is of utmost importance, both in case of PDS and IDS. Achieving optimal interval debulking of 1-10mm residual disease did not show any survival benefit over suboptimal interval debulking.

