Related Experiment Video
Updated: Feb 19, 2026
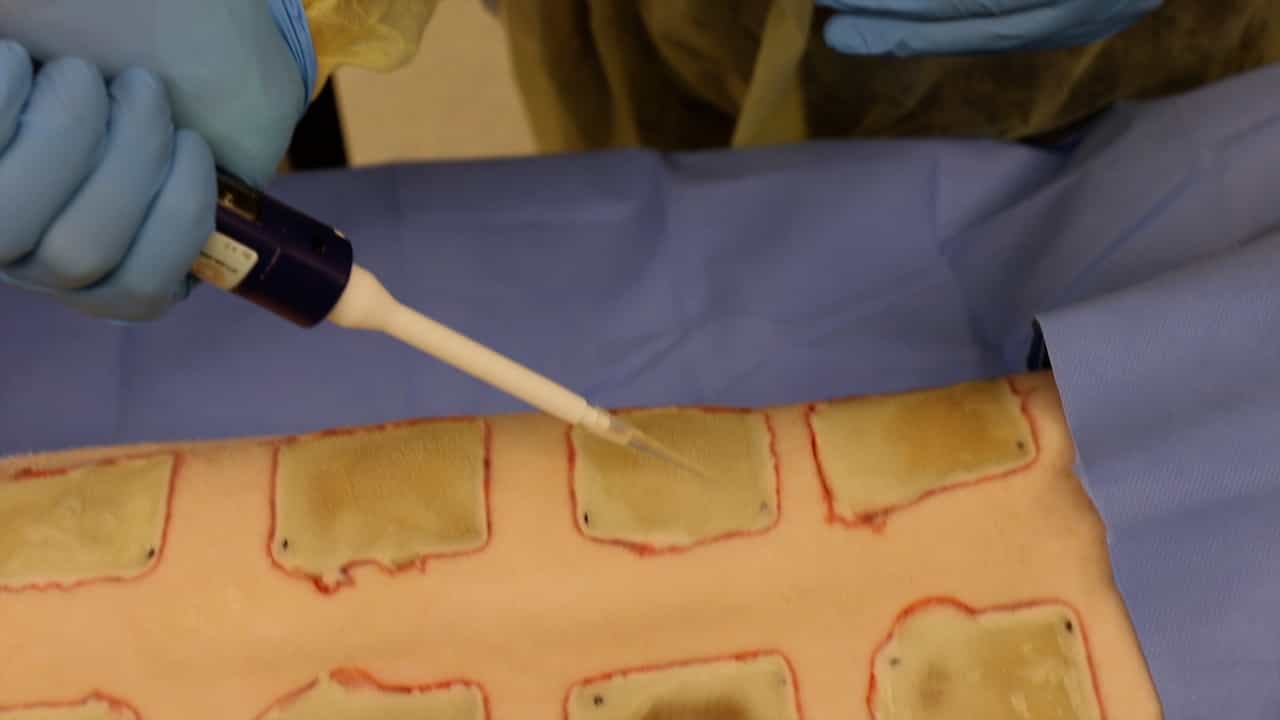

Author Spotlight: Studying Host-Microbe Interactions in Wound Biofilm Formation
Published on: June 16, 2023
[CHARACTERISTIC FEATURES OF PRESSURE ULCER INFECTION]

Abstract:
Pressure ulcer is a localized injury of the skin and/or adjacent tissue, usually above bone protrusions. It is a result of pressure or pressure combined with shear stress, friction and humidity. With regard to long life and delayed healing, it is a chronic wound. Pressure ulcer appears as a consequence of a combination of micro-embolism, ischemia and myonecrosis. These pathophysiological processes provide an ideal medium for proliferation of microorganisms, predominantly bacteria, and development of infection. Progression in the development of pressure ulcer is a dynamic process manifesting in phases, each of which is characterized by its own physiological-anatomical peculiarities and microbiological status. An open lesion without protective barrier becomes contaminated immediately, and, shortly afterwards, colonized by physiological microflora of the host and microbes from the environment. In the absence of preventive measures, the wound becomes critically colonized and infected. The characteristic of chronic wound/pressure ulcer is that it is colonized, and the infection develops depending on various factors in 5% to 80% of cases. The ability of microbes to cause infection depends on a number of factors, which include the pathogen and the host. The number and quantity of virulent factors, microbes, determines the virulence coefficient, which is responsible for overcoming the host’s immune system and development of infection. In the development of pressure ulcer infection, two essential microbial factors predominate, i.e. the presence of adhesin and association with biofilm. Thus, pressure ulcer infection as a chronic wound is characterized by a polymicrobial and heterogeneous population of microbes, domination of biofilm phenotype as a primary factor of virulence present in 90% of cases, phenotype hypervariability of species, and resistance or tolerance of the etiological agents to all types of biocides. The most significant virulence factor is biofilm. It is a corporative community of microbes with a clear architecture managed by quorum sensing molecules. It is through them that the communication between species takes place, the phenotype and virulence change, and resistance develops at the level of genome. The formation of biofilm takes place in several stages, and the speed is measured in hours. Microorganisms in the biofilm are protected from the action of the host’s immune system and, likewise, they are tolerant or resistant to antibiotics, antiseptics, and stress. Bacteria causing pressure ulcer infection are characterized as opportunistic, but also primarily pathogenic. The dominance and combination of species depend on the duration, localization and stage of pressure ulcer. The predominant etiological agents are Staphylococcus aureus, Streptococcus pyogenes, Pseudomonas aeruginosa and Peptostreptococcus spp. Nowadays, multiple-resistant strains predominate, such as MRSA, Acinetobacter spp. and Pseudomonas spp. A chronic wound such as pressure ulcer is ideal for the development of infection, especially if targeted preventive measures are not applied. The diagnosis of infection is complex and is based on the combination of primary and secondary clinical symptoms, tissue in the wound, status of the wound environment, inflammation markers, and results of microbiological examination of targeted samples – biopsies, which are the gold standard. In reaching the diagnosis of infection, it is crucial to differentiate critical colonization from deep tissue infection, which is based on clinical criteria called NERDS-STONEES. The frequency of pressure ulcer infection is 5% to 80%, and biofilm is present in 90% of cases. Due knowledge of the epidemiology of pressure ulcer and follow up of complications such as infection make the basis for the understanding of chronic wound, efforts to improve necessary care, prevention of development and application of a combination of treatment strategies.


Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:25
Urinary Tract Infection II: Pathophysiology
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:24
Inflammatory Response II: Inflammatory Exudate and Tissue Repair
The typical wound exudate is odorless, transparent, straw-colored, thin, and watery. Exudate, however, can differ depending on the state of wound healing. Likewise, the...
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis