Related Experiment Video
Updated: Feb 19, 2026


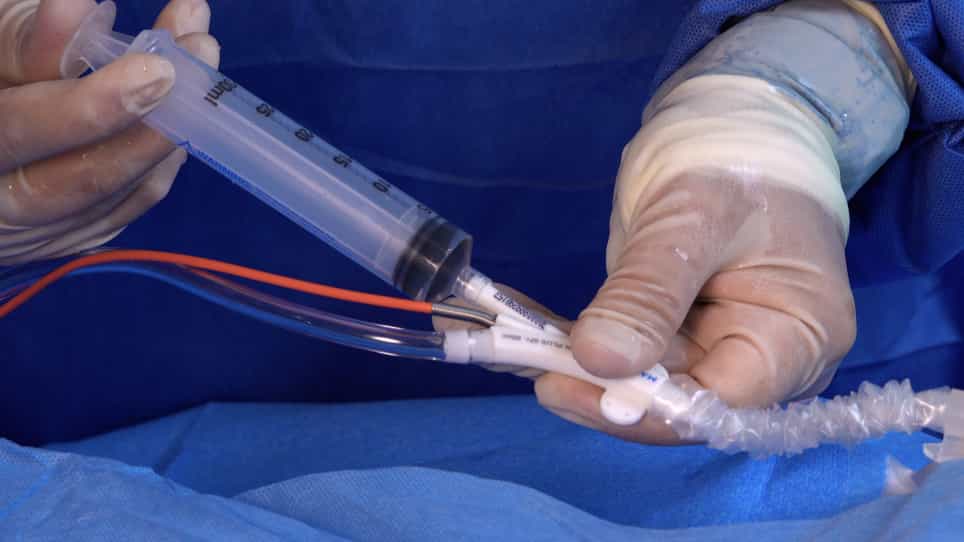
Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Cardiogenic Shock Due to End-Stage Heart Failure and Acute Myocardial Infarction: Characteristics and Outcome of
1University Hospital Birmingham, Edgbaston, Birmingham, UK.

Background:
Mechanical circulatory support (MCS) is increasingly used in cardiogenic shock, but outcomes may differ between patients with acute myocardial infarction (AMI) or end-stage heart failure (ESHF). This study aimed to describe the characteristics of patients with cardiogenic shock due to AMI and ESHF.
Methods:
Single-center study of consecutive patients with cardiogenic shock due to AMI (n = 26) and ESHF (n = 42) who underwent MCS (extracorporeal life support, Impella or temporary ventricular assist devices). Arterial and venous O2 content and CO2 tension (PCO2), O2-hemoglobin affinity (P50) were measured. Veno-arterial difference in PCO2/arterio-venous difference in O2 content ratio was derived. Acid-base balance was characterized by the Gilfix method. MCS-related complications that required intervention or surgery were collected.
Results:
Patients with ESHF had lower ejection fraction, higher right and left-sided filling pressures, pulmonary artery pressure and vascular resistance, lower oxygen delivery (DO2) compared with AMI, which was not fully compensated by the increased hemoglobin P50. As a result, patients with ESHF had higher veno-arterial difference in PCO2 relative to arterio-venous difference in O2 content. Despite greater anerobic metabolism, patients with ESHF had less severe metabolic acidosis and base deficit compared with AMI, predominantly due to differences in strong ions.
Conclusion:
The cardiogenic shock phenotype in ESHF was distinct from AMI, characterized by higher filling and pulmonary artery pressures, lower DO2, greater anaerobic metabolism but less severe metabolic acidosis.

Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:22
Heart Failure VI: Adjunct Therapies
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:30
Heart Failure V: Medical Management