Related Experiment Video
Updated: Feb 18, 2026
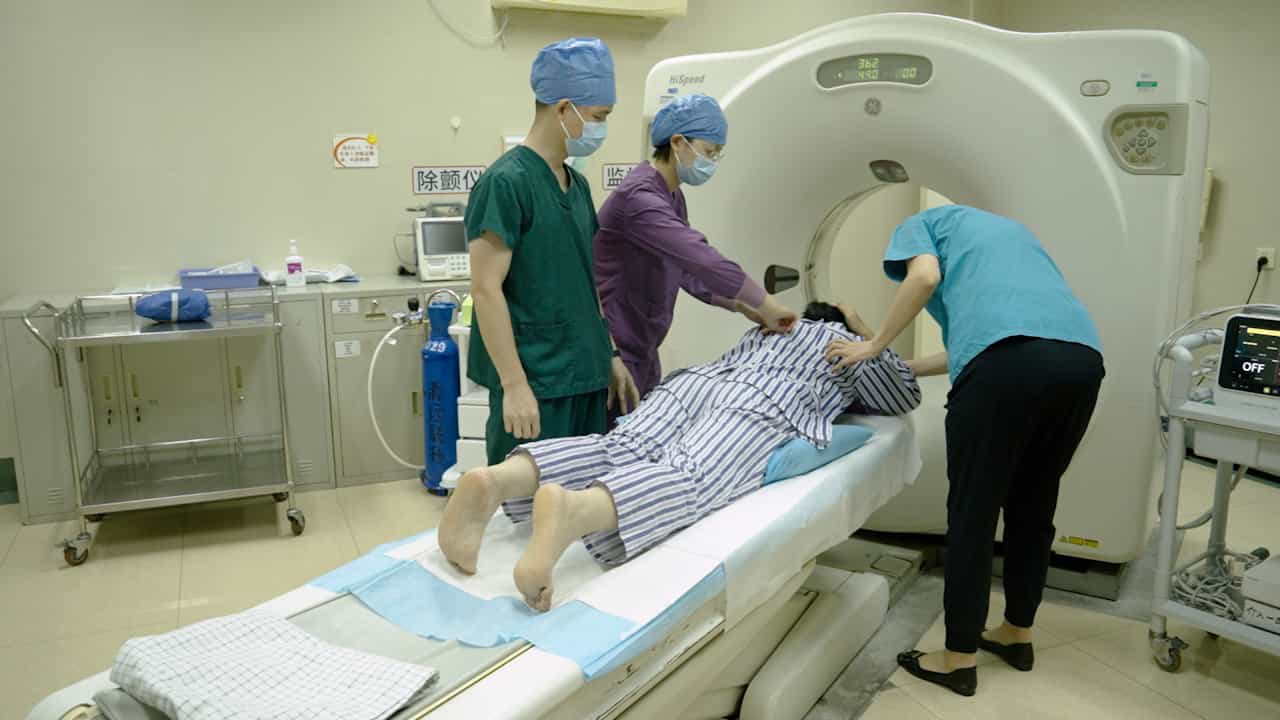
Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Hypertension Control, Apparent Treatment Resistance, and Outcomes in the Elderly Population With Chronic Kidney
Jean Kaboré1, Marie Metzger1, Catherine Helmer2,3,4
1CESP, Inserm UMR1018 Team 5, University of Paris-Sud, UVSQ, University Paris-Saclay, Villejuif, France.

Insights
This study found that chronic kidney disease (CKD) did not worsen the risk of stroke or coronary events in older adults with apparent treatment-resistant hypertension (aTRH). However, CKD was linked to higher cardiovascular mortality from other causes, even with controlled hypertension.
Area of Science:
- Nephrology
- Cardiology
- Geriatrics
Background:
- Chronic kidney disease (CKD) is linked to hypertension and treatment resistance.
- The impact of CKD on hypertension control and cardiovascular outcomes is not well understood.
Purpose of the Study:
- To investigate if CKD modifies the association between hypertension control and mortality or cardiovascular events in older adults.
- To examine the risks associated with different levels of hypertension control in the presence of CKD.
Main Methods:
- A 10-year study of 4262 community-dwelling individuals over 65 years old.
- Hypertension control status (controlled, uncontrolled, apparent treatment-resistant hypertension) and CKD (eGFR <60 ml/min/1.73m²) were assessed.
- All-cause mortality and cardiovascular events (stroke, coronary events) were recorded.
Main Results:
- 19% of participants had CKD. Apparent treatment-resistant hypertension (aTRH) was present in 6.5% of participants.
- Compared to those with controlled hypertension and no CKD, participants with CKD and controlled hypertension had a 1.33-fold increased risk of all-cause mortality.
- Participants with aTRH and CKD had over 3 times higher risk of coronary death. aTRH, with or without CKD, doubled stroke risk. CKD with controlled hypertension doubled risk of other cardiovascular deaths.
Conclusions:
- CKD does not appear to increase the risk of stroke and coronary events associated with aTRH in this elderly population.
- CKD is associated with increased cardiovascular mortality from causes other than stroke and coronary events, even with controlled hypertension.
- Further research is needed to understand the excess cardiovascular mortality observed in CKD patients with controlled hypertension.
Introduction:
Chronic kidney disease (CKD) is often associated with poor hypertension control and treatment resistance, but whether CKD modifies the effect of hypertension control on outcomes is unknown.
Methods:
We studied 10-year mortality and cardiovascular events according to hypertension control status and CKD (glomerular filtration rate <60 ml/min/1.73m2) in 4262 community-dwelling individuals (40% men) more than 65 years of age.
Results:
At baseline, 19% had CKD, and 31.2% had controlled hypertension on ≤3 antihypertensive drugs, 62.3% uncontrolled hypertension ≥140/90 mm Hg on ≤2 drugs, and 6.5% apparent treatment-resistant hypertension (aTRH) ≥140/90 mm Hg with ≥3 drugs or use of ≥4 drugs regardless of level. There were 1115 deaths (305 total cardiovascular deaths) and 274 incident nonfatal or fatal strokes or coronary events. Compared to the reference group (controlled hypertension and no CKD), participants without CKD and with uncontrolled hypertension or aTRH had adjusted hazard ratios for all-cause mortality of 0.86 (0.74-1.01) and 1.09 (0.82-1.46), and those with CKD and controlled or uncontrolled hypertension, or aTRH, of 1.33 (1.06-1.68), 1.14 (0.93-1.39), and 1.34 (0.98-1.85), respectively. Participants with aTRH and CKD had a risk of coronary death more than 3 times higher than that of the reference group; participants with aTHR, with or without CKD, had a risk of stroke more than twice as high, and those with CKD but controlled hypertension a 2 times higher risk for cardiovascular deaths from other causes.
Discussion:
CKD does not appear to amplify the risk of stroke and coronary events associated with aTRH in this older population. The reasons for excess cardiovascular mortality from other causes associated with controlled hypertension require further study.


Related Concept Videos
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:15
Drug Dosing: Geriatric Patients
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:18
Hypertension and Regulation of Blood Pressure