Related Experiment Video
Updated: Feb 17, 2026
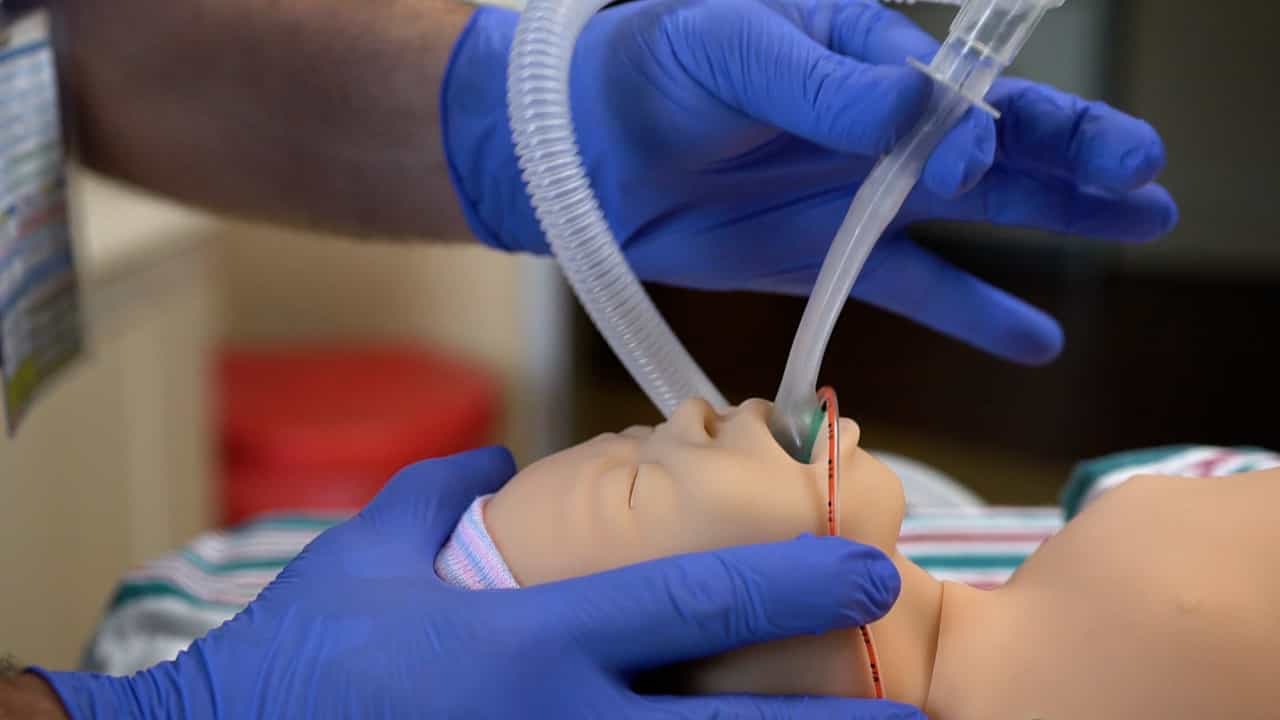

Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Premature birth affects the degree of airway dysanapsis and mechanical ventilatory constraints
Joseph W Duke1, Igor M Gladstone2, A William Sheel3
1Department of Biological Sciences, Northern Arizona University, Flagstaff, AZ, USA.

Insights
Adult survivors of preterm birth (PRE) and bronchopulmonary dysplasia (BPD) have smaller airways, indicated by a reduced dysanapsis ratio. This anatomical difference contributes to their airflow obstruction during rest and exercise.
Area of Science:
- Pulmonary Medicine
- Neonatology
- Pediatric Pulmonology
Background:
- Adult survivors of very preterm birth (≤32 weeks gestational age) often exhibit obstructive lung disease.
- Bronchopulmonary dysplasia (BPD) is a chronic lung disease that can arise from prematurity and neonatal oxygen therapy.
- Airflow obstruction can result from various factors, including smaller airway dimensions.
Purpose of the Study:
- To investigate whether adult survivors of preterm birth without (PRE) and with bronchopulmonary dysplasia (BPD) have smaller airways compared to full-term controls (CON).
- To assess the dysanapsis ratio (DR) as an index of airway size in these groups.
- To determine if airway size correlates with airflow limitation at rest and during exercise.
Main Methods:
- Calculation of the dysanapsis ratio (DR) in three groups: PRE (n=21), BPD (n=14), and CON (n=34).
- Analysis of flow-volume loops at rest and during submaximal exercise.
- Estimation of static recoil pressure to determine DR.
Main Results:
- The DR was significantly smaller in both PRE and BPD groups compared to CON (P < 0.001).
- The BPD group exhibited the smallest DR, indicating the most significant airway narrowing.
- DR showed significant correlations with peak expiratory airflow at rest (r=0.42) and expiratory flow limitation during exercise (r=0.60).
Conclusions:
- Adult survivors of preterm birth, particularly those with BPD, may have anatomically smaller airways.
- Smaller airways likely contribute to the observed airflow obstruction at rest and exercise limitations in PRE and BPD survivors.
- These findings enhance understanding of long-term respiratory consequences of preterm birth and neonatal care.
New Findings:
What is the central question of this study? Adult survivors of preterm birth without (PRE) and with bronchopulmonary dysplasia (BPD) have airflow obstruction at rest and significant mechanical ventilatory constraints during exercise compared with those born at full term (CON). Do PRE/BPD have smaller airways, indexed via the dysanapsis ratio, than CON? What is the main finding and its importance? The dysanapsis ratio was significantly smaller in BPD and PRE compared with CON, with BPD having the smallest dysanapsis ratio. These data suggest that airflow obstruction in PRE and BPD might be because of smaller airways than CON. Adult survivors of very preterm birth (≤32 weeks gestational age) without (PRE) and with bronchopulmonary dysplasia (BPD) have obstructive lung disease as evidenced by reduced expiratory airflow at rest and have significant mechanical ventilatory constraints during exercise. Airflow obstruction, in any conditions, could be attributable to several factors, including small airways. PRE and/or BPD could have smaller airways than their counterparts born at full term (CON) owing to a greater degree of dysanaptic airway development during the pre- and/or postnatal period. Thus, the purpose of the present study was to compare the dysanapsis ratio (DR), as an index of airway size, between PRE, BPD and CON. To do so, we calculated DR in PRE (n = 21), BPD (n = 14) and CON (n = 34) individuals and examined flow-volume loops at rest and during submaximal exercise. The DR, using multiple estimates of static recoil pressure, was significantly smaller in PRE and BPD (0.16 ± 0.05 and 0.10 ± 0.03 a.u.) compared with CON (0.22 ± 0.04 a.u.; both P < 0.001) and smallest in BPD (P < 0.001). The DR was significantly correlated with peak expiratory airflow at rest (r = 0.42; P < 0.001) and the extent of expiratory flow limitation during exercise (r = 0.60; P < 0.001). Our findings suggest that PRE/BPD might have anatomically smaller airways than CON, which might help to explain their lower expiratory airflow rate at rest and during exercise and further our understanding of the consequences of preterm birth and neonatal O2 therapy.

Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:05
Breathing
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings