Related Experiment Video
Updated: Feb 17, 2026
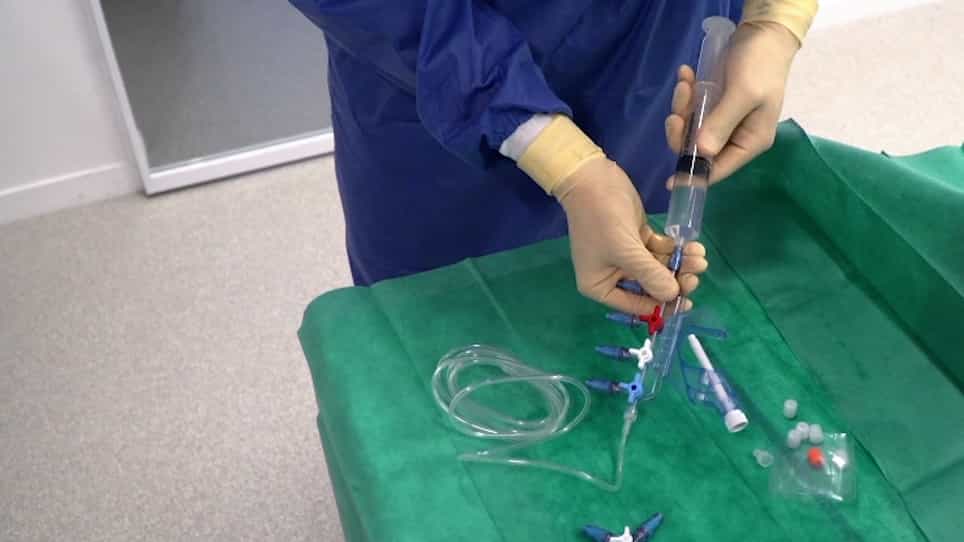
A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Unit-Level Changes in Central Line-Associated Bloodstream Infection Before and After Implementation of the Affordable
Benjamin C Woodward1, Reba A Umberger
1Benjamin C. Woodward, RN, BSN, is a nurse in the trauma-surgical/neuro critical care unit at the hospital studied. This work was completed under the guidance of Dr. Umberger as part of the Nursing Honors Program at the University of Tennessee, Knoxville. Reba A. Umberger, PhD, RN, CCRN-K, is an assistant professor in the College of Nursing, Department of Acute and Tertiary Care at the University of Tennessee Health Science Center in Memphis, TN. She served as Mr. Woodward's Nursing Honors Program mentor prior to relocating from the College of Nursing at the University of Tennessee in Knoxville, TN. Dr. Umberger's program of research is focused on immune suppression in patients with sepsis (including genetic, epigenetic, and environmental risk factors for subsequent infection) and long term outcomes in survivors of sepsis and their informal caregivers.

Insights
Legislation and mandatory reporting laws have influenced central line-associated bloodstream infection (CLABSI) rates. While CLABSI numbers decreased, further research is needed to confirm legislative impact.
Area of Science:
- Healthcare-associated infection (HAI) prevention
- Public health policy and legislation
- Infection control and epidemiology
Background:
- Increased focus on Central Line-Associated Bloodstream Infection (CLABSI) prevention due to the Affordable Care Act and mandatory reporting.
- Legislative measures link hospital reimbursement to CLABSI rates and other healthcare-associated infections.
Purpose of the Study:
- To investigate the impact of legislation and mandatory reporting on CLABSI rates.
- To examine changes in CLABSI reporting methodologies over time.
Main Methods:
- Retrospective review of medical intensive care unit patients in 2008, 2012, and 2015.
- Analysis of CLABSI reporting via International Classification of Diseases (ICD) and Centers for Disease Control (CDC) by infection prevention (IP).
- Comparison of central line usage and calculation of percent agreement and κ statistics for reported CLABSIs.
Main Results:
- A decrease in reported CLABSIs was observed from 2 in 2008 to 0 in 2015.
- Excellent agreement (99.6% and κ=0.799) was found between ICD and IP reporting methods.
- Central line usage remained consistent across the study periods.
Conclusions:
- The study suggests a potential decrease in CLABSIs, possibly influenced by legislative changes, but requires larger sample sizes for definitive conclusions.
- Discrepancies between reporting methods were noted, aligning with previous research.
- Further investigation into provider coding practices and evolving central line utilization is recommended.
Background:
Central line-associated bloodstream infection (CLABSI) prevention efforts have increased over the past decade because of implications of the Affordable Care Act and mandatory reporting laws. These legislative measures allow for reduced reimbursement to hospitals with high level of CLABSIs and other health care-associated infections.
Objective:
The aim of this study was to explore the impact of legislation and mandatory reporting on CLABSI rates and reporting.
Methods:
The study team performed a retrospective review of medical intensive care unit patients in January 2008, 2012, and 2015 to examine changes in CLABSI reporting by 2 methods (International Classification of Diseases [ICD] by providers and Centers for Disease Control by infection prevention [IP]), as well as changes in central line use over time. Data were summarized and compared. Percent agreement and κ statistics were calculated for ICD- and IP-coded CLABSIs.
Results:
Among 465 intensive care unit patients, most were white (89.9%), males (52.0%), aged 58.7 ± 17.1 years. Only 3 new CLABSIs were reported during the study period: 2 by ICD and IP in 2008, 1 by ICD in 2012, and 0 by either method in 2015. The percent agreement (99.6%) and κ (0.799) represent excellent agreement. Central line usage was similar for each time period.
Discussion:
The number of CLABSIs decreased over time; however, the findings were limited, and a larger sample over a longer period is needed to draw conclusions about the influence of legislative changes. One discrepancy was observed between the 2 reporting methods, which is consistent with other studies. More research is needed to understand the complexity of provider coding practices and changes in central line use (eg, duration, type, location) over time.


Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:21
Types of Reports II: Incident or Occurrence Report
Purposes:
In the healthcare industry, reports play a crucial role in documenting incidents within an agency. The primary objective of these reports is to ensure patient safety, uphold the...
 01:22
Standards of Care I
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:30
Health Information Technology and Healthcare Information System
Health Information Technology, commonly called HIT, integrates advanced information systems and technology in healthcare settings. Its primary functions include:
 01:25
Types of Reports I: Hands-off Report
Following are the key components and categories of hand-off reports:
Purpose and Process: