
Background and distribution of lobar microbleeds in cognitive dysfunction
Hirofumi Matsuyama1, Yuichiro Ii1, Masayuki Maeda2
1Department of Neurology Mie University Graduate School of Medicine Tsu Mie Japan.

Objectives:
Cerebral microbleeds (CMBs) are often observed in memory clinic patients. It has been generally accepted that deep CMBs (D-CMBs) result from hypertensive vasculopathy (HV), whereas strictly lobar CMBs (SL-CMBs) result from cerebral amyloid angiopathy (CAA) which frequently coexists with Alzheimer's disease (AD). Mixed CMBs (M-CMBs) have been partially attributed to HV and also partially attributed to CAA. The aim of this study was to elucidate the differences between SL-CMBs and M-CMBs in terms of clinical features and regional distribution.
Materials:
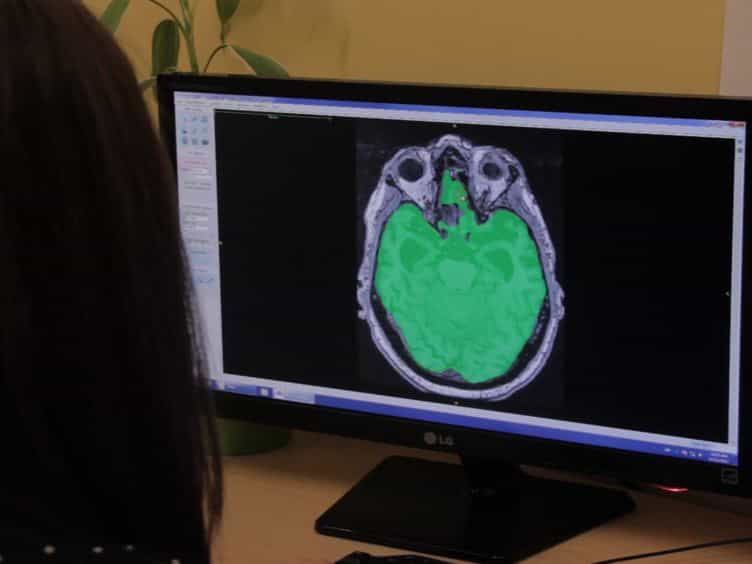
We examined 176 sequential patients in our memory clinic for clinical features and CMB location using susceptibility-weighted images obtained on a 3T-MRI. The number of lobar CMBs in SL-CMBs and M-CMBs was counted in each cerebral lobe and their regional density was adjusted according to the volume of each lobe.
Results:
Of the total 176 patients, 111 patients (63.1%) had CMBs. Within the patients who had CMBs, M-CMBs were found in 54 patients (48.6%), followed by SL-CMBs in 35 (31.5%) and D-CMBs in 19 (17.1%). The SL-CMB group showed a significantly higher prevalence of family history of dementia, whereas the M-CMB group showed an increasing trend toward hypertension and smoking. The prevalence of AD was significantly higher in the SL-CMBs group, whereas the prevalence of AD with cerebrovascular disease was higher in the M-CMBs group. The regional density of lobar CMBs was significantly higher in the occipital lobe in the M-CMB group, whereas the SL-CMB group showed higher regional density between regions an increasing tendency in the parietal and occipital lobe.
Conclusion:
The between-group differences in clinical features and regional distribution indicate there to be an etiological relationship of SL-CMBs to AD and CAA, and M-CMBs to both HV and CAA.
Insights
Strictly lobar cerebral microbleeds (SL-CMBs) are linked to Alzheimer's disease (AD) and cerebral amyloid angiopathy (CAA), while mixed CMBs (M-CMBs) are associated with both HV and CAA in memory clinic patients.
Area of Science:
- Neurology
- Radiology
- Pathology
Background:
- Cerebral microbleeds (CMBs) are common in memory clinic patients.
- Deep CMBs (D-CMBs) are typically linked to hypertensive vasculopathy (HV), while strictly lobar CMBs (SL-CMBs) are associated with cerebral amyloid angiopathy (CAA), often co-occurring with Alzheimer's disease (AD).
- Mixed CMBs (M-CMBs) are thought to result from both HV and CAA.
Purpose of the Study:
- To differentiate between SL-CMBs and M-CMBs based on clinical characteristics and anatomical distribution.
- To investigate the etiological underpinnings of different CMB subtypes.
Main Methods:
- Analysis of 176 memory clinic patients using 3T-MRI with susceptibility-weighted imaging.
- Quantification and regional density adjustment of lobar CMBs in SL-CMB and M-CMB groups.
- Correlation of CMB location with clinical features, including dementia history, hypertension, smoking, AD, and cerebrovascular disease.
Main Results:
- CMBs were present in 63.1% of patients; M-CMBs were most frequent (48.6%), followed by SL-CMBs (31.5%).
- SL-CMB patients showed higher dementia history prevalence and AD, while M-CMB patients had trends toward hypertension, smoking, and co-existing AD with cerebrovascular disease.
- M-CMBs had higher regional density in the occipital lobe, whereas SL-CMBs showed increased density in parietal and occipital lobes.
Conclusions:
- Clinical and regional distribution differences support an etiological link between SL-CMBs and AD/CAA.
- M-CMBs appear to be associated with both hypertensive vasculopathy (HV) and cerebral amyloid angiopathy (CAA).
- These findings aid in understanding the distinct pathologies underlying different CMB presentations.

Related Concept Videos
 01:17
Hemorrhagic Stroke l: Introduction
 01:23
Alzheimer Disease ll: Pathophysiology
 01:22
Dementia l: Introduction