Related Experiment Video
Updated: Feb 17, 2026
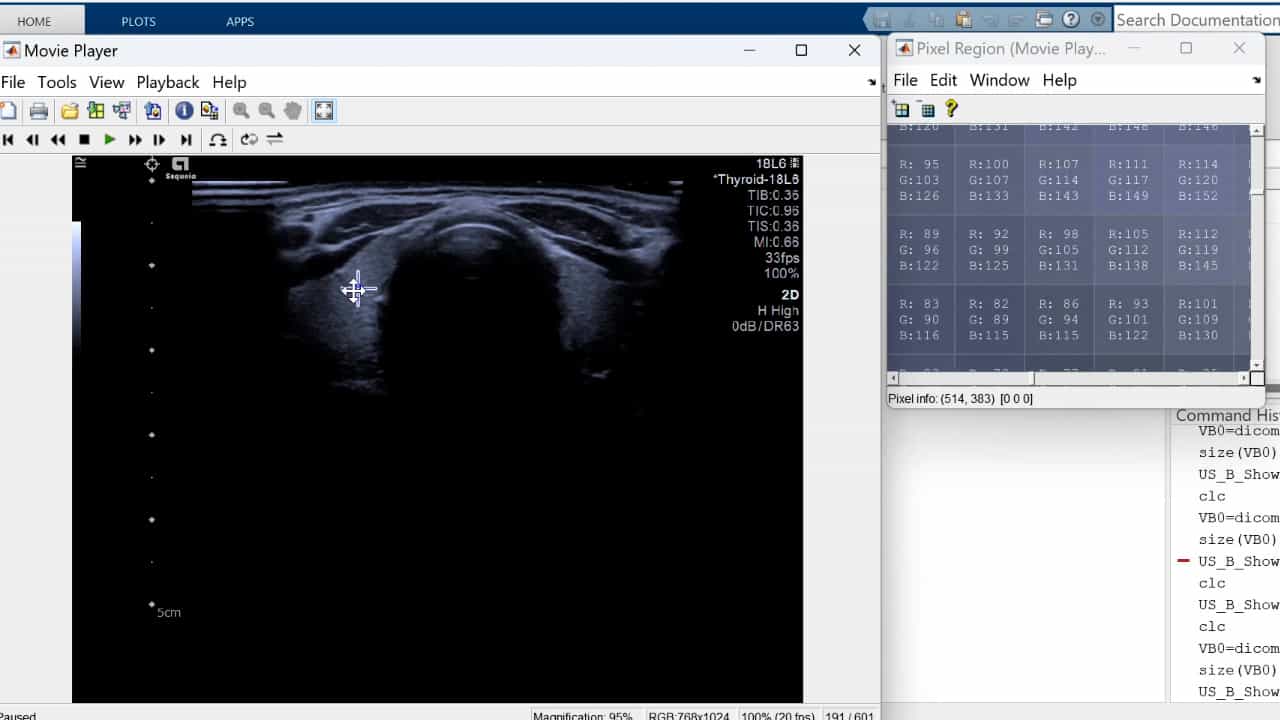

Author Spotlight: Integrating Ultrasound Imaging with Biochemical Markers for Thyroid Disease Diagnosis
Published on: February 9, 2024
Lessons learnt from a case of missed central hypothyroidism
Tessa Glyn1, Beverley Harris2, Kate Allen1
1Diabetes and Endocrinology.

Abstract:
We present the case of a 57-year-old lady who had a delayed diagnosis of central hypothyroidism on a background of Grave's thyrotoxicosis and a partial thyroidectomy. During the twenty years following her partial thyroidectomy, the patient developed a constellation of symptoms and new diagnoses, which were investigated by numerous specialists from various fields, namely rheumatology, renal and respiratory. She developed significantly impaired renal function and raised creatine kinase (CK). She was also referred to a tertiary neurology service for investigation of myositis, which resulted in inconclusive muscle biopsies. Recurrently normal TSH results reassured clinicians that this did not relate to previous thyroid dysfunction. In 2015, she developed increased shortness of breath and was found to have a significant pericardial effusion. The clinical biochemist reviewed this lady's blood results and elected to add on a free T4 (fT4) and free T3 (fT3), which were found to be <0.4 pmol/L (normal range (NR): 12-22 pmol/L) and 0.3 pmol/L (NR: 3.1-6.8 pmol/L), respectively. She was referred urgently to the endocrine services and commenced on Levothyroxine replacement for profound central hypothyroidism. Her other pituitary hormones and MRI were normal. In the following year, her eGFR and CK normalised, and her myositis symptoms, breathlessness and pericardial effusion resolved. One year following initiation of Levothyroxine, her fT4 and fT3 were in the normal range for the first time. This case highlights the pitfalls of relying purely on TSH for excluding hypothyroidism and the devastating effect the delay in diagnosis had upon this patient.
Learning Points:
Isolated central hypothyroidism is very rare, but should be considered irrespective of previous thyroid disorders.If clinicians have a strong suspicion that a patient may have hypothyroidism despite normal TSH, they should ensure they measure fT3 and fT4.Laboratories that do not perform fT3 and fT4 routinely should review advice sent to requesting clinicians to include a statement explaining that a normal TSH excludes primary but not secondary hypothyroidism.Thyroid function tests should be performed routinely in patients presenting with renal impairment or a raised CK.
Related Concept Videos
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:27
Major Hormones and Their Functions
Oxytocin, produced in the hypothalamus and released by the pituitary gland, plays a role in social bonding, childbirth, and...
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 00:59
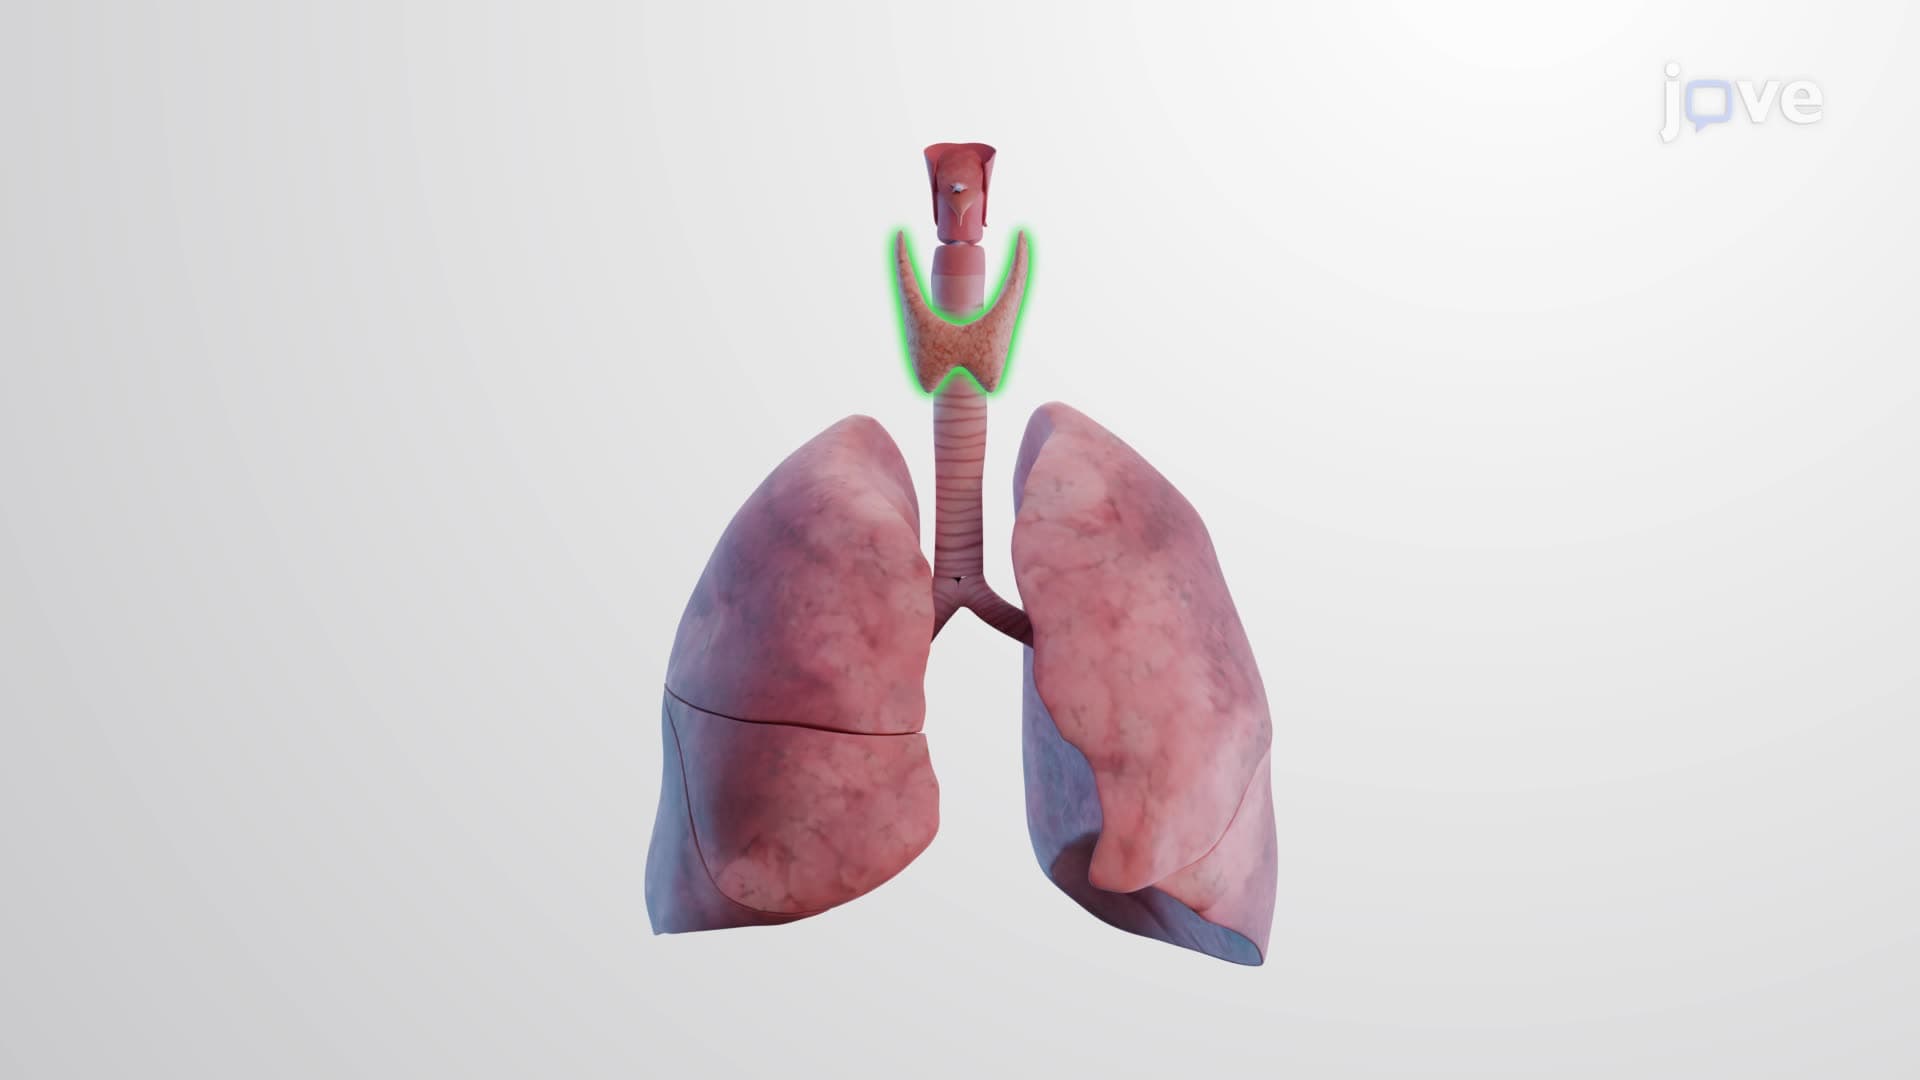
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by...