Related Experiment Video
Updated: Feb 17, 2026
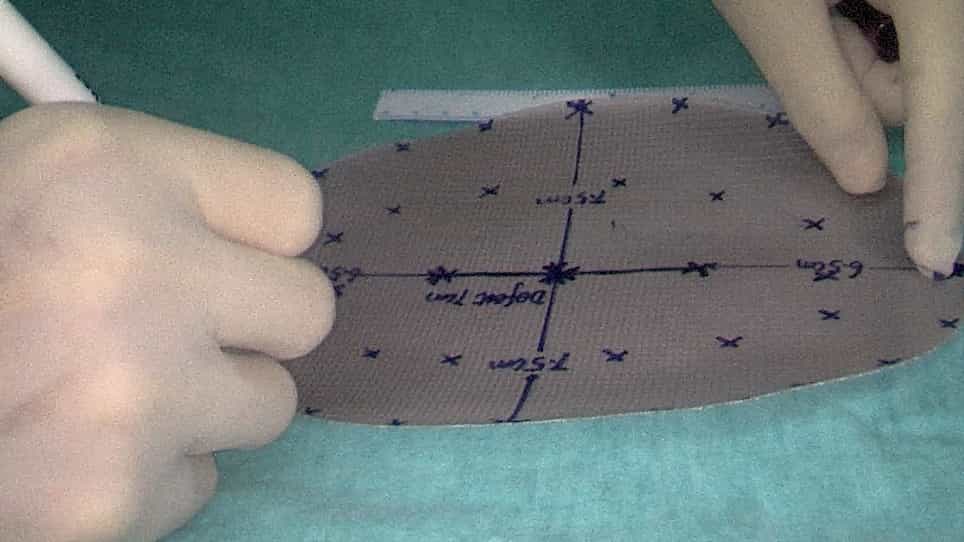
Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
Impact of incisional hernia development following abdominal operations on total healthcare cost
Vamsi V Alli1, Jianying Zhang2, Dana A Telem3
1Department of Surgery, Penn State Hershey Medical Center, 500 University Drive, M.C. H149, Hershey, PA, 17033, USA. valli@pennstatehealth.psu.edu.

Background:
Introduction of the category III CPT code (0437T) for prophylactic mesh augmentation (PMA) highlights efforts to reduce incisional hernia (IH). PMA's value in the context of value-based care requires understanding both the cost of IH development and the savings from prevention. We hypothesized large healthcare costs with IH development. Appreciating which subsets of patients are at highest risk for IH, and the subsets who have the costliest care is essential in targeting interventions for hernia prevention.
Methods:
Retrospective cohort study utilizing data from Truven Health Analytic MarketScan Commercial Claims and Encounters Database from calendar years 2011-2014. Adults undergoing open abdominal operations with continued enrollment 3-year post-surgery were included. Inpatient and outpatient claims were tracked over 3 years to identify IH. Quantile regression estimated the association between conditional distribution of total cost and IH. A generalized linear model with gamma distribution estimated the association of conditional mean of total cost and IH. Models were adjusted for confounding cost covariates (e.g., age, gender, obesity, smoking, cancer).
Results:
14,290 patients were identified, 1294 (9.1%) developed IH, 48% within 1-year, 33% at 1-2 years, and 19% at 2-3 years post-surgery. 515 underwent stoma creation, 4579 colon resection, 2263 liver/kidney, 3890 peritoneal, 3043 other (foregut, appendectomy, cholecystectomy). Rate of IH formation was 25, 13, 5.9, 6.3, and 6.3%, respectively. The difference in median expenditures for IH development versus no IH was ostomies: $26,098, colorectal: $21,211, liver/kidney: $23,811, peritoneal: $25,554, others: $28,870 (p < 0.0.01). IH within 1 year was more expensive than within 3 years in the following categories: colorectal ($16,034, p = 0.0385), liver/kidney ($27,145, p = 0.0004), and ostomy ($18,992, p = 0.0035).
Conclusion:
IH is a common occurrence imposing significant healthcare burden. Higher costs occur when IH occurs within 1 year versus 3 years from the index-procedure. This highlights the importance of hernia prevention techniques and the question of whether temporizing closure adjuncts are appropriate in high-risk patients.
More Related Videos

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:22
Aneurysm IV: Nursing Management
 01:26
Aneurysm III: Interprofessional Care