Related Experiment Video
Updated: Feb 17, 2026


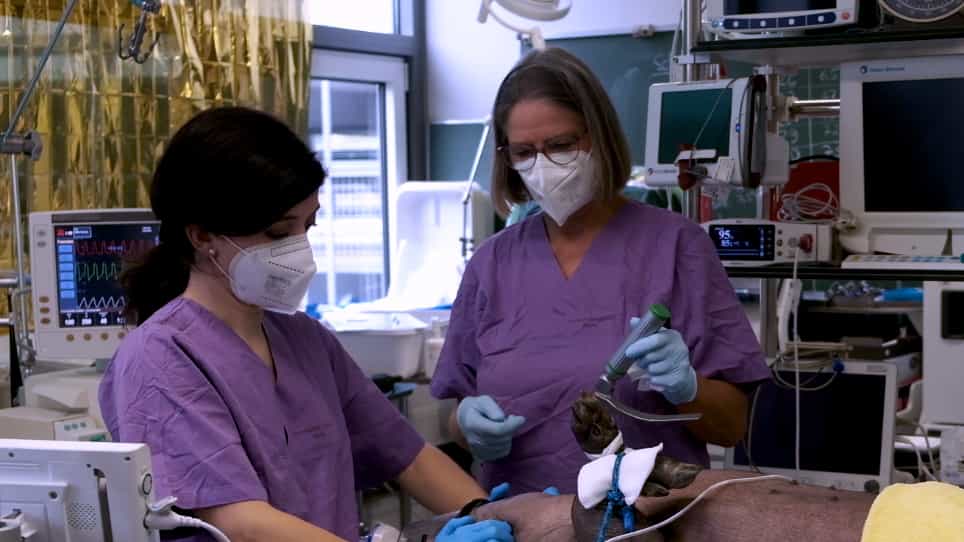
Author Spotlight: Advancing Awake Nasotracheal Intubation with Flexible Video Rhino-Laryngoscopes
Published on: August 2, 2024
Videolaryngoscopy for Physician-Based, Prehospital Emergency Intubation: A Prospective, Randomized, Multicenter
Erol Cavus1,2, Sebastian Janssen1, Florian Reifferscheid3
1From the Faculty of Medicine, Christian-Albrechts-University, Kiel, Germany.

Background:
Videolaryngoscopy is a valuable technique for endotracheal intubation. When used in the perioperative period, different videolaryngoscopes vary both in terms of technical use and intubation success rates. However, in the prehospital environment, the relative performance of different videolaryngoscopic systems is less well studied.
Methods:
We conducted this prospective, randomized, multicenter study at 4 German prehospital emergency medicine centers. One hundred sixty-eight adult patients requiring prehospital emergency intubation were treated by an emergency physician and randomized to 1 of 3 portable videolaryngoscopes (A.P. Advance, C-MAC PM, and channeled blade KingVision) with different blade types. The primary outcome variable was overall intubation success and secondary outcomes included first-attempt intubation success, glottis visualization, and difficulty with handling the devices. P values for pairwise comparisons are corrected by the Bonferroni method for 3 tests (P[BF]). All presented P values are adjusted for center.
Results:
Glottis visualization was comparable with all 3 devices. Overall intubation success for A.P. Advance, C-MAC, and KingVision was 96%, 97%, and 61%, respectively (overall: P < .001, A.P. Advance versus C-MAC: odds ratio [OR], 0.97, 95% confidence interval [CI], 0.13-7.42, P[BF] > 0.99; A.P. Advance versus KingVision: OR, 0.043, 95% CI, 0.0088-0.21, P[BF] < 0.001; C-MAC versus KingVision: OR, 0.043, 95% CI, 0.0088-0.21, P[BF] < 0.001). Intubation success on the first attempt with A.P. Advance, C-MAC, and KingVision was 86%, 85%, and 48%, respectively (overall: P < .001, A.P. Advance versus C-MAC: OR, 0.89, 95% CI, 0.31-2.53, P[BF] > 0.99; A.P. Advance versus KingVision: OR, 0.24, 95% CI, 0.055-0.38, P[BF] = 0.0054; C-MAC versus KingVision: OR, 0.21, 95% CI, 0.043-.34, P[BF] < 0.003). Direct laryngoscopy for successful intubation with the videolaryngoscopic device was necessary with the A.P. Advance in 5 patients, and with the C-MAC in 4 patients. In the KingVision group, 21 patients were intubated with an alternative device.
Conclusions:
During prehospital emergency endotracheal intubation performed by emergency physicians, success rates of 3 commercially available videolaryngoscopes A.P. Advance, C-MAC PM, and KingVision varied markedly. We also found that although any of the videolaryngoscopes provided an adequate view, actual intubation was more difficult with the channeled blade KingVision.

Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:23
Tracheostomy Suctioning II: Procedure