Related Experiment Video
Updated: Feb 16, 2026

Author Spotlight: An Economic and Efficient Method for Quantitative Evaluation of Bone Microarchitecture in a Murine Osteoporosis Model
Published on: September 8, 2023
The clinical-morphological profile of bone and joints tuberculosis - our experience in relation to literature data
Iancu Emil Pleşea1, Dan Nelu Anuşca, Iordan Procopie
1Department of Public Health and Management, University of Medicine and Pharmacy of Craiova, Romania; mghelase@ymail.com.

Aim:
The authors made a morphological assessment of musculoskeletal tissue samples from patients admitted in Surgical Departments of the Emergency County Hospital of Craiova, Romania, between 1990 and 2015, proved as presenting tuberculous lesions in the Department of Pathology of the same Hospital.
Materials And Methods:
The studied material consisted of bone, joint and sometimes muscle tissue fragments resulted from biopsies or surgical excisions from 54 cases coming out of 841 patients investigated in the above-mentioned period of time, where the established histological diagnosis was tuberculosis (TB). For diagnostic confirmation, Ziehl-Neelsen staining has been used as a rule but, in some cases, immunohistochemistry was also used.
Results:
TB lesions have prevailed in men and around the age of 50 despite the tissue involved (either bones or joints or both structures). Bone tissue, lower limb and right side of the body have been more frequently touched by the TB lesions. Axial bones (spine, ribs and hip bone) and knee joint have been the favorite sites. From morphological point of view, the inflammatory cellular population has been dominated by the epithelioid and giant Langhans cells that surrounded areas less or more extended of classical acidophilic fine granular necrosis. The fibrosis was observed more frequently around bone lesions, usually in an incipient phase. Overall, the granulomatous reaction was of reactive type but one should notice hyporeactive or areactive, disorganized reaction encountered quite often in bone or associated bone and joints lesions.
Conclusions:
Osteoarticular tuberculosis (OATB) has a complex and dynamic clinical morphological picture, which is still partly known, described and understood especially in the field of morphological changes. Further detailed and integrative analysis of both clinical and morphological aspects is required so the suspicion of diagnosis at the admission becomes as soon as possible certitude.

Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:18
Classification of Bones
Long and Short Bones
The appendicular skeleton, particularly the upper and lower limbs, is primarily made of long and short bones. The...
 01:17
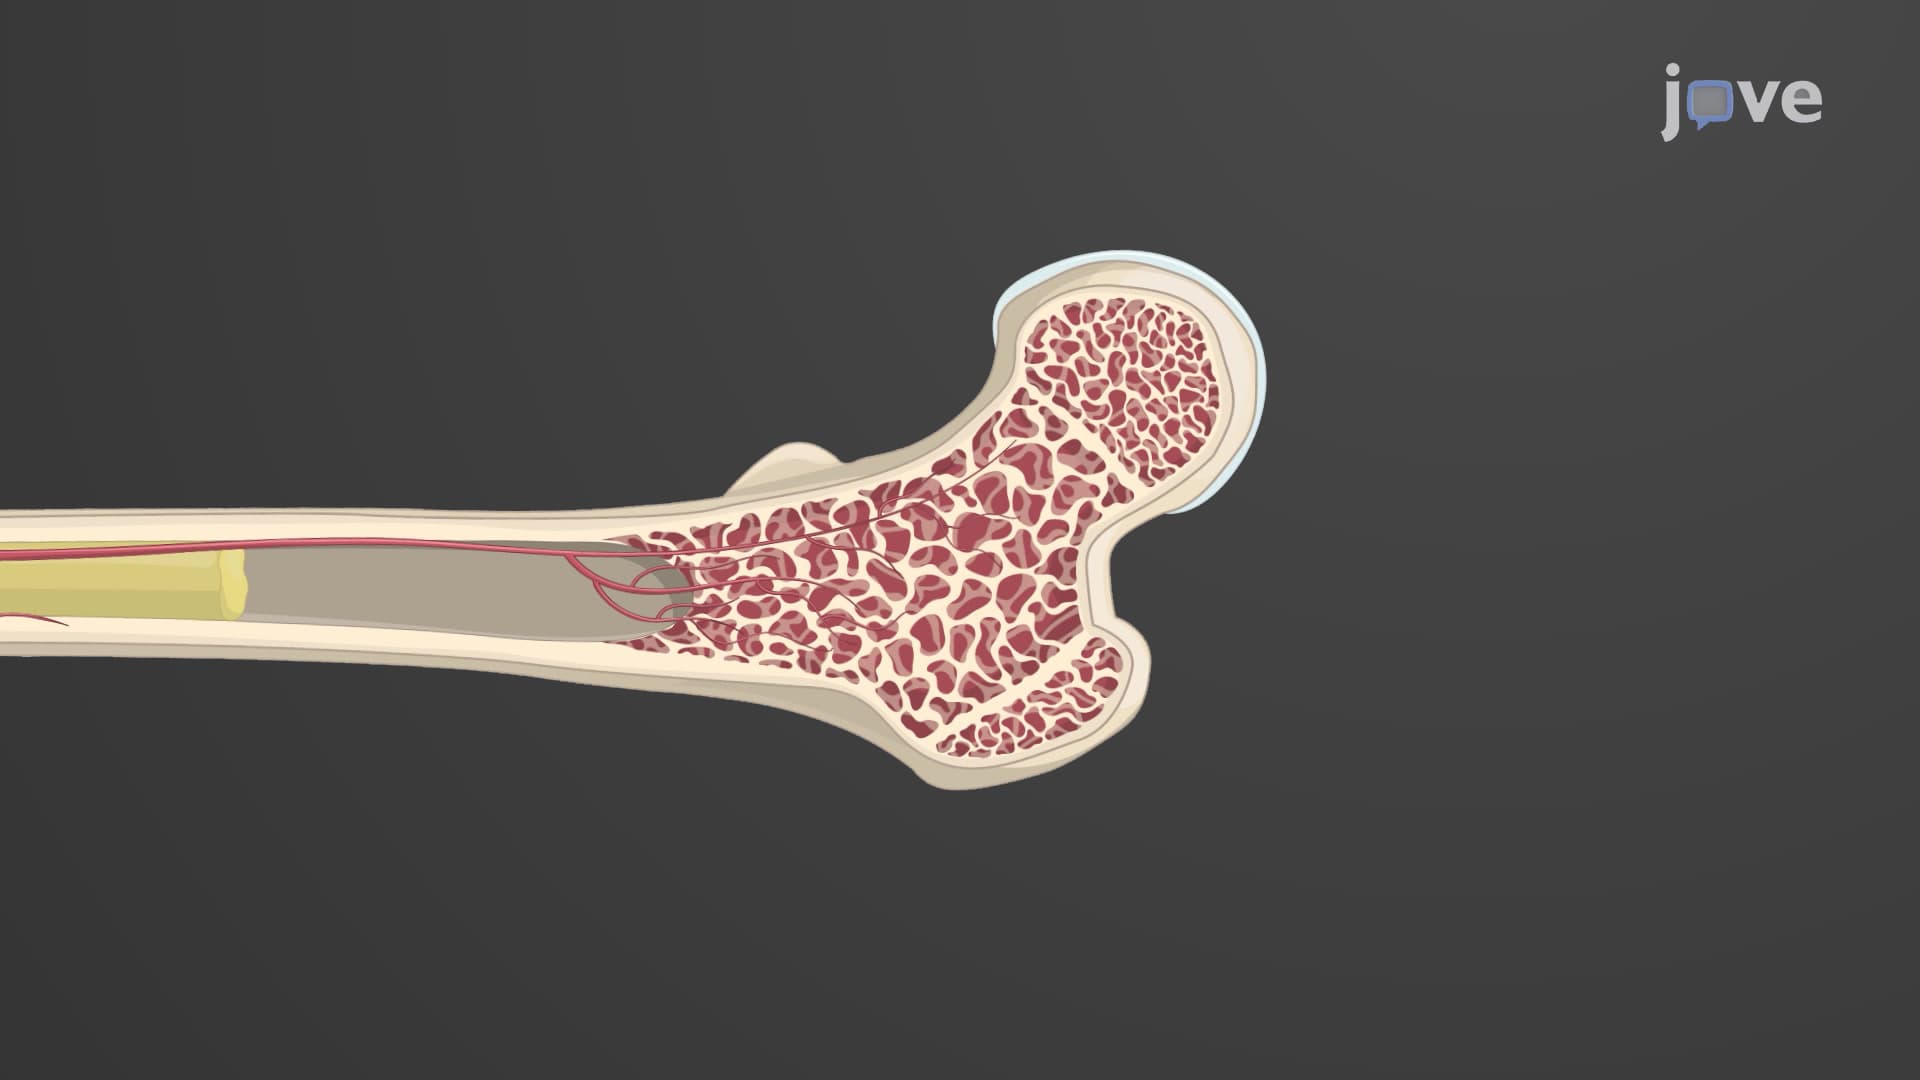
Gross Anatomy of Bone
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in...