Diagnostic Accuracy of Controlled Attenuation Parameter for Detecting Hepatic Steatosis in Patients with Chronic
Patrícia Andrade1, Susana Rodrigues1, Eduardo Rodrigues-Pinto1
1Department of Gastroenterology, Faculty of Medicine, Centro Hospitalar São João, University of Porto, Porto, Portugal.

Introduction:
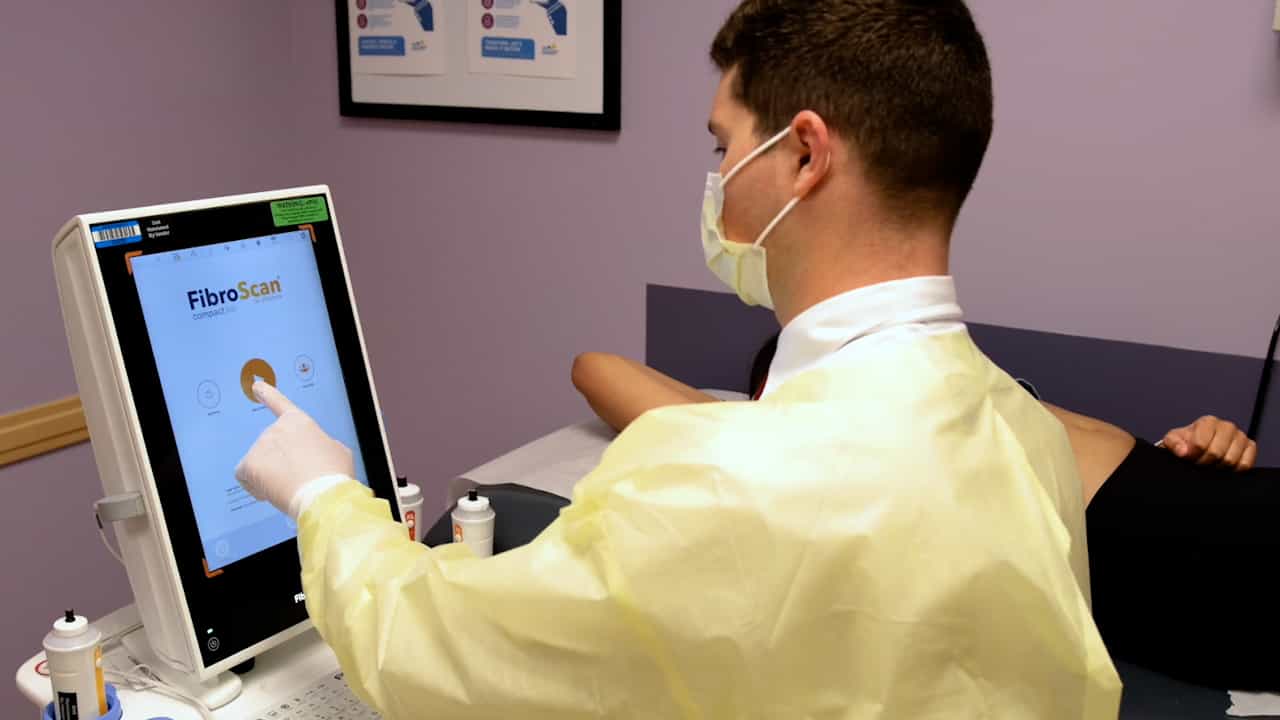
Controlled attenuation parameter (CAP), measured by transient elastography, has been suggested as a noninvasive method for the detection and quantification of steatosis. We aimed to assess the accuracy of CAP to detect steatosis in patients with chronic liver disease (CLD) compared with liver histology and to evaluate factors that correlate with the CAP value.
Methods:
Patients with CLD who underwent liver biopsy and simultaneous CAP determination were consecutively enrolled. CAP was measured using the M probe of FibroScan® (Echosens, Paris, France). Histologically, steatosis was categorized as absent (S0: <5%), mild (S1: 5-33%), moderate (S2: 34-66%) and severe (S3: >66% of all hepatocytes).
Results:
We analyzed 159 patients with CLD (61% men, mean age 47.9 ± 12.9 years). We found a positive correlation between CAP and steatosis in histology (rs = 0.869, p < 0.001), arterial hypertension (rs = 0.222, p = 0.005), type 2 diabetes mellitus (rs = 0.279, p < 0.001), body mass index (BMI; rs = 0.533, p < 0.001), total cholesterol (rs = 0.442, p < 0.001), triglycerides (rs = 0.272, p = 0.001), and non-alcoholic fatty liver disease (NAFLD; rs = 0.588, p < 0.001). In the multivariate analysis, BMI >25 (odds ratio [OR] 48.4, 95% confidence interval [CI] 23.78-72.95, p < 0.001), serum total cholesterol (OR 3.803, 95% CI 2.203-13.889, p = 0.008), and NAFLD etiology (OR 40.8, 95% CI 15.01-66.66, p = 0.002) were independently associated with higher CAP values. We did not find any significant correlation between CAP and the grade of necroinflammatory activity (rs = 0.063, p = 0.808) or fibrosis (rs = 0.071, p = 0.713) in histology and with alanine aminotransferase (rs = 0.190, p = 0.356) or aspartate aminotransferase (rs = 0.117, p = 0.142). Optimal CAP cutoff values for detecting steatosis ≥S1, ≥S2, and ≥S3 were 206.5, 232.5, and 282.5 dB/m, respectively. CAP performance was 0.822, 0.956, and 0.976 for diagnosing steatosis ≥S1, ≥S2, and ≥S3, respectively.
Conclusions:
CAP had an excellent diagnostic accuracy for the detection of steatosis in diverse CLD patients. A CAP value cutoff of <282.5 dB/m excludes severe steatosis ≥S3 with an accuracy of 98%.
More Related Videos
 08:41
Novel In Vivo Micro-Computed Tomography Imaging Techniques for Assessing the Progression of Non-Alcoholic Fatty Liver Disease
Published on: March 24, 2023
 07:12
Author Spotlight: Analysis of Fluorescent-Stained Lipid Droplets with 3D Reconstruction for Hepatic Steatosis Assessment
Published on: June 2, 2023
Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow