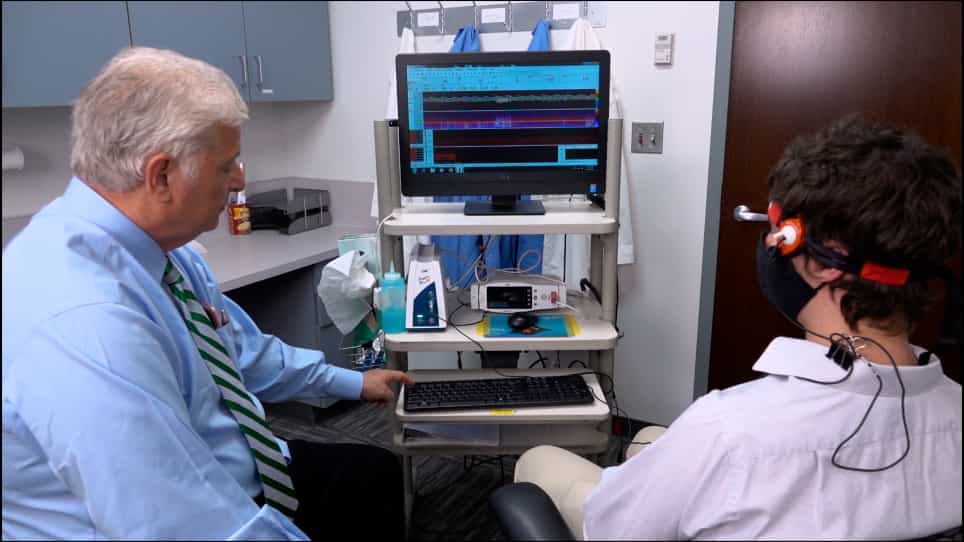
Related Experiment Video
Updated: Feb 16, 2026

Systems Analysis of the Neuroinflammatory and Hemodynamic Response to Traumatic Brain Injury
Published on: May 27, 2022
Relationships between cerebral flow velocities and neurodevelopmental outcomes in children with moderate to severe
Nicole Fortier O'Brien1, Tensing Maa2, Melissa Moore-Clingenpeel3
1Nationwide Children's Hospital, Division of Critical Care Medicine, The Ohio State University, 700 Children's Drive, Columbus, OH, 43205, USA. nicole.obrien@nationwidechildrens.org.

Insights
Cerebral blood flow velocity (CBFV) in children with traumatic brain injury (TBI) can predict neurodevelopmental outcomes. Low CBFV indicates poor outcomes, while normal CBFV is linked to better results, suggesting CBFV as a prognostic tool.
Area of Science:
- Pediatric neurology
- Neurocritical care
- Neurodevelopmental outcomes
Background:
- Traumatic brain injury (TBI) in children can lead to significant neurodevelopmental deficits.
- Assessing cerebral blood flow velocity (CBFV) may offer insights into TBI severity and prognosis.
Purpose of the Study:
- To investigate the relationship between cerebral blood flow velocity (CBFV) and neurodevelopmental outcomes in pediatric patients with moderate to severe TBI.
- To determine if CBFV can serve as an early prognostic indicator in children following TBI.
Main Methods:
- Prospective enrollment of children with TBI (Glasgow Coma Score 8-12) and abnormal brain imaging.
- Daily assessment of CBFV within the first 8 days post-trauma.
- Neurodevelopmental testing performed 12 months post-injury using the Pediatric Glasgow Outcome Scale (GOS-E Peds).
Main Results:
- Sixty-nine patients were analyzed. Low CBFV (<2 SD below normal) was observed in 6% and uniformly associated with poor neurologic outcomes (GOS-E Peds ≤4).
- Normal CBFV (±2 SD from normal) was found in 43% of participants.
- High CBFV and vasospasm were identified in 23% and 28% of children, respectively. Children with good outcomes were more likely to exhibit normal CBFV patterns.
Conclusions:
- CBFV alterations in pediatric TBI are heterogeneous, but low flow consistently predicts poor outcomes.
- Normal CBFV patterns correlate with better neurodevelopmental outcomes, suggesting its utility as a prognostic marker.
- Further research is warranted to explore aberrant CBFV as a potential therapeutic target in TBI management.
Purpose:
This study aimed to determine relationships between cerebral blood flow and neurodevelopmental outcomes in children with moderate to severe traumatic brain injury (TBI).
Methods:
Children with TBI, a Glasgow Coma Score of 8-12, and abnormal brain imaging were enrolled prospectively. Cerebral blood flow velocity (CBFV) was assessed within 24 h of trauma and daily thereafter through death, discharge, or hospital day 8, whichever came first. Twelve months from injury, participants completed neurodevelopmental testing.
Results:
Sixty-nine patients were enrolled. Low flow velocities (< 2 SD below age/gender normal) were found in 6% (n = 4). No patient with a single low CBFV measurement had a good neurologic outcome (Pediatric Glasgow Outcome Scale (GOS-E Peds) ≤ 4)). Normal flow velocities (± 2 SD around age/gender normal) were seen in 43% of participants (n = 30). High flow velocities (> 2 SD above age and gender normal with a Lindegaard ratio (LR) < 3) were identified in 23% of children (n = 16), and vasospasm (> 2 SD above age/gender normal with LR ≥ 3) was identified in 28% (n = 19). Children with good outcomes based on GOS-E Peds scoring were more likely to have had normal flow velocity than other flow patterns. No other differences in neurodevelopmental outcomes were noted.
Conclusions:
Individual patient responses to TBI in terms of CBFV alterations were heterogeneous. Low flow was uniformly associated with a poor outcome. Patients with good outcomes were more likely to have normal flow. This suggests CBFV may serve as a prognostic indicator in children with TBI. Future studies are needed to determine if aberrant CBFVs are also a therapeutic target.