Related Experiment Video
Updated: Feb 16, 2026
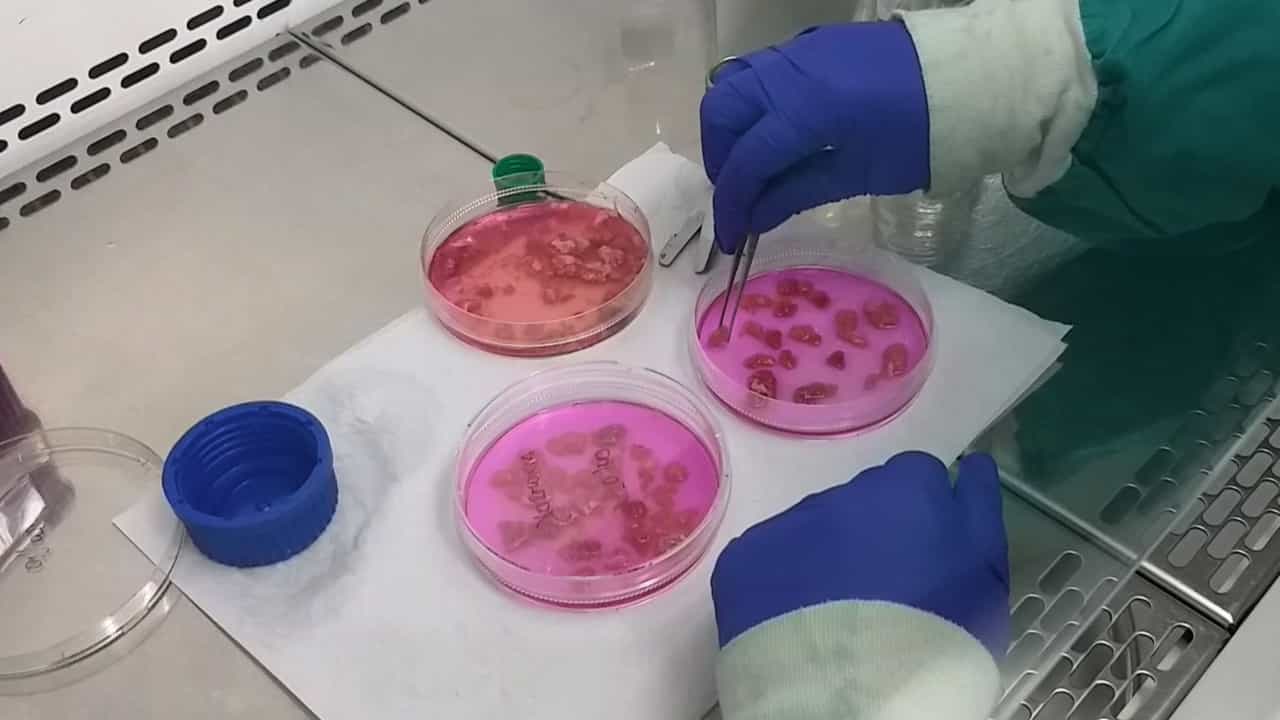

Author Spotlight: Modeling an Aspect of Preeclampsia in Female Mice Using Hypoxic Human Placenta-Derived Small Extracellular Vesicles
Published on: January 26, 2024
Maternal blood-pressure trends throughout pregnancy and development of pre-eclampsia in women receiving
A A Baschat1, D Dewberry1, V Seravalli1
1Center for Fetal Therapy, Department of Gynecology & Obstetrics, Johns Hopkins School of Medicine, Baltimore, MD, USA.

Objectives:
To study women who initiated aspirin in the first trimester for high risk of pre-eclampsia, and compare blood-pressure trends throughout pregnancy between those with normal outcome and those who subsequently developed pre-eclampsia.
Methods:
Women were enrolled into a prospective observational study at 9-14 weeks' gestation. This was a secondary analysis of those who started daily doses of 81 mg of aspirin before 16 weeks for increased risk of pre-eclampsia based on maternal history and bilateral uterine artery notching. Enrollment characteristics and blood-pressure measurements throughout gestation were compared between women who did and those who did not develop pre-eclampsia.
Results:
Of the 237 women who initiated first-trimester aspirin prophylaxis, 29 (12.2%) developed pre-eclampsia. A total of 2881 serial blood-pressure measurements obtained between 4 and 41 weeks' gestation (747 in the first trimester, 1008 in the second and 1126 in the third) showed that women with pre-eclampsia started pregnancy with higher blood pressure and maintained this trend despite taking aspirin (mean arterial blood pressure in women with pre-eclampsia = (0.13 × gestational age (weeks)) + 93.63, vs (0.11 × gestational age (weeks)) + 82.61 in those without; P < 0.005). First-trimester diastolic and second-trimester systolic blood pressure were independent risk factors for pre-eclampsia (β = 1.087 and 1.050, respectively; r2 = 0.24, P < 0.0001). When average first-trimester diastolic blood pressure was >74 mmHg, the odds ratio for pre-eclampsia was 6.5 (95% CI, 2.8-15.1; P < 0.001) and that for pre-eclampsia before 34 weeks was 14.6 (95% CI, 1.72-123.5; P = 0.004). If, in addition, average second-trimester systolic blood pressure was >125 mmHg, the odds ratio for pre-eclampsia was 9.4 (95% CI, 4.1-22.4; P < 0.001) and that for early-onset disease was 34.6 (95% CI, 4.1-296.4; P = 0.004).
Conclusion:
In women treated with prophylactic aspirin from the first trimester, those who develop pre-eclampsia have significantly and sustained higher blood pressure from the onset of pregnancy compared with those who do not develop pre-eclampsia. This raises the possibility that mildly elevated blood pressure predisposes women to abnormal placentation, which then acts synergistically with elevated blood pressure to predispose such women to pre-eclampsia to a degree that is incompletely mitigated by aspirin. Copyright © 2017 ISUOG. Published by John Wiley & Sons Ltd.
Related Concept Videos
 01:33
Hormonal Regulation
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:17
Measurement of Blood Pressure
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.