Related Experiment Video
Updated: Feb 16, 2026

A Novel Vertebral Stabilization Method for Producing Contusive Spinal Cord Injury
Published on: January 5, 2015
Instrumented Spinal Stabilization without Fusion for Spinal Metastatic Disease
Dori Drakhshandeh1, James A Miller2, Andrew J Fabiano2
1Department of Neurosurgery, Roswell Park Cancer Institute, Buffalo, New York, USA.

Objectives:
Spinal stabilization surgery is an integral part of the treatment of spinal metastatic disease. Bony fusion is the hallmark of spinal stabilization in non-oncology patients. Spinal oncology patients are unlikely to achieve bony fusion because of their overall prognosis and concurrent therapies. Stabilization surgery without fusion may be a reasonable approach for these patients. Literature evaluating the effectiveness of this approach is limited. The object of this study was to investigate the rate of instrumentation failure in patients undergoing posterior spinal instrumented stabilization without fusion for spinal metastatic disease.
Methods:
Data from consecutive cases of spinal surgery at our institution during an 81-month period were reviewed. Demographics, clinical notes, and computed tomography findings were recorded and used to evaluate instrumentation failures. Patients who underwent separation surgery that included laminectomy and posterior spinal instrumentation without fusion for spinal metastatic disease and had follow-up computed tomography scans >3 months postoperatively were selected for the study.
Results:
Twenty-seven patients were included in the study. Mean age was 64.85 ± 6.53 years. Nine patients were women. A mean of 1.61 ± 0.96 laminectomy levels was performed. A mean of 8.26 ± 1.48 screws was inserted. The mean postoperative discharge date was 5.07 ± 1.47 days. Mean follow-up duration was 12.17 ± 11.73 months. None of the patients had a change in instrumentation position, pedicle screw pullout, change in spinal alignment, or progressive deformity. No patient required reoperation or instrumentation revision or replacement.
Conclusions:
Our experience suggests that instrumented spinal stabilization without fusion is an acceptable approach for patients with spinal metastatic disease.

Related Concept Videos
 01:26
Spinal Cord
 01:54
The Spinal Cord
 01:10
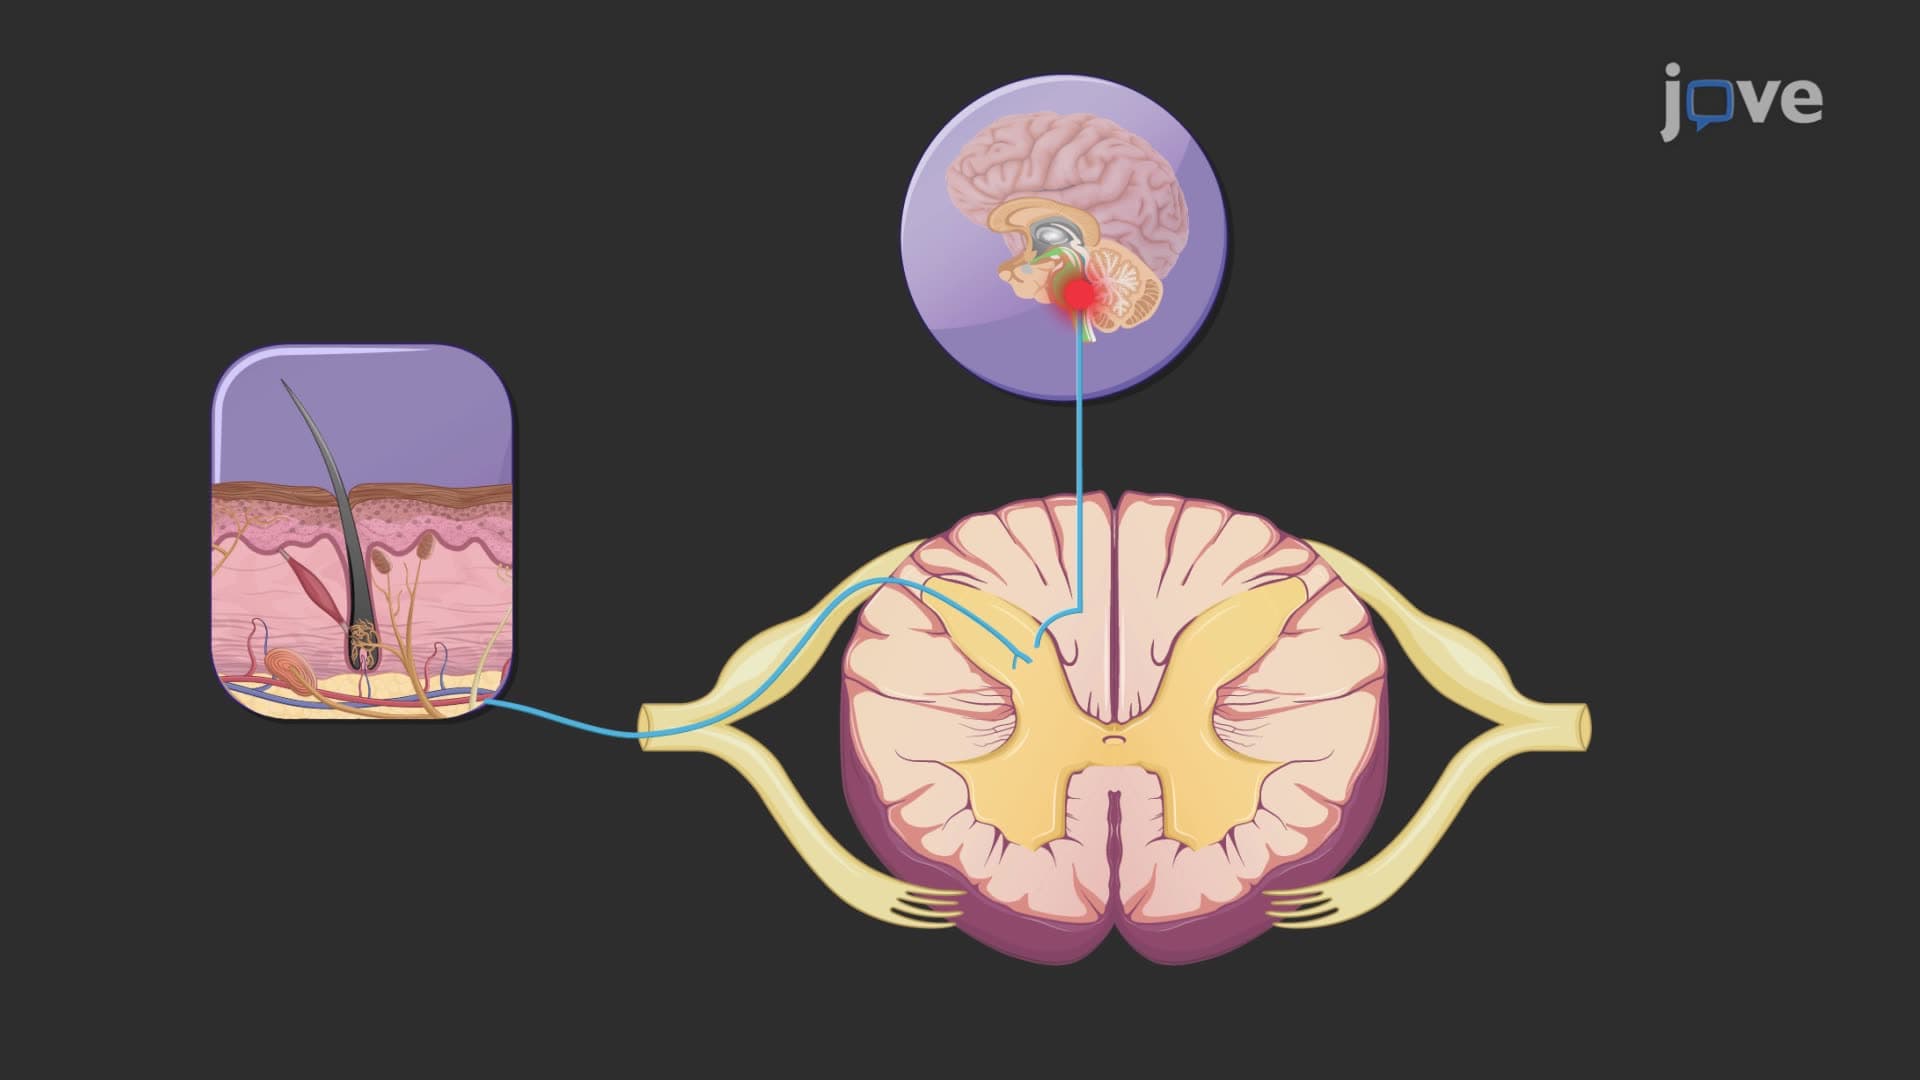
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:23
Spinal Nerves: Anatomy
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...