Related Experiment Video
Updated: Feb 16, 2026
Author Spotlight: Minimally Invasive Ultrasound-Guided Acupotomy in Knee Osteoarthritis Treatment
Published on: April 26, 2024
Does additional patella tendon shortening influence the effects of multilevel surgery to correct flexed knee gait in
M C M Klotz1, Britta K Krautwurst1, K Hirsch1
1Clinic for Orthopedics and Trauma Surgery, Heidelberg University Hospital, Heidelberg, Germany.

Insights
Patellar tendon shortening (PTS) effectively corrects flexed knee gait in children with cerebral palsy (CP) when combined with single event multilevel surgery (SEMLS). However, this intervention may increase anterior pelvic tilt and lead to a stiff knee gait.
Area of Science:
- Orthopedic surgery
- Pediatric rehabilitation
- Gait analysis
Background:
- Flexed knee gait is a common challenge in children with cerebral palsy (CP).
- Single Event Multilevel Surgery (SEMLS) is a surgical approach to address gait abnormalities.
- The role of Patellar Tendon Shortening (PTS) as an adjunct to SEMLS for improving knee extension requires further investigation.
Purpose of the Study:
- To evaluate the efficacy of Patellar Tendon Shortening (PTS) as part of SEMLS in reducing flexed knee gait in children with CP.
- To determine if PTS, when combined with SEMLS, leads to a stiff knee gait.
- To assess the impact of PTS on knee extension and other clinical parameters post-surgery.
Main Methods:
- A randomized controlled study involving 22 children with CP and flexed knee gait (GMFCS Level I-III).
- Participants were allocated to two groups: SEMLS with PTS and SEMLS without PTS.
- Kinematic data (3-D motion analysis) and clinical assessments were compared before and after surgery (12.7 ± 1.6 months follow-up).
Main Results:
- Both groups showed significant improvement in maximum knee extension post-SEMLS.
- The SEMLS + PTS group demonstrated significantly greater correction in knee extension (37.6° to 11.4°) compared to SEMLS alone (35.1° to 21.8°).
- The SEMLS + PTS group also showed a significant decrease in peak knee flexion and improvements in knee flexion contracture and popliteal angle, with a trend towards increased anterior pelvic tilt.
Conclusions:
- Patellar tendon shortening (PTS) is effective in correcting flexed knee gait and knee flexion contracture, leading to improved stance phase knee extension in children with CP.
- While beneficial for knee extension, the addition of PTS to SEMLS may result in a stiff knee gait.
- An increased anterior pelvic tilt was observed following surgery in both groups, with a trend towards a higher increase in the PTS group.
Background:
The aims of this study were to investigate if patellar tendon shortening (PTS) as a part of SEMLS (single event multilevel surgery) is effective for reduction of flexed knee gait in children with cerebral palsy (CP) and, if PTS leads to stiff knee gait.
Methods:
In a randomized controlled study 22 children with flexed knee gait (age: 10.4 ± 2.6 years, GMFCS Level I-III) were randomized and allocated to two groups (1: SEMLS + PTS; 2: SEMLS no PTS): SEMLS was performed for correction of flexed knee gait either with or without additional PTS. Before and after surgery (follow up: 12.7 ± 1.6 months) kinematics (3-D motion analysis) and clinical parameters were compared.
Results:
Two children were lost to follow up. Maximum knee extension improved significantly in both groups after SEMLS while the patients with additional PTS showed much more correction (SEMLS + PTS: 37.6° to 11.4°, p = 0.007; SEMLS no PTS: 35.1° to 21.8°, p = 0.016). After surgery peak knee flexion decreased significantly (14.6°, p = 0.004) in the "SEMLS + PTS" group while there was no relevant change in the other group. There was a trend of increase in anterior pelvic tilt after surgery in both groups, but no statistical significant difference. After surgery knee flexion contracture (15.9°, p < 0.001) and popliteal angle (27.2, p = 0.009) measured on clinical examination only decreased significantly in the "SEMLS + PTS" group.
Conclusion:
PTS is effective for correction of flexed knee gait and knee flexion contracture leading to superior stance phase knee extension. However, additional PTS may lead to stiff knee gait and a higher increase of anterior pelvic tilt.
More Related Videos

Related Concept Videos
 01:16
Bones of the Lower Limb: Femur and Patella
 01:15
Distance Corrections
 01:27
Conjugate Addition (1,4-Addition) vs Direct Addition (1,2-Addition)
Conjugate addition results in a thermodynamically stable product. The reaction retains the stronger C=O bond at the expense of the weaker C=C π bond. The process is slow as the β carbon is less electrophilic than the carbonyl carbon.
Direct addition products are...
 01:23
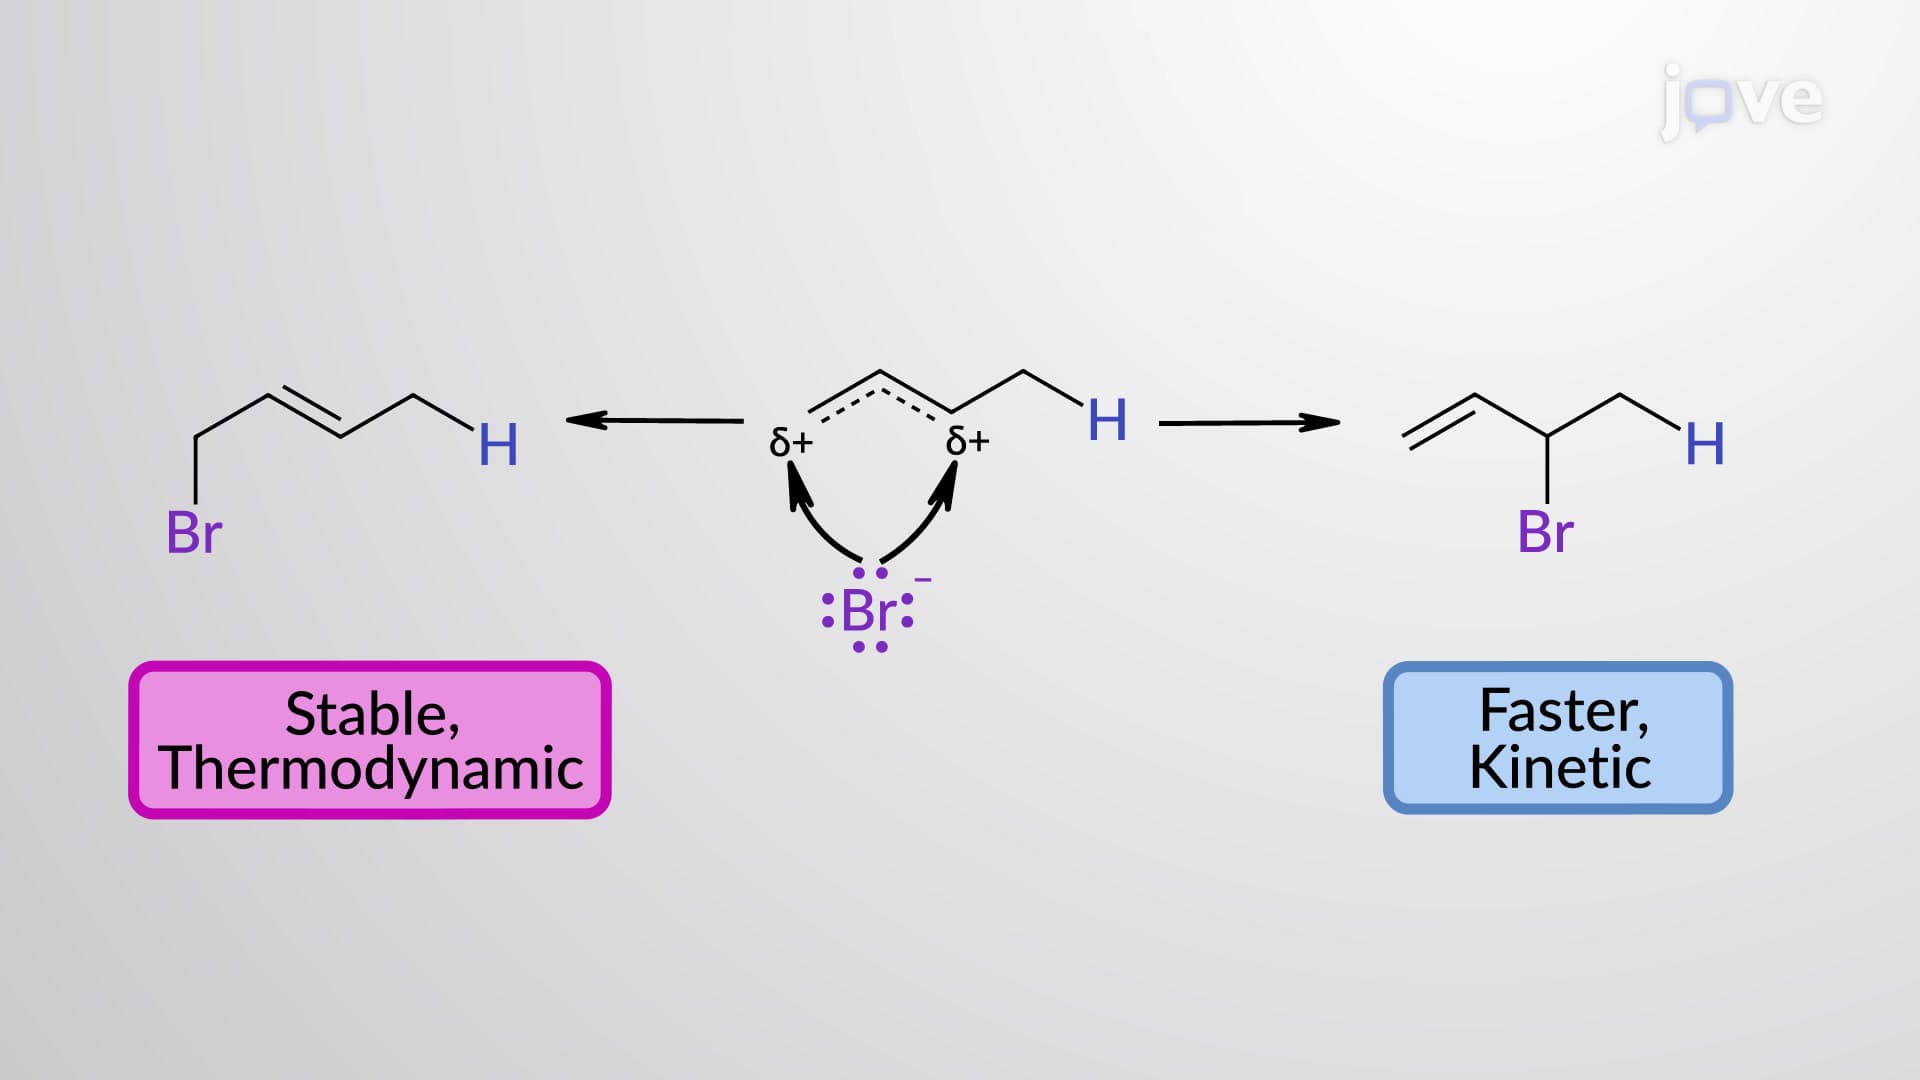
Electrophilic Addition of HX to 1,3-Butadiene: Thermodynamic vs Kinetic Control
 01:20
Power Factor Correction
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...