Related Experiment Video
Updated: Feb 16, 2026


Microinjectrode System for Combined Drug Infusion and Electrophysiology
Published on: November 13, 2019
Prolonged Dexmedetomidine Infusion and Drug Withdrawal In Critically Ill Children
Astrid S Haenecour1, Winnie Seto1, Charline M Urbain1
1Department of Critical Care Medicine (ASH, WS, PCL, CRB), The Hospital for Sick Children, Toronto, Canada; Department of Pharmacy (WS), The Hospital for Sick Children, Toronto, Canada; Department of Diagnostic Imaging and Neuroscience & Mental Health Program (CMU), The Hospital for Sick Children Research Institute, Toronto, Canada; Department of Clinical research services (DS), The Hospital for Sick Children, Toronto, Canada; and University of Toronto (DRB, PCL, WS), Toronto, Ontario, Canada.

Insights
Prolonged dexmedetomidine infusions in critically ill children can lead to withdrawal symptoms in 35% of cases. Higher cumulative doses and longer opioid use increase withdrawal risk, suggesting a need for weaning protocols.
Area of Science:
- Pediatric Critical Care Medicine
- Pharmacology
- Clinical Toxicology
Background:
- Dexmedetomidine is commonly used for sedation in pediatric intensive care units.
- Prolonged use may be associated with withdrawal syndromes.
- Limited data exists on withdrawal characteristics in pediatric populations.
Purpose of the Study:
- To determine the incidence, symptoms, and risk factors for dexmedetomidine withdrawal in critically ill children.
- To identify thresholds for cumulative dexmedetomidine dose associated with withdrawal.
Main Methods:
- Retrospective chart review of pediatric patients receiving dexmedetomidine for over 48 hours.
- Analysis of patient demographics, infusion details, and withdrawal symptoms.
- Statistical analysis to identify risk factors for withdrawal.
Main Results:
- Withdrawal occurred in 35% of 68 dexmedetomidine treatment courses.
- Common symptoms included agitation, fever, vomiting, and decreased sleep.
- Cumulative dexmedetomidine dose >107 mcg/kg and duration of opioid use were significant risk factors.
- Clonidine did not prevent withdrawal.
Conclusions:
- Withdrawal syndrome is a potential complication of prolonged dexmedetomidine infusion in children.
- Cumulative dose and concurrent opioid use are key factors influencing withdrawal.
- Development of a standardized weaning protocol is recommended.
Objective:
To characterise the incidence, symptoms and risk factors for withdrawal associated with prolonged dexmedetomidine infusion in paediatric critically ill patients.
Methods:
Retrospective chart review in the paediatric intensive care unit and the cardiac critical care unit of a single tertiary children's hospital. Patients up to 18 years old, who received dexmedetomidine for longer than 48 hours were included.
Results:
A total of 52 patients accounted for 68 unique dexmedetomidine treatment courses of more than 48 hours. We identified 24 separate episodes of withdrawal in the 68 dexmedetomidine courses (incidence 35%). Of these episodes 38% occurred in patients who were weaned from dexmedetomidine alone while the remaining occurred in patients who had concurrent weans of opioids and/or benzodiazepines. Most common symptoms were agitation, fever, vomiting/retching, loose stools and decreased sleep. The symptoms occurred during the latter part of the wean or after discontinuation of dexmedetomidine. A cumulative dose of dexmedetomidine of 107 mcg/kg prior to initiation of wean was more likely associated with withdrawal (this equates to a dexmedetomidine infusion running at 1 mcg/kg/hr over 4 days). Duration of opioid use was an additional risk factor for withdrawal. The use of clonidine, as a transition from dexmedetomidine, did not protect against withdrawal (p = 1).
Conclusions:
A withdrawal syndrome may occur after prolonged infusion of dexmedetomidine. As all our patients were also exposed to opioids this may be affected by the duration of opioid use. We identified a cumulative dose of 107 micrograms/kg of dexmedetomidine beyond which withdrawal symptoms were more likely (which equates to 4 days of use at a dose of 1 mcg/kg/hr). A protocol for weaning should be considered in this circumstance.
More Related Videos


Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:28
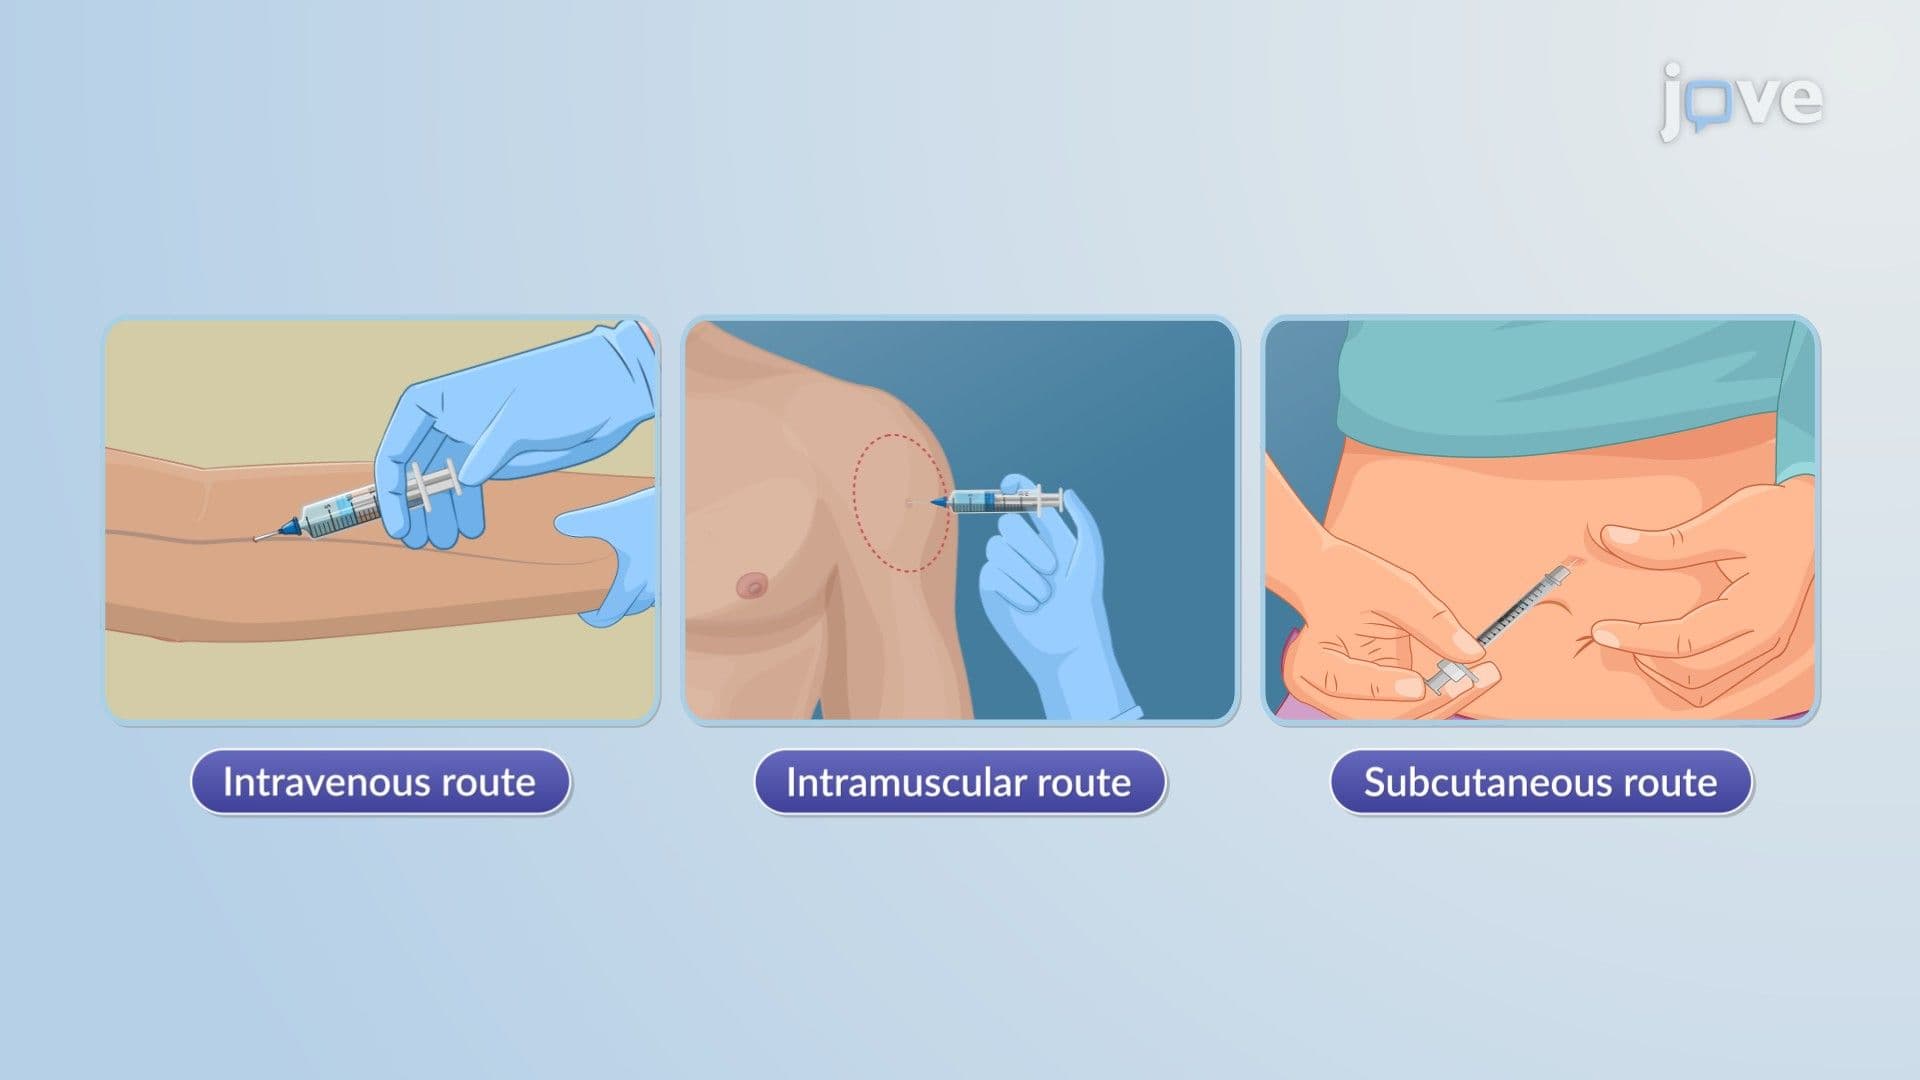
Parenteral Drug Delivery Systems: Injectables, Implants, and Infusion Devices
 01:16
Critical Region, Critical Values and Significance Level
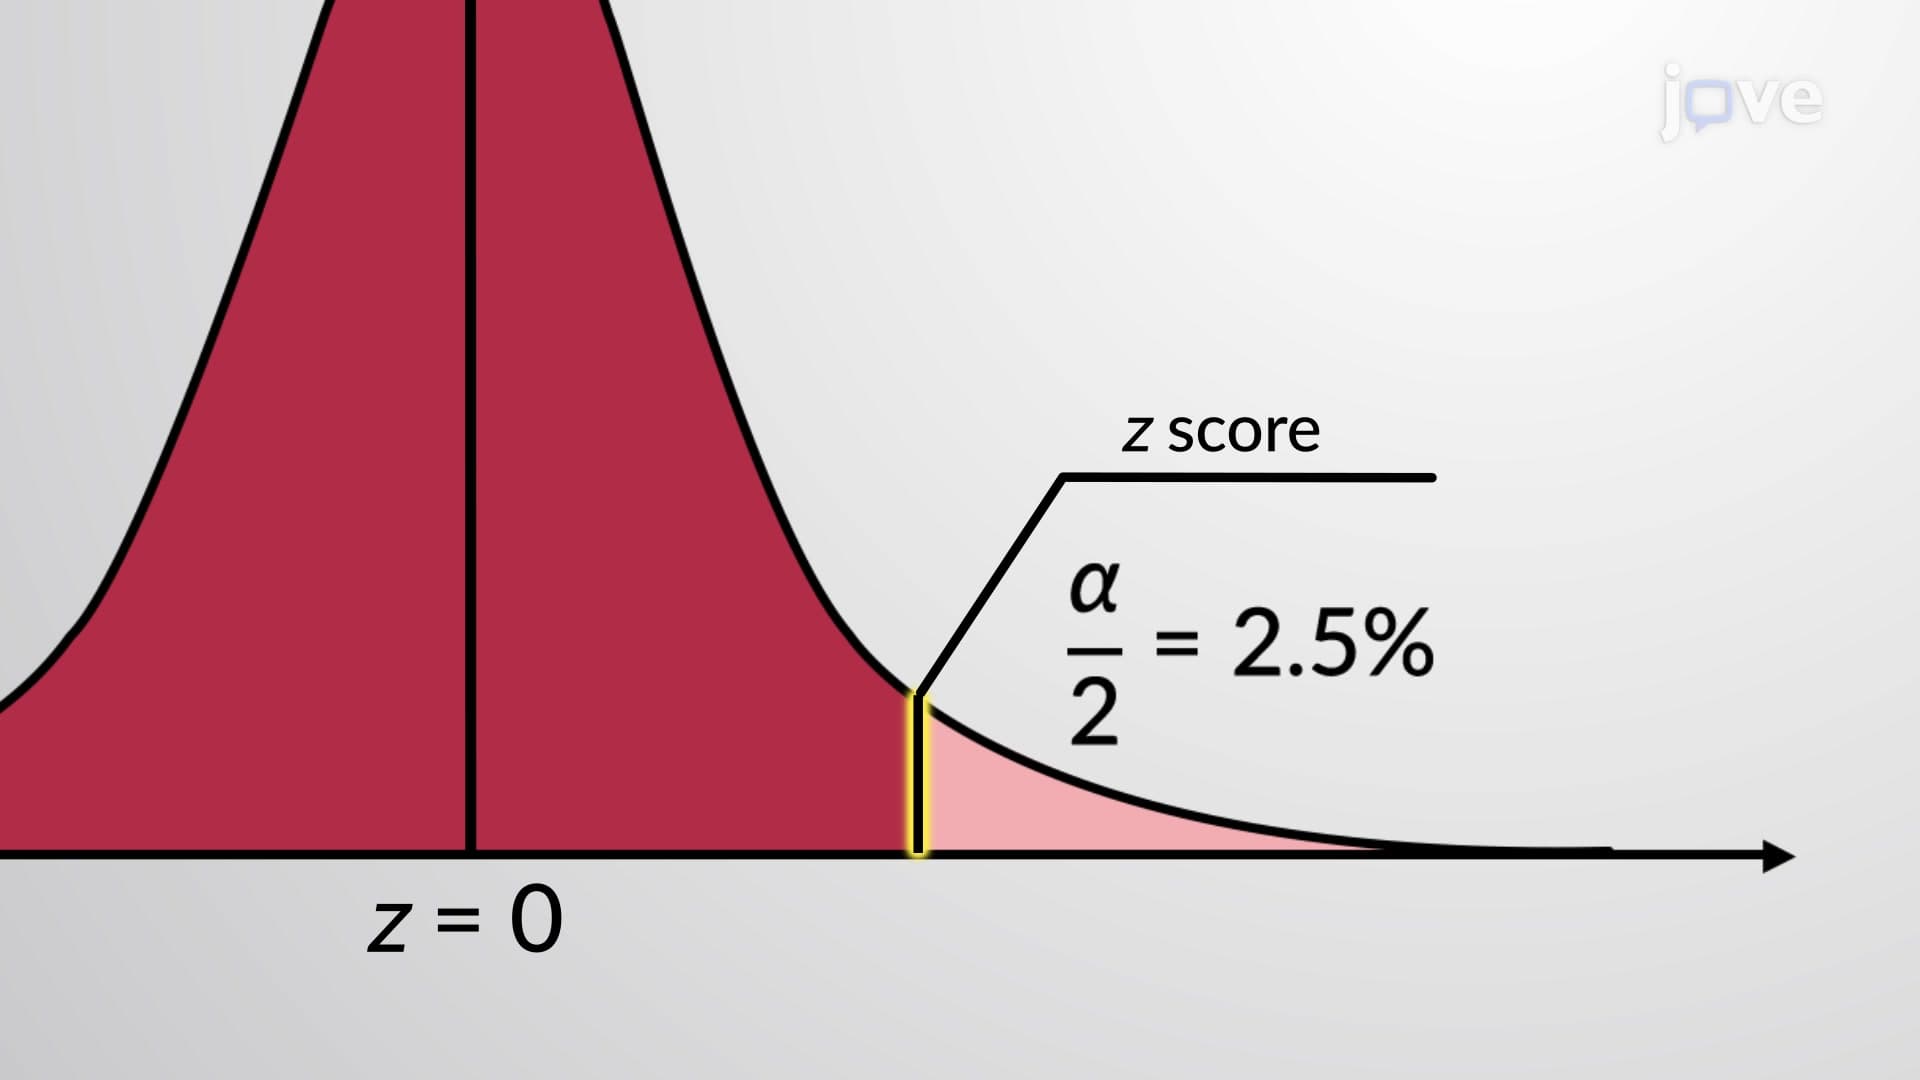
In hypothesis testing, a sample statistic is converted to a test statistic using z, t, or chi-square distribution. A critical region is an area under the curve in probability distributions demarcated by the critical value. When the test statistic falls in this region, it suggests that the null hypothesis must be rejected. As this region contains all those values of the...
 01:31
Critical Values
 01:19
Critical Thinking
Colleges and universities are...