Related Experiment Video
Updated: Feb 16, 2026

Fluorescent Laparoscopic Central Hepatectomy for Liver Cancer Using Indocyanine Green Negative Staining
Published on: March 17, 2023
Laparoscopic vs open complete mesocolic excision with central vascular ligation for colon cancer: A systematic review
Ionut Negoi1, Sorin Hostiuc2, Ruxandra Irina Negoi3
1Department of General Surgery, Emergency Hospital of Bucharest, Carol Davila University of Medicine and Pharmacy Bucharest, Bucharest 014461, Romania. negoiionut@gmail.com.

Aim:
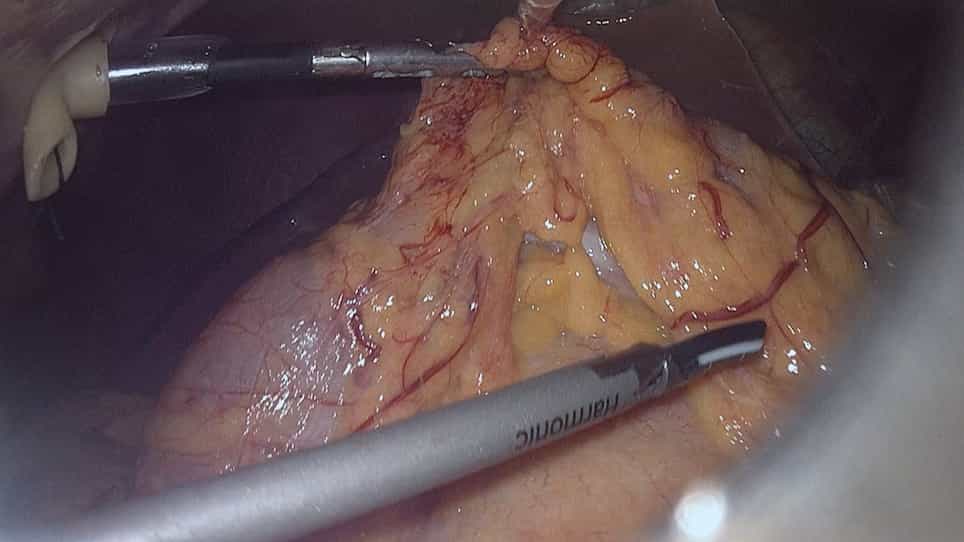
To compare the effectiveness of laparoscopic complete mesocolic excision (CME) with central vascular ligation (L-CME) with its open (O-CME) counterpart.
Methods:
We conducted an electronic search of the PubMed/MEDLINE, Excerpta Medica Database, Web of Science Core Collection, Cochrane Center Register of Controlled Trails, Cochrane Database of Systematic Reviews, SciELO, and Korean Journal databases from their inception until May 2017. We considered randomized controlled trials (RCTs) and controlled clinical trials (CCTs) that included patients with colonic cancer comparing L-CME and O-CME. Primary outcomes included the quality of the resected specimen (lymph nodes retrieved, complete mesocolic plane excision, tumor to arterial high tie, resected mesocolon surface). Secondary outcomes included the three-year and five-year overall and disease-free survival rates, recurrence of the disease, surgical data, and postoperative morbidity and mortality. Two authors of the review screened the methodological quality of the eligible trials and independently extracted data from individual studies.
Results:
A total of one RCT and eleven CCTs (four from Europe and seven from Asia) met the inclusion criteria for the current meta-analysis. These studies involved 1619 patients in L-CME and 1477 patients in O-CME. The L-CME was associated with the same quality of the resected specimen, with no differences regarding the retrieved lymphnodes (MD = -1.06, 95%CI: -3.65 to 1.53, P = 0.42), and tumor to high tie distance (MD = 14.26 cm, 95%CI: -4.30 to 32.82, P = 0.13); the surface of the resected mesocolon was higher in the L-CME group (MD = 11.75 cm2, 95%CI: 9.50 to 13.99, P < 0.001). The L-CME was associated with a lower rate of blood transfusions (OR = 0.45, 95%CI: 0.27 to 0.75, P = 0.002), faster recovery of gastrointestinal function, and less postoperative overall complication rate. The L-CME approach was associated with a statistical significant better three-year overall (OR = 2.02, 95%CI: 1.31 to 3.12, P = 0.001, I2 = 28%) and disease-free (OR = 1.45, 95% CI: 1.00 to 2.10, P = 0.05, I2 = 0%) survival.
Conclusion:
The laparoscopic approach offers the same quality of the resected specimen as the open approach in complete mesocolic excision with central vascular ligation for colon cancer. The laparoscopic complete mesocolic excision with central vascular ligation is superior in all perioperative results and at least non-inferior in long-term oncological outcomes.
Related Concept Videos
 01:54
Base Excision Repair
The first step of...
 01:10
Central Tendency: Analysis
The mean is one such measure, calculated by totaling all values in a dataset and dividing by the number of values. For instance, the mean blood pressure reading (120, 130, 140, 150) would be 135. However, the mean can be affected by extreme values or outliers.
The median, another measure,...
 02:22
The Colonization of Land
 01:08
Nucleotide Excision Repair
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview