Related Experiment Video
Updated: Feb 16, 2026

Three-dimensional Alginate-bead Culture of Human Pituitary Adenoma Cells
Published on: February 18, 2016
Stereotactic radiosurgery in pituitary adenomas: long-term single institution experience and role of the
Kita Sallabanda1, Sergey Usychkin2, Fernando Puebla2
1Instituto Madrileño de Oncología, Grupo IMO, Department of Neurosurgery, 7 Plaza Republica Argentina, 28002, Madrid, Spain.

Abstract:
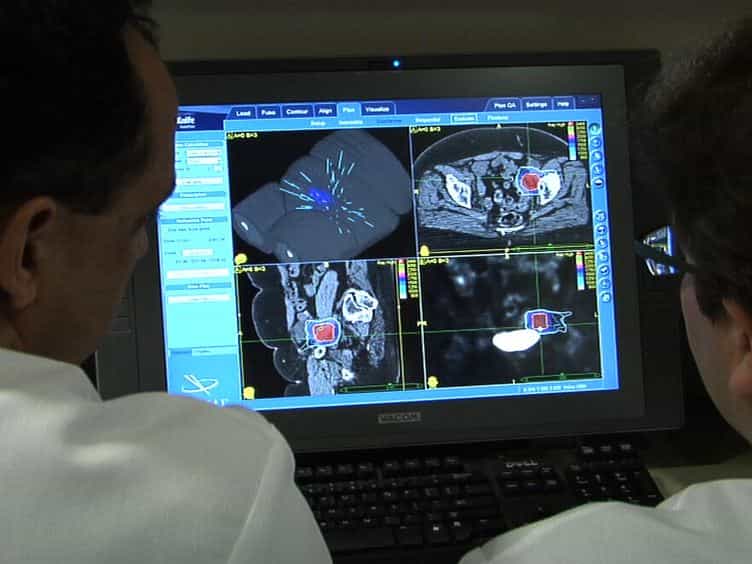
Stereotactic radiosurgery (SRS) is an effective treatment for incompletely resected or recurrent pituitary adenomas characterized by high rates of local control and endocrinological remission. The SRS-associated morbidity is usually considered minimal, but could not be neglected. It is mainly related to new pituitary hormone deficit, and seemingly caused by un-intentional inclusion of the hypothalamus, pituitary stalk and gland in the high-dose irradiation area. We report long-term clinical outcomes of 30 pituitary adenoma patients who received SRS in our institution. Dose was generally prescribed to the 90% isodose line and ranged from 10 to 16 Gy (mean and median 14 Gy). Selection of prescription dose was based on a tumor location and proximity to adjacent radiation-sensitive structures and previous radiotherapy. The length of follow-up varied from 15 to 230 months (mean 102.6 months, median 90 months). Overall, in 28 patients (93%) control of tumor growth was observed during the followup. In 19 patients (63%) tumor size was considered stable after SRS, in 9 patients (30%) tumor reduced in size and in 2 patients (7%) tumor progression was observed. Among 26 patients with functioning pituitary adenomas 17 patients (65,4%) had normalization and 4 patients (15,3%) had improvement of endocrinological function. Persistent hypersecretion was observed in 5 patients (19,3%) with functioning pituitary adenomas. New hypopituitarism after SRS treatment was observed in 4 patients (13.3%). The median maximum dose to hypothalamus, pituitary stalk and pituitary gland was 2.33 Gy (range 0.78-6.22 Gy), 11.20 Gy (range 3.17-15.49 Gy) and 12.83 Gy (range 5.00-15.24 Gy), respectively. SRS allows to effectively control tumor growth in 90-100% of patients and in the great part of patients a relatively rapid endocrinological remission is observed. Doses to the structures of hypothalamic-pituitary axis might have influence on the development of radiation-induced hypopituitarism. Every effort should be made to spare these structures as much as possible.

Related Concept Videos
 01:37
Hypothalamic-Pituitary Axis
 01:27
Hormones of the Pituitary Gland
The most abundantly secreted hormone from the anterior lobe is the growth hormone, which controls overall growth by...
 01:17
The Pituitary Gland
 01:29
Load along a Single Axis
Consider a beam of length L subjected to a varying load, which is a combination of parabolic and trapezoidal load distribution along the x-axis. In this case, it is essential to determine the resultant loads, their locations, and...
 03:20
The Stanford Prison Experiment
 01:05
Long-term Depression