Related Experiment Video
Updated: Feb 16, 2026

Author Spotlight: A Unique Mouse Model of Asphyxia-Induced Cardiac Arrest
Published on: April 14, 2023
Cardiac arrest during pregnancy: ongoing clinical conundrum
Carolyn M Zelop1, Sharon Einav2, Jill M Mhyre3
1Division of Maternal-Fetal Medicine, Department of Obstetrics and Gynecology, Valley Hospital, Ridgewood, NJ; Department of Obstetrics and Gynecology, New York University School of Medicine, New York, NY.

While global maternal mortality has decreased in the last 25 years, the maternal mortality ratio in the United States has actually increased. Maternal mortality is a complex phenomenon involving multifaceted socioeconomic and clinical parameters including inequalities in access to health care, racial and ethnic disparities, maternal comorbidities, and epidemiologic ascertainment bias. Escalating maternal mortality underscores the importance of clinician preparedness to respond to maternal cardiac arrest that may occur in any maternal health care setting. Management of maternal cardiac arrest requires an interdisciplinary team familiar with the physiologic changes of pregnancy and the maternal resuscitation algorithm. Interventions intended to mitigate obstacles such as aortocaval compression, which may undermine the success of resuscitation interventions, must be performed concurrent to standard basic and advanced cardiac life support maneuvers. High-quality chest compressions and oxygenation must be performed along with manual left lateral uterine displacement when the uterine size is ≥20 weeks. While deciphering the etiology of maternal cardiac arrest, diagnoses unique to pregnancy and those of the nonpregnant state should be considered at the same time. If initial basic life support and advanced cardiac life support interventions fail to restore maternal circulation within 4 minutes of cardiac arrest, perimortem delivery is advised provided the uterus is ≥20 weeks' size. Preparations for perimortem delivery are best anticipated by the resuscitation team for the procedure to be executed opportunely. Following delivery, intraabdominal examination may reveal a vascular catastrophe, hematoma, or both. If return of spontaneous circulation has not been achieved, additional interventions may include cardiopulmonary bypass and/or extracorporeal membrane oxygenation. Simulation and team training enhance institution readiness for maternal cardiac arrest. Knowledge gaps are significant in the science of maternal resuscitation. Further research is required to fully optimize: relief of aortocaval compression during the resuscitation process, gestational age and timing of perimortem delivery, and other interventions that deviate from nonpregnant standard resuscitation protocol to achieve successful maternal resuscitation. A robust detailed national and international prospective database was recommended by the International Liaison Committee on Resuscitation in 2015 to facilitate further research unique to cardiac arrest during pregnancy that will produce optimal resuscitation techniques for maternal cardiac arrest.
While global maternal mortality has decreased in the last 25 years, the maternal mortality ratio in the United States has actually increased. Maternal mortality is a complex phenomenon involving multifaceted socioeconomic and clinical parameters including inequalities in access to health care, racial and ethnic disparities, maternal comorbidities, and epidemiologic ascertainment bias. Escalating maternal mortality underscores the importance of clinician preparedness to respond to maternal cardiac arrest that may occur in any maternal health care setting. Management of maternal cardiac arrest requires an interdisciplinary team familiar with the physiologic changes of pregnancy and the maternal resuscitation algorithm. Interventions intended to mitigate obstacles such as aortocaval compression, which may undermine the success of resuscitation interventions, must be performed concurrent to standard basic and advanced cardiac life support maneuvers. High-quality chest compressions and oxygenation must be performed along with manual left lateral uterine displacement when the uterine size is ≥20 weeks. While deciphering the etiology of maternal cardiac arrest, diagnoses unique to pregnancy and those of the nonpregnant state should be considered at the same time. If initial basic life support and advanced cardiac life support interventions fail to restore maternal circulation within 4 minutes of cardiac arrest, perimortem delivery is advised provided the uterus is ≥20 weeks' size. Preparations for perimortem delivery are best anticipated by the resuscitation team for the procedure to be executed opportunely. Following delivery, intraabdominal examination may reveal a vascular catastrophe, hematoma, or both. If return of spontaneous circulation has not been achieved, additional interventions may include cardiopulmonary bypass and/or extracorporeal membrane oxygenation. Simulation and team training enhance institution readiness for maternal cardiac arrest. Knowledge gaps are significant in the science of maternal resuscitation. Further research is required to fully optimize: relief of aortocaval compression during the resuscitation process, gestational age and timing of perimortem delivery, and other interventions that deviate from nonpregnant standard resuscitation protocol to achieve successful maternal resuscitation. A robust detailed national and international prospective database was recommended by the International Liaison Committee on Resuscitation in 2015 to facilitate further research unique to cardiac arrest during pregnancy that will produce optimal resuscitation techniques for maternal cardiac arrest.
More Related Videos
 10:55
A Piglet Perinatal Asphyxia Model to Study Cardiac Injury and Hemodynamics after Cardiac Arrest, Resuscitation, and the Return of Spontaneous Circulation
Published on: January 13, 2023
 10:25
Normothermic Cardiac Arrest and Cardiopulmonary Resuscitation: A Mouse Model of Ischemia-Reperfusion Injury
Published on: August 30, 2011
Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:27
Nursing Clinical Information System
A Nursing Clinical Information System (NCIS) is a specialized type of healthcare information system tailored to meet the unique needs of nursing practice. It incorporates the principles of nursing informatics to streamline information management and improve the quality of care delivery.
Critical attributes of NCIS include:
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...
 01:19
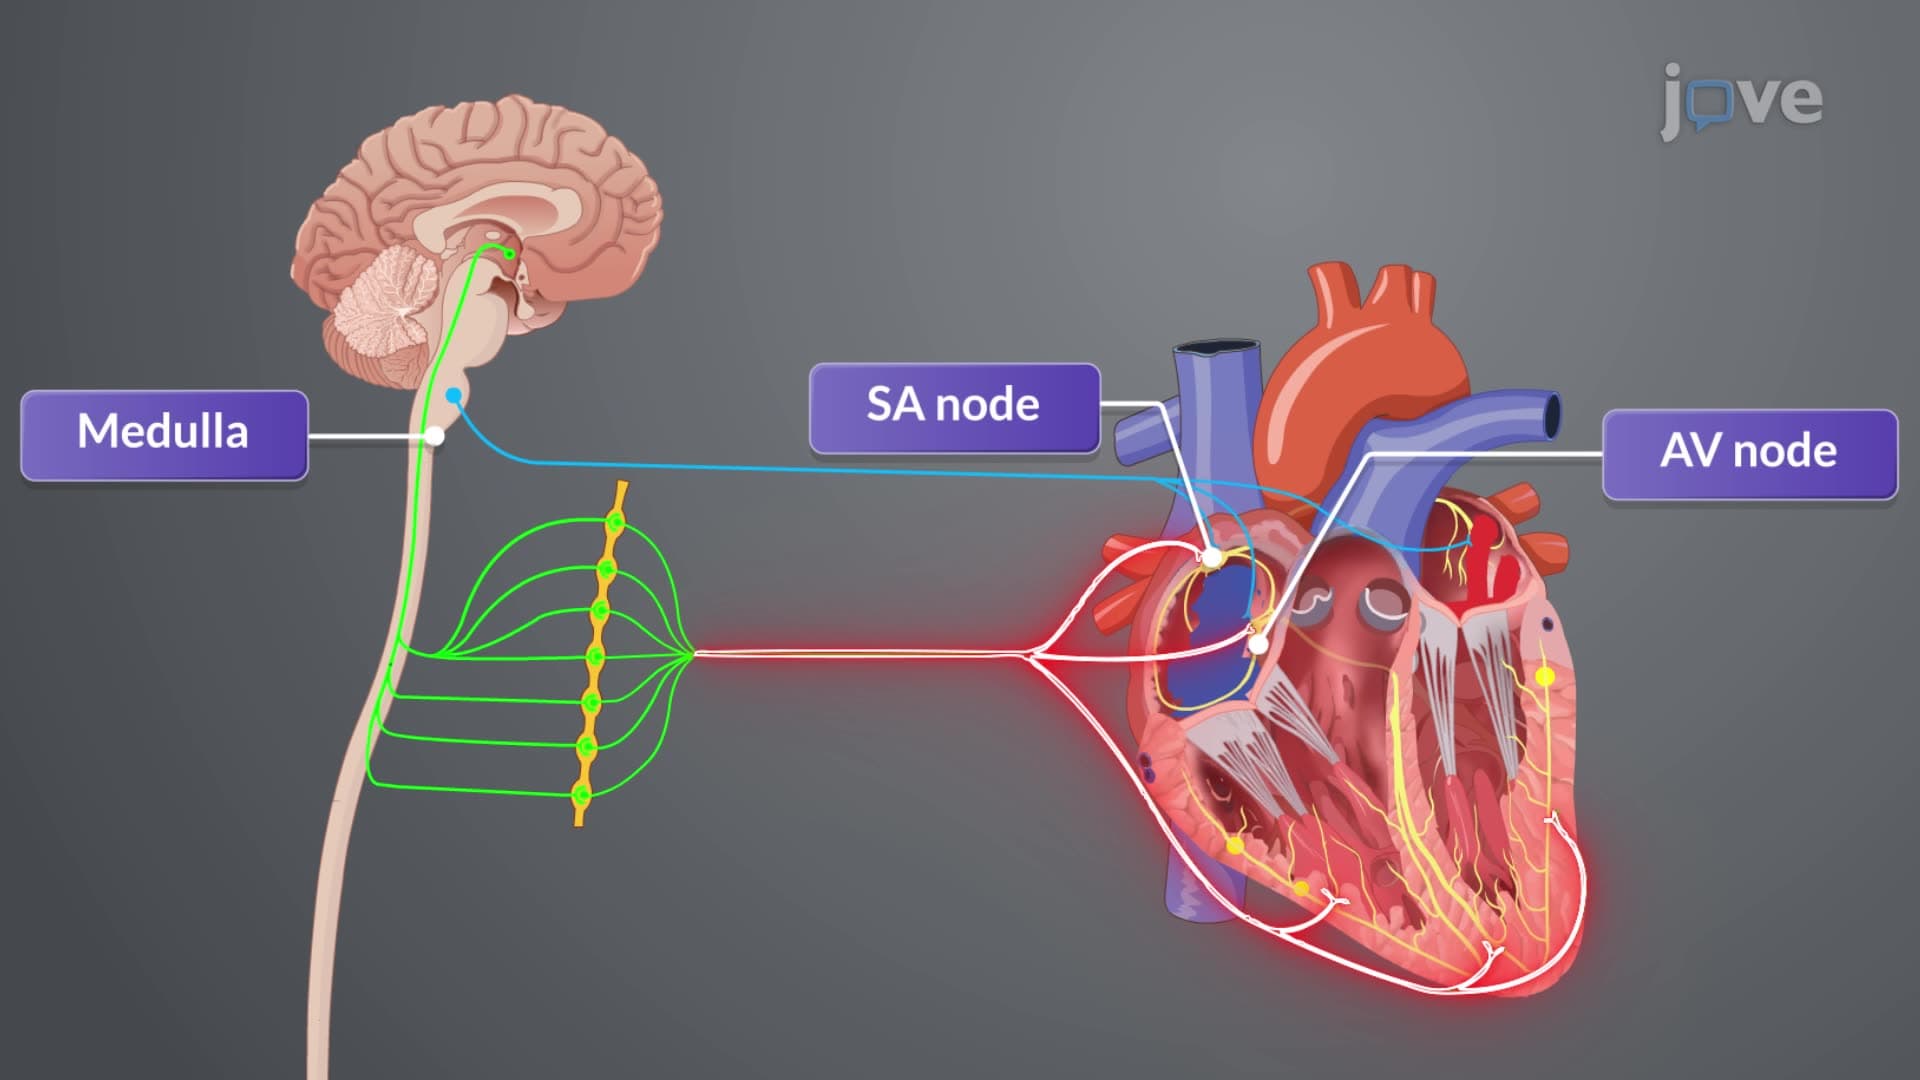
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...
 01:29
Cardiac Cycle
During the cardiac cycle, blood flow through the heart is regulated entirely by changing pressure gradients. This sequence of events begins with the heart in a state of total relaxation, known as mid-to-late diastole, during which blood passively flows from...